
You are currently browsing the category archive for the ‘Real life’ category.
Tuesday last week, I woke up to find this message in my Twitter DMs. I read it and read it again. It accompanied a tweet or two to me about my blog post from the previous day.
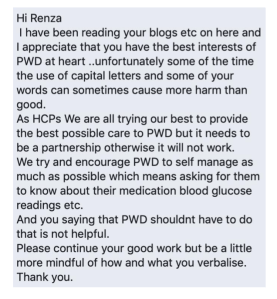
I debated about whether or not I should share this publicly. I wrote some words, walked away, came back to them, walked away, asked a few friends their thoughts, walked away, wrote a bit more and walked away again. I posted it to my closed Facebook page to get some feedback from others and wondered if that was enough.
But then remembered this blog post. #StandUP.
So, here I am, standing up. Because I am upset and angry.
I am not upset and angry that someone didn’t like or disagreed with what I wrote. It would be frightfully boring if we always all agreed with each other and loved the same things.
I am not upset and angry that this message was unsolicited. I believe that people don’t need an invitation to comment when I write and publish things on a public forum. I invite all feedback – good and not so good.
I’m not even upset or angry that I don’t understand what was being referred to in the message. I re-read and re-read and re-read my post, and I can’t see where I ever, ever said that people with diabetes shouldn’t self-manage, or know what meds they’re taking or what their glucose readings are. I couldn’t find it in there. But, people interpret things differently and perhaps my writing wasn’t as clear to them as I thought it was.
I’m not here today to defend the content in that blog post, because that’s not what this is about.
I am upset and angry that I was being told to ‘be mindful of what and how I verbalise’. This is called tone policing. It is telling me that I should moderate the way that I talk and think about my own diabetes. This was an opinion piece. My opinion. People don’t need to agree with it – and they can tell me they don’t. But telling me to moderate the way that I communicate is a very different thing.
I will forever call out and stand up to anyone who tells me, or others with diabetes, to restrain our feelings or opinions, and that is why I am writing this post. Because more than anything, I believe that we have a right to express how we feel about diabetes, in the way we want to, especially when we are sharing our own opinions or experiences. When we are told to be mindful of what and how we are writing/speaking it is a step on the way to censoring and silencing us. We already do that enough.
Often, in clinical settings, we moderate the way we speak. We might minimise how tough things are, or don’t speak out about the way we are treated or the judgement we face. When we are told that we’re not doing enough and are failing, we look down, afraid to stand up for ourselves.
And so, we created spaces where we could be free to share and rant and cry in a way that gave us some comfort. We turned to others who are likely to have had similar – if not identical – experiences. We share our opinions, some of them unpopular, thought-provoking and challenging of the status quo because we feel we have the liberty to do just that.
We have had to be quiet for too long. But that should never be the case in our own space.
The diabetes online community is that space. Twitter, when we use our #xxDOC (or #DSMA) hashtags is that space. Other online and offline support opportunities and groups we have created is that space.
And this blog (and others written by PWD) is that space.
So, back to the message I received last week. I did ask for clarification, and for examples of where I’d used capital letters or words that could be considered harmful, but I didn’t get a response.
Just this message:

No answers, just a threat to mute me. To silence my voice. Sure, it is only being silenced on this one person’s twitter stream, but that was the response to me refusing to be ‘compliant’ and agree with a healthcare professional’s demands that I tone down the way I write about my own opinion. I had not been aggressive, abusive or rude. I had just shared my own opinion and thoughts in my own voice. In my own space.
These days, I usually don’t show my glucose data online. When I first started Looping (about two and a half years ago), I regularly posted the flat CGM lines that amazed and surprised me. I also shared the not-flat lines that showed how hard my Loop app was working as temp basal rates changed almost every five minutes. The technology worked hard so I didn’t need to, and the results were astonishing to me. I shared them with disbelief. (And gratitude.)
I stopped doing that for a number of reasons. It did get boring, and I definitely recognise my privilege when I say that. I also acknowledge my privilege at being able to access the devices required for the technology to work. And there was the consideration that sharing these sorts of stats and data online inevitably lead to comparisons and competition. That was never my intention, but I certainly didn’t want to add to someone having a crappy diabetes day while I blabbed about how easy my day had been.
But today, I’m sharing this:

This was my previous 30-day time in range data from the Dexcom Clarity app on the day I arrived back home in Australia after returning from New York. (My range is set to 3.9mmol/l – 8.1mmol/l.) I’m not sharing it to show off or to boast. I don’t want congratulations or high fives. In fact, if anyone was to see this and pat me on the back, I would respond with the words: ‘I had very little do with it’.
I can’t really take credit for these numbers and would feel a fraud if anyone thought I worked hard to make this happen. Using an automated insulin delivery system full time means that I do so much less diabetes than ever before while yielding time-in-range data that I could once only dream of.
I want to share it, not to focus on the numbers (because it’s NEVER about the numbers!), but to explain what happens when diabetes tools get better and better, and what that means in reality to me.
Those thirty days included the following: End of year break up parties for work and other projects (four of those); ‘We-must-catch-up-before-the-end-of-the-year’ drinks with friends (dozens of those!); actual Xmas family celebrations (three of those over a day and a half– and I’m from an Italian family, so just think of the quantities of food consumed there). Oh, and then there were the three weeks away in NY with my family. Our holiday consisted of long-haul flights from Australia, frightful jet lag (there and back), a lot of food and drink indulgences, out-of-whack schedules, late nights, gallons of coffee, no routine, and more doughnuts than I should admit to consuming.
Add to that some diabetes bloopers of epic proportion that had the potential to completely and utterly railroad any best laid plans: insulin going bad, blocked infusion sets, sensors not lasting the distance, a Dex transmitter disaster.
And yet, despite all of that, my diabetes remained firmly in the background, chugging away, bothering me very little, with the end result being time in range of over eighty per cent.
This graph is only part of the story of why I so appreciate the technology that allowed me to have a carefree and relaxed month. Diabetes intruded so little into our holiday. I bolused from my iPhone or Apple watch, so diabetes devices were rarely even seen. Alarms were few and far between and easily silenced. I was rugged up in the NY cold, so no one even commented on the Dex on my upper arm. The few times I went low, a slug of juice or a few fruit pastilles were all it took, rather than needing to sit out for minutes or hours. Diabetes didn’t make me feel tired or overwhelmed, and my family didn’t need to adapt and adjust to accommodate it.
That time-in-range graph may be the physical evidence that can point to just how my diabetes behaved, but there is a lot more to it, namely, the lack of diabetes I needed to do!
As I spoke about this with Aaron, he reminded me of my well-worn comments about not waiting around for a diabetes cure. ‘You’ve always said that although you would love a cure, it’s the idea that diabetes is easier to manage that excites you. Ten years ago, when you spoke about what that looked like, you used to talk about diabetes intruding less and being less of a burden to your day. That is what you have now. And it is incredible.’
A very smart friend I met through Twitter, and has become a treasured IRL friend, says that when publicly telling our diabetes stories we may have opened a window into our lives, but that doesn’t mean we need to open a door. We get to choose how we protect ourselves and who we let in.
I choose to leave the window open and have come to learn over the years that as more and more people walk by, more people see what is going on inside. I know I can shut the window and draw the blinds any time I choose, and I did that for a short time at the end of last year. But mostly it is very, very wide open.
But having an open window to glance into doesn’t give anyone the right to yell that they don’t like what you see through the window, especially if I don’t ask. And certainly make sure that you have a good look and understand what you are seeing before you start to tell me that I am wrong about my decorating choices.
My window is on one side of the street. You can cross the road to avoid looking in. Or you can walk by, but not stop for a chat.
I choose what it looks like inside my window. I choose where the furniture goes, how it looks and feels. I live in it the way that works for me. I’m not a professional window dresser or decorator, just someone who knows what looks and feels good to me. I have never given decorating advice because I am not a professional decorator. Just a person living in this room that can be seen through that open window.
This blog is my open window. I welcome anyone who wants to peek inside. No one has to be here, but they’re welcome if they want to be. Some people might have a quick look and decide that it is all a little too frivolous or boring. They may think the things I get worked up about are a waste of time and that there are far better things to spend energy on. They may think it’s all naval grazing. They may think there are far too many pink stripes. That’s okay. It probably is a bit of each of those things, but it works for me. I sometimes write my thoughts on things in the broader diabetes world – and that may not be your take. That’s okay, too. We don’t need to agree on everything. I’m here, narrating my diabetes and how that intersects with the rest of my life, the world around me, the people I love.
Sometimes, I do that with great vulnerability. I share stories that are painfully personal and sometimes very raw. I try to infuse humour in there because sometimes, living with diabetes hurts so, so much that I need to break that up with something amusing.
I write about those sensitive topics, as well as more general day-to-day subjects, and that is not a decision I make lightly. I do it for selfish reasons – I hope that by telling my story I might just find someone who has a similar experience who can share their wisdom with, and help, me. Another reason is that I don’t want anyone to feel the loneliness and isolation I have felt at times. Diabetes can be lonely. Diabetes on top of other really tough things, such as infertility and pregnancy loss, parenting, mental illness, distress, diabetes-related complications can feel isolating.
If you don’t like what you see in here, that’s perfectly okay. If I have said something factually incorrect, I would really like to know about it so I can correct it. You can tell me about typos (I know there are many) and eventually, I may get around to fixing them. If I have upset you, I would love to understand why and welcome that discussion if you’re comfortable doing that. You can leave a comment – anonymously if you would like – sharing your thoughts.
But don’t ever tell me that I need to change what you read here because you don’t like what you see. Don’t tell me that I need to moderate what I say, or the tone in which I choose to say it. I have chosen to open the window into my diabetes life. But I have not ever chosen to be told how to live that life.

Outside looking in.
I wrote a post a while ago called ‘You Do You’, (and revisited and expanded on it here). It’s where I wrote about how everyone should have the freedom to do diabetes whichever way they see fit. I’m pro-choice in all aspects of life*, especially when it comes to PWD choosing their own management tools.
And I think that people with diabetes should have the choice to BE the people we need to be. And the people we are. I touched on this on my post on Monday when I spoke about how I felt intimidated online because my opinions and thoughts, and the way I addressed issues, were not everyone’s cup of tea. I felt that I was being called out for being myself. And that wasn’t okay.
No two people with diabetes are the same; no two people with diabetes will have precisely the same management ideas and preferences, and no two people with diabetes will react and respond to situations in exactly the same way.
THAT IS OKAY.
Diabetes is messy, frustrating, weird, annoying, amusing (rarely, but sometimes), scary, boring and a whole lot of other adjectives. And how we react and respond to it is our own business and no one else’s. You BE you, because you have the right to do that.
You have the right to be as loud or as quiet as you want.
You have the right to be as bitter and angry as you need to be in the moment.
You have the right to celebrate and be joyful about your diabetes.
You have the right to call out things that upset you just as much as you have the right to commend the things that make you satisfied.
You have the right to step away from groups, situations, people who upset you.
You have the right to disagree with others. Having an opposing view does not mean that you are attacking another person.
You have the right to have an opinion on what you see in the world of diabetes – even if it is happening on the other side of the world. I was incredulous when it was suggested that I shouldn’t question something happening in a healthcare system of which we are not a part. (I may not use the healthcare system in the US or the UK or Italy or anywhere other than Australia, but I am allowed to comment on what I see being done in those places.)
You have the right to be passionate and not be told that is a character flaw.
You have the right to be emotional because diabetes is real in a way that only makes sense to those of us who are living with it or have a loved one living with it. I don’t know how to take the emotion out of this, so you bet I will be emotional at times. I don’t get to clock off at the end of the work day and not think about it.
You have the right to use the words and language that works for you when talking about your own diabetes and if anyone tells you that #LanguageMatters is actually preventing PWD from doing that, tell them to fuck right off. It’s not. It never was. It never will be, and anyone who says it is has missed the point of the whole movement.
You have the right to use the word ‘fuck’ or whatever else you want to use. Profanity helps some people and we shouldn’t be told to wash out our mouths if others don’t like us using those words. (Sorry, dad.)
You have the right to be the sort of advocate you want to be. Or to not be an advocate.
You have the right to share your experiences – even the ones that don’t shine a particularly positive light on health systems or HCPs. No one – NO ONE – should silence us when we turn to our peers to seek support, or talk about what is going on in our diabetes lives.
You have the freedom to talk about your own diabetes, especially in the diabetes online community which we created for this very reason – to be able to share our experiences, learn from each other, support our peers and build each other up.
So, this? This is me being me. This is me standing up and not going quietly. This is me saying that I will be the person with diabetes I need to be, because it’s the only way I can be true to myself and true to my community.

*Except vaccinations. I don’t believe in choice there.
So, this is 2020? How are you going? I returned from overseas to a country literally burning and choked in smoke; a government that is refusing to accept that climate change is real; and a news organisation making up the narrative to suit themselves (arsonists are everywhere, apparently).
Bet you didn’t expect me to get so political before midday on a Monday!
Today is my first day back at work after three weeks of holidays in New York with my family. We spent the time basically relocating our Melbourne life to New York: finding a favourite café that served decent coffee, drinking great quantities of said coffee, wandering the streets, playing with (other people’s) dogs, warming up in bookstores and catching up with friends. It was the perfect way to farewell 2019 and welcome 2020.
As I have mentioned a million times before, I don’t do resolutions. You may not know this, but I live with diabetes, and that in itself gives me enough reasons to not reach goals and targets. I don’t need to add another list of things of which to fall short.
For the last three years, I’ve chosen a word that I’ve hoped would oversee and direct my way of thinking and acting for the year. As it turns out, that was a load of rubbish. Because each time, as I searched for the word that I wanted to guide me, the one I settled on went against the very grain of who I am.
The words were pause, focus and reset – and behind them was the idea that I would respond in ways that were really out of character; words that would silence or calm my natural responses.
But that’s not me. I walk towards things (usually at pace), I’m impulsive, I’m reactive. Sure, these may not necessarily be the best traits for a mindful, calm existence, and they can be exhausting, but welcome to my life: Hi, I’m Renza.
This year, I’m ditching the word idea, and using a phrase that better suits me, and that phrase is Stand Up.
We are living in a world that does not need people to be silent. Manners are all very important, but it is very possible to have manners and be polite, but still challenge things that we see as not right. We don’t need to be told how to think, how to feel, how to respond to something that upsets us. We don’t need to tone police ourselves – or others. We don’t need to accept what we are given.
And in the diabetes space, we don’t need people to be meek and mild. We need people who are disrupters and who speak their minds and who call out the bullshit. We definitely need to make sure that the voice of PWD is the loudest in the room, and that anyone who tries, even for a second on any platform, to tell us to pipe down is called out for it.
We do not need people to go quietly, and I am somewhat horrified that I did just that at the end of last year when I was feeling intimidated and vulnerable online. If I’m honest, I don’t recognise the person who switched her Twitter to private and wrote this thread to explain it to the people who were asking why.
Being angry is okay because there is a lot to get angry about in diabetes care. Not standing up means that we accept the situation for how it is. We can do it in a way that is nice and friendly, but sometimes it takes more than that. And that is okay.
I have never cared about being popular in the DOC or being considered one of the cool kids. I have never worried about follower numbers. I searched for this community because I needed support and I needed to feel part of something amongst people who were just life me. Other people with diabetes.
When I re-read my twitter thread from before Xmas, my heart broke NOT at what had happened; but at how I felt that the only way for me to stop feeling so unsafe was to turn away from the community – MY community. It was this tweet that set my tears running again:

I thought that if I had wandered into the DOC for the first time instead of the welcoming place it was, I saw PWD being challenged, I would have run away. THAT was what broke my heart – the very idea that I would not have discovered people like Kerri, Georgie, Cherise, Melissa, Mike, Dana, Grumps, David, Manny, Jeff, Mel, Frank, Alanna, Kelly, Ashleigh, Scott, Annie, Alecia, Bastian, Daniela and so, so many others. I don’t know how I would have navigated the murky waters of life with diabetes without those people: MY people for whom diabetes actually invades our DNA and the DNA of our loved ones. People there for the right reasons – not for the accolades, not for increasing follower counts. They are community-minded, open to opposing ideas and thoughts, and don’t consider themselves superheroes.
If I had have gone quietly, I would never have learnt from them; never had the support of people who understand; never had people like that at my back when I do stand up.
So, I don’t go quietly ever again. I stand up as I always have. I accept that doing that will send me into periods of advocacy burnout; I’ll deal with that when it happens, surrounded my friends and peers who get it.
So yes, this is 2020. I’m back. It’s really nice to see you here.

Each year, as we stop, look back and take stock, the reason that we are feeling so tired becomes apparent. This year is no different for me; my work travel calendar was the most intense it has ever been, with nine long haul trips, some for only a day or two. Combined with regular domestic travel, I can truly say that I have seen the inside of airports far too much. I stopped adding up the trips I did once I passed 100 walks down airbridges to board planes because it was making me weepy.
But on top of the usual exhaustion this year, there seems to be an extra element of fatigue that goes beyond what I’ve experienced before.
But first, let’s talk highlights, because there have been many of them.
The year kicked off with Spare A Rose and whoa, did we start the year with a bang! With the true philosophy of SaR at the forefront (an initiative for the community, by the community), we not only reached our rather audacious target, we smashed it! A cheeky and opportunistic little extra push saw a smiling Grumpy Pumper unleashed to the whole world for just a moment The DOC didn’t break, but the final tally of for the campaign meant that 939 kids in under-resourced countries would be receiving insulin for a year. Amazing!
My favourite issue, #LanguageMatters, only went from strength to strength, and the publication of this piece in BMJ, followed by this podcast, was a brilliant way to get it outside of the diabetes echo chamber. The importance of language featured on the programs of major conferences such as ADA and #IDF2019 with stellar panels speaking about why it really does matter.
My diabetes turned 21 and tied up in all the emotion of that, my pancreas’ performance review didn’t go all that well. Maybe next year? (Unlikely.)
Possibly the most exciting, heart-warming, rewarding and humbling thing I did this year was co-facilitate a workshop in Manila with some of the most dynamic, compassionate and enthusiastic young diabetes advocates I have ever met. I’m thrilled have had a chance to catch up with a couple of the people from this meeting and can see the wonderful work they are doing in more than trying circumstances.
Peer support was never far away. One of my favourite digital campaigns came from Diabetes Australia (remember – I work there so consider my bias) with our The Lowdown campaign. What a brilliant way to showcase how a digital campaign can reach and connect people from all over the world, and encourage them to safely speak about a topic that doesn’t seem to get anywhere enough coverage. I spoke about the campaign’s success in a number of places this year.
My own personal peer support experiences happened all around the globe at conferences, advisory board meetings and other opportunities to see friends and colleagues with diabetes. These moments ground me and help me make sense of what I am seeing and hearing, and are critical for keeping me balanced.
A special shout out to these two peers and dear, dear friends: Bastian and Grumps. We saw each other an inordinate number of times this year, literally all over the globe, travelling on planes, trains and automobiles for our #DiabetesOnTour. I do think we should launch a calendar of the 2020 pics. (Admittedly, we may be the only ones remotely interested in that idea.) When I talk about my diabetes tribe, it’s friends like these two. We’ve celebrated through some pretty amazing things this year, stood up to elevate the lived experience over and over, and also counselled each other through the tough bits. We’ve held post-mortems of long days, sitting in hotel foyers and bars, trying to make sense of what has happened, working out how to always improve, and plotting and planning more and more and more. I am so grateful to them for being the scaffolding holding me up when I’m away from home and feeling overwhelmed.

So, now the reason for that elevated exhaustion…
When I first wrote about advocacy burnout back in January this year, I had no idea at the time that it would set the scene for a difficult and sometimes troubling theme for the year. I get tired and overcome at times throughout the year, but 2019 was different and I’m not really sure why.
There were moments this year where I did honestly wonder how much more energy I have to stand up over and over again to a lot of what I was seeing. I don’t like using war and battle analogies in diabetes, but I did feel that I was fighting a lot of the time. Diabetes advocacy is a tough gig to begin with. Adding burnout on top of it makes it seem shattering.
Being attacked by HCPs for daring to voice my thoughts and challenge their behaviour, or getting it from certain, more confrontational parts of the diabetes community, or having industry reps tell me I don’t know what I’m talking about for daring to suggest that maybe their lame attempts to simulate diabetes in gameshow-style gimmicks at conferences could be better directed at actually engaging and listening to PWD all added up.
Or perhaps it was the repeated examples of ‘diabetes for laughs’…and realising that we are a long way away from HCPs truly being allies in our daily encounters with stigma.
Or perhaps it was feeling that we needed to justify just how important the #LanguageMatters movement, and the decade of work we’ve done really is. I can’t even begin to tell you how upsetting this little incident was.
It added up and several times I’ve felt overcome. I feel like that today. Which is disappointing because on measure, the highlights, the positives and the amazing community should overshadow the negative encounters.
And that is why I’m taking a break from Diabetogenic. I need some time away from feeling as though I want to analyse what is going on and comment on it. I have a wonderful holiday planned with my gorgeous family where we will see friends and wander wintery streets, rugged up in pompom hats. And then, will warm up once back in Australia to finish recharging my seriously diminished batteries, ready for a new year that’s already shaping up to be so, so busy.
Until then, I hope you have a wonderful holiday season, celebrating however you see fit. Thanks for popping by. And I’ll see you in 2020, clapping my hands and raring to go!

On the first day of IDF, a star of the Diabetes Spotlight was Ella Adams. We wanted to hear about how children with diabetes are best supported, what works and what could be improved. In the past, we usually don’t hear directly from the young person themselves. But at the IDF Congress this year, the Living with Diabetes program team was committed to hearing the lived experience as much as possible. Ella’s dad, Jason, gave a brilliant overview of how he and his wife have supported Ella, but then he stepped aside and Ella told her own story. And she did it beautifully.
Ella shared stories about how best laid plans sometimes just go a little haywire. Admirably, she just gets on with things, dealing with her diabetes around whatever situation she is in. She is fiercely independent and is doing such a stellar job of working out she wants to do diabetes in a way that works for her. She has taken on more and more responsibility for her own diabetes, her parents stepping back as she has felt ready to step up.
We had two young people on the program in the Living with Diabetes stream this year and I am so proud that we stayed true to our wishes of handing the microphone as much as possible to people living with diabetes. We saw a different type of program and Ella was very much a part of that.
Jason filmed his daughter’s presentation and shared it on YouTube, and they have given me permission to share it here. So here’s Ella. What an absolute star!
DISCLOSURE
I was the Chair of the Living with Diabetes Stream at the IDF Congress in Busan. My flights to Busan were covered by Ascensia Global (in order for me to get to Busan in time to co-facilitate their Social Media Summit). Flights home and accommodation were covered by the IDF.
Who wants to get out of a warm hotel bed and wander through the freezing streets of Busan to the BEXCO conference centre on the last day of an exhausting conference to be ready for an 8.30am session on diabetes and sexual health?
As it turns out, a lot of people do (including a few people who may have been doing karaoke until just a few hours earlier).
The symposium was in three parts. I started by talking about the female perspective of diabetes, sex and sexual health, followed by Grumps (Chris Aldred) giving the male perspective. Brilliant physician and academic, Fauzia Moyeen, closed out the session by highlighting current research in this area of diabetes.

Introducing Fauzia Moyeen to the stage.
My session at the IDF Congress focused on the recurring themes I hear from women living with diabetes. These themes were evident in responses to the blog post I wrote a couple of weeks ago asking women to share their experiences, and reinforced the messages I’d received after previous posts I’d published about diabetes, women and sex.
As much as I had wanted to present a variety of different experiences, the messages I heard from women was not especially diverse! Women from countries considered more liberal and open to discussions about sex said exactly the same things as out sisters from countries where you would expect limited information about sex and sexual health.
Over and over and over again, women echoed that they had never spoken about this issue with a healthcare professional, and if they had raised it, they were told diabetes does not impact on sex.
Some of the quotes were absolutely heartbreaking. Women shared stories of how their relationships ended because sex had become so painful and uncomfortable after their diabetes diagnosis and they had not been able to get help. One woman was told ‘…get used to it because that’s how it is’, another was told the pain was not real.
The emotional impact of feeling that yet another part of our bodies is letting us down and not doing what it is meant to is never considered or discussed. We are left to flail around with these intense feelings and concerns. It’s not even a matter of being able to get help – we don’t have anyone signal to us that this could be an issue.
Then there is the mess of adding hypos, or fear of hypos into sexual activity, or trying to be intimate when we’re hyper and our bodies feel leaden and achy. There is so little that is sexy about diabetes, and that may be especially true when we are trying to be our sexiest!
And then there is the whole contemplation of how to introduce a new partner to devices stuck on bodies and scars on skin, and the worry about how that will make them see us.
Discussion after my talk was lively, with HCPs asking some great questions. One wanted to know how to bring up the topic, which is really important. Many people are not comfortable talking about sex and sexual health. Not everyone is happy to share when they are experiencing problems. Cultural considerations come into play here as well. Having a HCP of a different gender speaking about sex makes some people very uncomfortable. One HCP said that when he has raised the topic, he’s been told that it’s none of his business.
I had some suggestions about normalising discussions about sex, while remain sensitive to people with diabetes, allowing them to dictate if this is a topic for discussion.
I believe it is essential that the person with diabetes is the one who decides whether or not sex and sexual health are to be topics of discussion. Now that doesn’t mean HCPs don’t get to ask at all, leaving all responsibility to the PWD. They can provide prompts. Perhaps have some brochures in the waiting room that can be accessed by women. (Yes! There are such things and you can see them here.)
Also, list sexual health and sex as something that may be affected by diabetes in general diabetes discussions. Think about it as a complication of diabetes and address it as you would any other complication. Just mentioning it plants a seed for the PWD to understand that this may be something that needs attention.
I borrowed a suggestion I heard Sarah Le Brocq during her language and obesity talk at the DEEP Summit earlier this year. Sarah shared how one GP practise has a little form for people to fill in before they go to see the doctor. There are a list of different issues and the person can tick the topics they are comfortable having discussed in the appointment. (This, she said, is a brilliant idea for people living with obesity, because often that is the first and only thing the doctor wants to speak about, even if the reason for the appointment is a sore finger or something irrelevant to the person’s weight).
Translated for diabetes, develop a checklist with potential topics, with sex as one of them. If the box had been ticked, that would signpost to the HCP that this was a topic that the person with diabetes wanted to discuss.
Another question came from a doctor who asked how to make discussions about sex a priority when he needs to focus on diabetes-related complications. ‘If a person is dead from a heart attack, sex won’t matter,’he said.
The response from people with diabetes was the same. Consultations need to focus on the issues that matter to people with diabetes, not tick the box exercises so HCPs feel that they are getting in all the things theywant to speak about.
Yesterday, I wrote this in my post:
‘… sometimes the chasm between what people living with diabetes want and need and what HCPs and researchers think we want is gulf-like.’
I felt that keenly after my talk. Women had told me that relationships had ended because of how diabetes had impacted on their sex lives. Others said that the discomfort they felt having sex meant that they just didn’t want to, and it had become a constant source of tension between them and their partner. Other women felt that they were failing themselves and their current or potential partners. One woman said that she refused to have sex because she didn’t want anyone to see how diabetes had marked her body.
To me, these sound like issues that need to be addressed, as much as, if not more so, than trying to adjust basal rates. They are just as important as making sure someone is doing their foot checks. They are far more important than knowing a current A1c. Dismissing the importance of sex in a woman with diabetes’ life as less critical than other aspects of her diabetes care clearly is doing us no favours.
The feedback following the session was really positive and I hope that we start to see similar sessions on programs at other diabetes events. Let’s get the dialogue happening so that women can feel comfortable talking about diabetes and sex. And get the help we may need.

DISCLOSURE
I was the Chair of the Living with Diabetes Stream at the IDF Congress in Busan. My flights to Busan were covered by Ascensia Global (in order for me to get to Busan in time to co-facilitate their Social Media Summit). Flights home and accommodation were covered by the IDF.
Busan is a very different city today than it was last week. There won’t be warmly dressed people hurrying into BEXCO with IDF2019 lanyards around their necks, eager to learn about diabetes. The word ‘diabetes’ won’t be uttered in almost every language of the globe. There won’t be Melbourne diabetes people loudly lamenting that Starbucks seems to be the coffee of choice in the city.
And you won’t see groups of people from all around the world standing together talking about what it’s like to live with diabetes. Most of us have gone home to our respective corners of the world, back to our families, back to our jobs, back to our real lives. But we will always have Busan and the incredible week of the IDF Congress.
By the time I arrived in Busan on Monday, the IDF was already a different beast. There was a new President and Board in place and some of the concerns that we’d had about the handover had melted away to nothing. This paved the way for what we really there for: a week of learning, networking, hearing different perspectives and truly uniting for diabetes.
We did that.
Was it a perfect conference? Of course not; they never are. There were hiccoughs and AV fun. There were controversies that played out online very differently to the way they actually happened in real life. There were sessions – critically important and brilliant sessions from all streams– with disappointing turnouts.
But these are all minor concerns that are the reality of every conference I have ever attended. There will be a time for post-mortems and evaluations and planning for improvements to future conferences. That time, however, is not now. Now is the time to celebrate.
IDF 2019 was a brilliant showcase of diabetes from around the globe. As expected, I only attended sessions from the Living with Diabetes stream and every single story was beautifully presented, and enhanced by the professional expertise of the HCPs who shared the stage. Amongst the incredible tales were moments of discomfort. It’s challenging to hear of the struggles many of my sisters and brothers with diabetes face in their day to day lives. I was forced to confront my privilege in a way that demands more than just acknowledging it there.
Also, difficult to accept is realising that sometimes the chasm between what people living with diabetes want and need and what HCPs and researchers think we want is gulf-like. For every HCP who ‘gets us’ and understands the value of lived experience in the healthcare space dialogue, there are many others who just don’t accept it, and, despairingly, don’t want to listen.
But more on that another day. Because for now, I’m focused on the people who did such a stellar job. So here are just some of them!

Two hours after touching down in Busan, and we kicked off the sixth Ascensia Social Media Summit with these gems.

Bright and early on day 1 of IDF2019, and the auditorium was packed to hear about diabetes and tech.

Always, ALWAYS, pleased to share the stage with Jane. Here we are just before the panel session.

Georgie excited to TALK ABOUT HYPOS! (We couldn’t understand why there was an explanation mark at the end of that sentence.)

Manny Hernandez gave the LWD Stream Award Lecture and there is no one more qualified to talk about the importance of diabetes community. How honoured I was to introduce him!

Celebrating Manny! (Photo courtesy of Boudewijn Bertsch)

From Melbourne to Busan. Neighbours at IDF2019. Jo was speaking about living with a rare type of diabetes and Andy was there for support (and photos from rooftops).

This woman! Sana, deputy lead of the LWD Stream and a bright, fierce force.

Anita eloquently explaining the challenges of living with diabetes-related complications in Indonesia.

Apoorva highlighting #LanguageMatters in her talk.

Some of the most dynamic young people I have ever met at the Young Leaders in Diabetes Training Summit.

Cherise can always be relied upon to ask thoughtful questions.

I’ve lost count of the cities we’ve done our #DiabetesOnTour this year, but these blokes have made all my travel so much better! Thanks Bastian and Grumps.

My favourite people at IDF2019? The two baristas running this uber-hipster coffee van.

We were all surprised to see the room packed full at 8.30am on the last day of the Congress. Sex sells. Or people just want to talk about it…

One of the best pieces of advice I was ever give was this: surround yourself with smart women. This is the LWD stream from IDF2019. I truly was surrounded by the smartest of women! Thank you Sana, Pei Yan and Elizabeth.

The final session in the LWD and my highlight of the whole congress was my neighbour, Sol, talking about living with MODY 3. We could not have scripted a closing remark better than his: ‘Being at this conference has made me feel part of something and with people that understand.’ Welcome to the world of diabetes peer support, Sol. You are so, so very welcome here.
DISCLOSURE
I was the Chair of the Living with Diabetes Stream at the IDF Congress in Busan. My flights to Busan were covered by Ascensia Global (in order for me to get to Busan in time to co-facilitate their Social Media Summit). Flights home and accommodation were covered by the IDF.

Shortbread with Smarties. (Time lapse at end of post.)
Every Sunday, I spend an hour or so doing one of my favourite things. I bake cookies, cakes, brownies or anything else that takes my fancy. I make a time lapse video of it and then share it to my Instagram and Facebook, along with some photos of the delicious finished product and the hashtag #AndOnSundaysWeBake. My friends and family frequently comment on my creations. Some ask for recipes; some ask if they can have some delivered to them; some are perplexed as to why I feel the need to add veggies to my cakes. (The answer is THIS ZUCCHINI BREAD RECIPE!!!!)
The other day, someone who had just started following me on Instagram asked me if these baked goods are my guilty pleasure.
‘Of course not,’ I said to them shaking my head. ‘Why should I feel guilty?’
‘Because they have sugar in them. And butter. Lots of carbs and fat. And you have diabetes. I thought you would steer clear of those kinds of foods.’
I sighed and thought that I could explain how as long as I cover the carbs with insulin, I am dealing with the diabetes side of things. And how I try to eat a balanced diet which mostly is made up of freshly cooked meals containing protein, in season vegetables and some carbs. I thought I could point to how I generally follow a low-ish carb diet because that works for me, and that my weekend (and week day too at times!) baking is a fabulous way for me to de-stress, and feel creative. I was going to point to how there is no such thing as a ‘diabetic diet’ and that people with diabetes can eat whatever we want and that it’s kinda not okay to ask us about what we are eating because it’s none of anyone else’s business. I started to tally up what I’d eaten for the day to highlight just how healthful my day’s food had been (so far) and was going to explain how I would be eating sashimi for lunch, and that has no carbs.
But instead, I just said ‘I don’t do guilty when it comes to food. And I try really hard not to do guilty when it comes to diabetes. Suggesting that we should feel guilty or shame when we eat something delicious that we enjoy – whether or not we’ve made it ourselves – just feeds into bullshit diet culture. My moral value has nothing to do with what I put in my mouth, or restricting food groups, or my weight.
‘So, to answer your question: No. What I bake on Sundays is not my guilty pleasure. But I do take great pleasure in baking and sharing the spoils with friends and family. And eating them. Because I am an amazing baker, and they taste absolutely delicious. Pleasure? You bet. Guilty? No fucking way!’
More?
My go to ‘smash diet culture’ SoMe sites are BodyPosiBetes and Feel Good Eating. Follow them for no-nonsense, no bullshit, no-diet-culture brilliance.





 Diabetogenic
