
You are currently browsing the category archive for the ‘Awareness’ category.
News out yesterday from the NDSS outlines the revised process for current Dexcom G6 users once the product is discontinued from the Scheme on 1 October 2026.
Current G6 registrants will be automatically transitioned to G7 sensors, meaning that an appointment with a diabetes healthcare professional is no longer required. It is our decision if we choose to meet with our HCP to discuss transitioning to a different device. Common sense prevails!
The change in process follows community pushback about the unnecessary burden expected of people with diabetes to see a healthcare professional for a simple technology upgrade. My article, written when I first received notification of the original policy (shared below), outlines my concerns, many of which were echoed by others in the community.

While this change is indeed a win, I will say a couple of things. The burden for demanding a change to the original policy fell on the community. Other than writing the post below (and this one), I took time to contact the NDSS, Diabetes Australia, the office of the Australian Health Minister, my local MP and the Department of Health. I spoke with a number of people in the community who were frustrated, disappointed and distressed at the process that had initially been proposed, and I helped draft letters for them to send to their local MPs.
That should not have been required, and I believe that it would NOT have been needed had people with diabetes been actively and meaningfully involved in discussions when news of the discontinuation of the G6 was first known.
Another change is that some of the paternalistic language from the original communication about the transition had been changed. In this one there is nothing suggesting that a health professional is the one to determine the most suitable device for us.
However, this paragraph does perhaps provide a glimpse into role of lived experience when it comes to NDSS policy and programs:
Working together to improve the experience of people living with diabetes
Diabetes Australia, the Australian Government Department of Health, Disability and Ageing, healthcare professionals and diabetes sector stakeholders are committed to ensuring that that the NDSS processes remain safe, evidence-based and centred on the needs of people living with diabetes.
I would suggest the glaring omission from the ‘commitment-making’ list is people with diabetes who, perhaps better than anyone else, would ensure that our needs are in fact centred. No one has safety in mind more than someone living with the condition. If processes are genuinely to be centred on our needs, people with diabetes must be directly involved in shaping them, not merely referenced as the people these decisions affect.
Details about transitioning to G7 (from G6) can be found on the NDSS website here.
Diabetes can’t have anything on its own it seems. It is often included under broad umbrellas such as non-communicable diseases (NCDs) or, (horribly), lifestyle diseases. Diabetes and obesity are linked as though the second is an inevitable consequence of the first. And, of course, within the overarching category of diabetes, there are many sub-types, each deserving of its own attention.
Often, discussions framed within diabetes contexts actually pivot away from diabetes, instead focusing on creating healthier environments – something for which we should all strive. But that isn’t just a diabetes issue. It’s an everyone issue.
And so, discussions about people living with diabetes right now, are watered down and lost in general population health conversations. Efforts to improve our diabetes-related outcomes, or make our lives with diabetes get swallowed by ‘big picture’ thinking that isn’t necessarily be all that relevant to diabetes specifically. Or, it is relevant to people with diabetes, but also to everyone else. Either way, diabetes gets lost.
Regardless of diabetes status, healthier environments are good for everyone. So why do these topics become the focus of so many sessions at a diabetes conference?
At last month’s IDF WPR Congress I attended a panel discussion organised by the Parliamentarians for Diabetes Global Network (PDGN). On stage were HCPs, parliamentarians and health professionals.
The first item on the agenda was sugar taxes. Do we need them? Super important topic to debate. Relevant exclusively to diabetes? Absolutely not.
From there, we detoured to urban planning with a comment about how houses on new estates are being built with barely any space to plant trees between boundaries. Sure, trees are critical for reducing urban air temperatures and improving air quality. Specifically, a diabetes-related topic? Nope.
I don’t disagree with any of these points. I definitely think we need more trees, and I think that urban planning and creating green spaces need better consideration. I’m also 100% pro-sugar tax, provided that it comes with policy that bans ‘junk food’ advertising, funds education programs and offers subsidies for healthier foods. I absolutely believe that we should do all we can to make healthier options easier.
But none of this relates exclusively to diabetes. These are public health and community issues.
And it’s not just conferences. We see this same conflation of diabetes with broader public health and wellbeing agendas in government policy too.
Australia missed an opportunity with the National Diabetes Inquiry a few years ago. The fact that it combined diabetes and obesity was the first miss. Two issues requiring attention and distinct strategies, and instead, they were folded into the same inquiry.
There were twenty-three recommendations in the inquiry report, and a number of those recommendations had little to do with diabetes at all, or were not specifically relevant to people with diabetes. What we miss when we conflate health and wellbeing initiatives with diabetes programs and policies is that we lose the ‘diabetesness’ in the discussion.
For example, recommendation 5 was about regulating the marketing of unhealthy food to children. Go ahead! Do it! Kids should not be bombarded with a barrage of advertising from unhealthy food companies every time they look at a screen. Their weekend sports shouldn’t be sponsored by burger companies, and those burger purchases should not come with a free toy. But tell me how that is a diabetes specific recommendation?
To be clear, I would like to see all 23 recommendations implemented. But because they’re so varied, any real focus on the diabetes-specific ones has been lost. To date none of the recommendations have been adopted, which is understandable when we consider the scale and cost recommendations spanning such huge, disparate populations. I can’t help but think that had the inquiry focused on diabetes alone (or even been broken down to specific types of diabetes), the recommendations would have been more manageable and easier to implement. For example, recommendation 16 (Explore expanded subsidised access to insulin pumps for all Australians with T1D) already had broad community-wide consensus. That’s the kind of focused, deliverable recommendation we lose when diabetes is diluted across a sprawling, catch-all inquiry.
A diabetes conference or inquiry should centre diabetes. Not anything on the periphery that may only tangentially relate to it.
Can you imagine a policy forum about breast cancer being hijacked by discussions of planting more trees? Or a sugar tax?
Living with diabetes is a hard gig. The people doing that work every day deserve conversations, policies and conferences that are actually about us. Not a line item in a broader public health agenda. There’s nothing wrong with planting a tree. Just don’t plant it and think it’s addressing diabetes.

What a treat it was to have the International Diabetes Federation Western Pacific Region (WPR) Congress in my hometown of Melbourne last week. Even more of a treat was to see people with lived experience and expertise of diabetes feature so prominently in the planning of the event, and on stages across the Melbourne Convention and Exhibition Centre.
I’ll begin by disclosing that I was the Chair of Stream 1, the Living with Diabetes Stream. When I was invited to take on this voluntary position, I was very specific about what I would need. The first was a committee made up of people with diabetes from across the WPR. The names that were first suggested to me were mostly Australian and looked and sounded like me and many were associated with diabetes professional organisations. I struck all the names off the list and started again. There are #dedoc° voices from across the WPR and it was so terrific to invite some of them to play an integral part in putting together a program showcasing the amazing work of advocates, grassroots community efforts, and stories of life with diabetes across the region.
After months of programming, we had an agenda that was a great balance of diverse stories and experiences. #dedoc° has a lot to answer for – the number of people in the stream who are alumni of the voices program was significant. (As were the many shout outs to Bastian across the week.)
Really centring people with diabetes resulted in stories that had people talking in corridors long after sessions ended. We structured each session to begin with short presentations and then moved to longer panel discussions to give the speakers the opportunity to engage with each other and deep dive into their work and experiences. We never got through all the questions from the audience, who were hungry to understand more. There was laughter at times – people with diabetes have the most wicked sense of humour when trying to get across their points! – and tears. In the numerous sessions I chaired, I reminded attendees of the emotional labour and emotional trauma it takes to relive and share our stories and to offer suggestions for how healthcare systems can better serve us. Trying to find solutions for the very systems that fail us is hard work. I think that should be emphasised more often.
It was also wonderful to see people with diabetes included in sessions across the other streams. There is so much power in bringing the lived experience into discussions about research, clinical and health outcomes, and education programs. I heard some incredible feedback from audience members in those sessions who said having someone with diabetes included in the discussion added a depth and perspective that is missed when they are excluded. Eleventy out of ten to the stream leads who followed through on their commitment to include lived experience and expertise in their programs. What a great example of how to be an ally! You bet we see those efforts and applaud them.
As ever, there are opportunities to improve engagement. I was disappointed at the complete absence of lived experience in a session that was about what good consumer and community involvement in diabetes research looks like. Make it make sense to me and explain how that conversation can happen without people with diabetes? And presentations about co-design that did not bother to include someone with diabetes in the session were also a miss. These glitches showed that #NothingAboutUsWithoutUs is not embedded across the diabetes world – not by a long shot – and it seems to remain the responsibility of people with diabetes to do the hard work and jump up and down when the mark has been missed. That’s just more emotional labour for us.
I was also disappointed at a comment about an organisation ‘using people with diabetes to provide input into research’. Language matters. People with diabetes are not there to ‘used’. We are there to engage and be engaged, to lead, to co-design, to inform, to guide, to influence. When someone tells you who they are, believe them, and the comment ‘use people with diabetes to provide input’ is tokenism at best. Taking advantage of community at worst. Thinking that it’s a great example of inclusion and engagement is offensive.
And I was frustrated when sessions about lived experience and expertise of diabetes were hijacked by audience members who used the open Q&A and comment time to talk themselves up. When the floor is open and the panel on stage has lived experience, it’s not an invitation to grab the mic and centre yourself or your organisation. Listening skills are somewhat amiss in some corners of the diabetes world, it seems.
The wash up from a very busy week of conferencing is overwhelming support for the strong representation and contribution of people with diabetes throughout the congress. A number of people have asked me if it is likely that the annual Australian Diabetes Congress will follow on from this year and introduce a living with diabetes stream. What a sterling idea, and one that I’d certainly love to see. It’s this sort of feedback that I’m holding on to now as we debrief and recover from the busy week. And look to how we can build on the momentum of truly and meaningfully engaging community in Australian diabetes conferences.

I’ve been in India this week for the annual Udaipur T1D Summit. This year, we took the summit to Jodhpur and once again, brought together dozens of people with diabetes, clinicians, researchers, industry stakeholders and policy makers.

One day, we all travelled to Nagaur, a city about three hours out of Jodhpur. We visited a T1D clinic in a district hospital, and attended a day camp for children and adolescents with T1D and their parents. This was for me, undoubtedly, the highlight of this visit to India.
The vast majority of the discussions were in Hindi and the local language. I understood nothing of the presentations other than the occasional words in English that cropped up from time to time. Afterwards, many of the people in the room spoke with me in English, and I had some lovely conversations with children and teens with diabetes, and their parents. I spoke with two young girls and they told me what they liked doing, about school and what annoys them about diabetes. A tiny toddler sat next to me and she was far more interested in the beaded bracelets on my arm than diabetes and really, who can blame her? Diabetes doesn’t compare to bright friendship bracelets! And I spoke with a remarkable young woman who I truly believe is going to change the world. She told me she wants to be a polo player, and I have no doubt that at some point I will find out that she is competing on national and international stages. She told me about how she feels about living with diabetes and her optimism and hope have stayed with me for the last few days. If only every newly diagnosed child with diabetes could connect with someone like her!
Parents spoke with each other, always keeping an eye on their children, but secure in the knowledge that in this room, everyone was looking out for each other.
I watched advocates who have become friends lead the activities, and I was in awe as they managed to show just how much peer support can mean. Jyotsana needs her own TV show – her enthusiasm and spark as she rallied the children was infectious. And Nupur and Snehal, ever calm and grounded, know exactly when to step in and when to step back. And then Prashanth rallied the children to do their injections together before they ate lunch, watching over each of them, and offering words of encouragement and words of reassurance. Worlds frequently collide in the diabetes advocacy space, and these incredible advocates are also #dedoc° voices. They are as confident and comfortable standing on stages at international professional diabetes conferences and in front of community groups. This is community at its best and most powerful.

One of the activities during the day is a ‘Wall of Hope’. I asked one of the event organisers translate the words on the post it notes. It came as no surprise to me that in the wishes and hopes and dreams of these young people, diabetes didn’t feature. They wrote about wanting to be doctors and teachers and work for the government. Many wrote about wanting to have happy lives. One said ‘I want to be strong like my mother and then I want to be a doctor’. I got a bit wobbly with that one!

There are some universal truths about T1D. I’ve come to learn that after decades of working in the diabetes space and spending time with others with diabetes. We are all different and we all carry diabetes in different ways. Our experiences vary based on diverse, complex and multiple factors. There absolutely is no one size fits all for diabetes.
But there is one constant that I have seen and continue to see ant that is the power of peer support. Spending time with others living with diabetes is life changing. The shared language of diabetes connects people in ways that make sense only to those of walking our own diabetes path.
One of the organisers of the event told me that me being there was important for the families and for the kids with diabetes. She looked surprised when I told her that it was important for me to see them. I learn from each and every other person with diabetes I come across and feel energised and connected. We all leave with out batteries recharged from the energy in the room.
Living with diabetes was never meant to be a solitary endeavour. It makes it so much easier when we have others who ‘get it’ because they’re living it too. That’s the superpower of community.
Disclosure
The Udaipur T1D Summit is a collaboration between Friends of Mewar (a charity run by Princess Padmaja Kumari Parmar who lives with T1D), the William J Clinton Foundation and Breakthrough T1D. I work at Breakthrough T1D as Senior Director, Global Responsibility.
For the last 25 and a half years, I’ve used an insulin pump to keep me alive. I’ve been using CGM almost full time since 2013, and sporadically before that.
Today, newspapers across Australia have published a fear-mongering report dressed up as serious investigative journalism about the safety of diabetes technologies and devices.
This is why we can’t have nice things.
Let me start by clarifying a couple of things. Firstly, the stories quoted from a few people with diabetes who have had genuinely frightening experiences with their technology should not be minimised. I understand how terrifying they may have felt when the devices they relied on didn’t behave as expected. And now they have made them question the safety of their devices.
And, secondly, I am fully aware of the shortcomings of diabetes tech. Of course I am. I’d be lying if I said I’d never had something go wrong in the well over 9,000 days I’ve had a diabetes device attached to my body.
But when I stop and weigh up the risks and compare them with the benefits, there’s no question that diabetes technology has not only been beneficial to me, it means that I am healthier than I thought possible, sleep better and spend far less time consumed by the endless decisions diabetes demands.
Decades of evidence show that use of these technologies improves diabetes outcomes, decreases glucose variability and lowers the risk of diabetes-related complications. My n=1 experience (which, for the record should be irrelevant in anything other than me talking about my own experience) is that these devices mean that I am able to show up as the best version of myself, despite the incredible challenges T1D throws my way.
The reports today highlight an increase in the reporting of adverse events. An ‘adverse event’ can be anything from a pump failure, a cannula blockage, a sensor failing or reading incorrectly or an alarm not sounding as expected.
It can also be device tape not adhering properly. Or skin irritations.
It shouldn’t take a genius to understand that the reason for the increase in adverse event reporting is the significant increase in people using these devices, thanks to NDSS subsidies.
Should we have the right to feel confident that government agencies are evaluating and monitoring the safety of these devices and acting when necessary? Absolutely.
There are thousands of hours of research demonstrating the safety of these devices, and that, overall, the benefits of diabetes technology far outweigh the risks.
I’d like to ask the journalists who have published this beat up and cherry picked lived experience stories: what’s the alternative? Should we go back to injecting insulin and blood glucose monitoring? I mean, there can be errors with blood glucose monitors (or I could not have completely wiped Nutella from my fingers before checking my glucose), so should we go back to peeing on a stick? And should we stop using automated insulin delivery and go back to doing all the calculations in our diabetes-exhausted and burnt out brains? DIY diabetes – and a reminder that all diabetes is DIY – was always far more dangerous to me than any automation from devices.
And I’d ask them where are the stories from the thousands and thousands of Australians who use these devices every day and are not experiencing serious problems?
I’d also like to remind them that people with T1D don’t get the option of opting out of risk. The comparison isn’t between diabetes technology and zero risk. The question is which approach gives us the best chance of staying alive and living well.
The potential damage to advocacy efforts for expanding access to insulin pumps for people with T1D and access to CGM for people with other types of diabetes has been done with this ‘investigation’ – a term I use very loosely here. Or for the introduction of the next generation of diabetes tech. Sowing the seeds of doubt without countering with balance, is irresponsible journalism. And in this case, it’s people with diabetes who stand to lose out.
What you can do today:
Write to Sixty Minutes, The Age and The Sydney Morning Herald with your concerns about their biased reporting.
If what you’ve read has made you second guess decisions about your own tech use, take a deep breath and double check your contingency plans and the limitations of tech we are all told about, and how to minimise them as best we can. If you’re really worried, contact your HCP.
Disclosures, because, jeez, that’s important today (and perhaps could have been clearer from some of the experts in the reports…)
I have used Omnipod, Deltec (RIP Cozmo) and a number of Medtronic pumps since 2001, and Dexcom sensors since 2013 (as well as some Medtronic sensors prior to that, and the occasional Abbott Libre sensor). I currently use Loop (Omnipod DASH and Dexcom G6). I pay for all diabetes devices consumables via the NDSS, and private health insurance covers the cost of insulin pumps.
As part of my health consultancy business, I have consulted for Medtronic, Abbott, Dexcom and Insulet (in Australia and globally). These consultancies have been focused on community engagement, language and communications.

Today, diabetes stopped me. It does that, which is why I am always somewhat confused at the toxic positivity of statements such as ‘diabetes doesn’t need to stop you’.
It stopped my plans for a walk with my kid because my blood glucose levels, for some reason, wouldn’t budge beyond 2.5mmol/l.
Ad then it stopped me joining a meeting on time because I accidentally ripped my pod off (door frames should come with a diabetes tech hazard warning) and the entry to my home office looked like a crime scene as blood gushed from my arm, all over the paintwork and down onto the floorboards.
That was just today. These may seem quite trivial, but they are just a couple of moments in time explaining how diabetes does indeed stop us in the moment, and in more significant ways. We can say that diabetes doesn’t stop us. And that may be the case. Until it does:
Until I am paralysed by fear of my kid having inherited the genes that have meant I have T1D.
Until I am overwhelmed by the fear of the unknown of what diabetes has in store for me tomorrow. Next month. Next year. Next decade.
Until I am told that I have developed some diabetes-related complication and I start catastrophising about how it will mean I’ll lose my independence.
Until I am feeling so burnt out by diabetes that I am unable to do the tasks I need to make diabetes just run, keep up with and fill insulin prescriptions, remember to order pump consumables and CGM supplies. (Oh, hey! Stripped Supply can help with this!)
Until we face stigma from random strangers in a café which may stop us doing the diabetes tasks that we need to do to simply stay alive.
Until a night of high glucose levels means I need a few hours of recovery, stopping me from carrying out the plans for the following day.
Until a bout of gastro leads to a bout of DKA and I find myself being forced to stop everything, and instead spend hours in A&E. (Or, if I’m lucky and have access to the VVED diabetes service, flaked out on the sofa managing at home.)
Suggesting that diabetes needn’t stop us ignores the systemic barriers that are a very real driver to diabetes stopping us. And campaigns rooted in toxic positivity do nothing to actually address those barriers.
Diabetes still means people are stopped from pursuing the career they have always wanted. And in some cases, it stops people from continuing the careers they have already built.
The considerable costs of diabetes – even in a country like Australia – stops people from doing a lot of the things they’d like to do. For some, the impact of diabetes on the family budget stops weekly food shops, other healthcare needs being met and household expenses being covered, and stops holidays from happening.
In some countries, where insulin is not easily available, or available at all, diabetes literally stops people from living. It’s pure privilege and a luck of being born in Australia that means this isn’t my reality.
Diabetes does stop us. And when we suggest that diabetes shouldn’t be a barrier and shouldn’t stop us, it erases the reality of day-to-day diabetes. And it can make us feel as though we are failing if we do need to stop and take time out.
Happy National Diabetes Week in Australia to all who celebrate. And for those of you who occasionally, or frequently find that diabetes does actually stop you sometimes, I see you.
More?
This article I wrote for diaTribe many years ago.

During the World Health Assembly in Geneva in May, there was an interesting shift as the days of the meeting progressed. I am always on high alert about the language used at these meetings (remember the ‘adherence’ event last year?), and this year, there was a definite shift in the words used when referring to people with lived experience of the health conditions discussed in different sessions.
Lived expertise started popping up, used by session chairs and moderators. This didn’t just happen by chance. For some time now, bolshy advocates (hand raised and waving…bolshily) have been stressing that what people with lived expereince bring to the table is indeed expertise. No one else can do it, and it is an essential part of any discussion.
During one of the audience discussions, I made the point of highlighting the importance of framing what people with different conditions bring as expertise. I emphasised that there is no one else capable of bringing that perspective and knowledge. The following day the moderator from that session introduced speakers with diabetes as having lived expertise. One of my colleagues reached over to me and tapped me on the arm: ‘Look at that! She’s changed her language from yesterday’s session’.
This shift is reflected in the new Meaningful Community Engagement framework used at ALIGN-T1D, where there is the clear acknowledgement that lived experience is expertise. (Disclosure: I work in the Global Responsibility team at Breakthrough T1D, the secretariat of ALIGN-T1D). It’s not just a framework document – it’s genuinely embedded in the project’s work and governance structure, and similarly, more broadly throughout the whole organisation. Can I tell you the utter joy I feel when colleagues without diabetes are the ones spearheading this language change rather than it being the person with diabetes! I see them doing it not only deliberately, but because they mean it.
Lived expertise in the diabetes context
I think for some people with diabetes it might take time to come around to using the moniker ‘expert’. I wrote years ago about how some people feel the term ‘advocate’ is loaded, and how not everyone who engages in advocacy feels comfortable adopting the label. I imagine for those people, coming on board and referring to themselves as experts might be a stretch. I’m curious as to why, and I wish that the imposter syndrome or whatever it is that is holding them back disappears so they can recognise the skill and expertise they bring.
While everyone with diabetes has expertise in their diabetes, we also need to recognise that there are expertise and skills that are learned. If we genuinely want lived expertise to be valued in the same way as other forms of expertise, we need others to understand that too. Otherwise, we see tokenism flourish as ‘anyone with diabetes will do’
For example, my expertise as a diabetes advocate lies in the areas upon which I have lived experience and also laboured experience. (For more about the four Ls of experience, please see this incredible piece in Diabetologia last year, led by Linxi Mytkolli with contributions from other #dedoc° voices from around the world.) With that knowledge, I know that I absolutely have expertise in what it means to live every day with T1D: the relentlessness, decision-making, stigma, language, healthcare interactions and the countless ways diabetes intersects with the rest of life because I have lived that reality for decades and spent years examining and articulating those experiences through my advocacy and writing. I don’t have expertise in living with T2D, or T1D and experiences that differ significantly from my own. That’s why I say no far more than yes when asked to act as a community representative.
My work – my laboured experience – means that I bring expertise around diabetes language, stigma, peer support, community engagement, advocacy and strategic communication. I have sat on numerous advisory boards and steering committees and, over time, developed the skills and expertise to lead and chair these groups. After spending years of acting as organisation spokespeople, I have expertise in media engagement and messaging. If I was asked to lead the design a diabetes registry or epidemiological study, I’d say no – that’s not where my expertise lies.
The problem with recognising lived experience as lived expertise is that there remains the issue of tokenism. If people’s expertise and skill as advocates or advisers or community representatives are overlooked, and anyone with diabetes is considered suitable, then we diminish the expertise they bring. To be involved in decision-making and advisory processes means having the confidence to push back, to challenge assumptions, to ask difficult questions and to recognise and overcome the real and perceived power imbalances that often exist in these spaces.
I will always say that people with diabetes should be centred and involved in all aspects of diabetes, but perhaps the caveat to that there needs to be consideration to match the right person with the right expertise to the right role. And that shouldn’t be surprising. After all, we readily accept that executive leadership positions, policy roles and research leadership roles require specific expertise and experience. Lived expertise should be treated with the same respect.
Recognising lived expertise means changing the questions we ask about who is involved in projects, advisory groups and decision-making processes. Instead of asking, ‘Do we have someone with diabetes at the table?’, we should be asking, ‘Whose expertise do we need?’ and ‘What experiences, skills and perspectives are missing from this discussion?’. Those are very different questions, and they lead to very different outcomes.
It also means being prepared to invest in people. We would never expect researchers, healthcare professionals or policymakers to become experts without mentoring, support or opportunities to develop their skills. The same should apply to lived expertise. If we want meaningful engagement, we need to support people to build confidence, gain experience and develop the skills needed to contribute effectively.

Recurring themes in diabetes recur for a reason: they impact people with diabetes. And stigma is one theme that you will hear people with diabetes speak about a lot. A. Lot.
Last week at the World Health Assembly in Geneva, there was much discussion about stigma – both within the diabetes and in other health condition spaces.
Stigma harms everyone. It goes without saying that there is no good form of stigma.
When speaking with people from other health organisations, it was interesting to learn that many see diabetes stakeholders as being leaders in addressing stigma.
There was a lot of interest in how we had come as far as we have. I shared what I knew and what I’ve been involved in and there was awe at the number of different activities that have involved so many stakeholders.
I agree that we are making strides in addressing diabetes-related stigma. But I’m afraid I wasn’t quite as enthusiastic as the people I spoke to who seemed to think that we had it all sorted. That’s sadly not the case. Every single week I hear from people with diabetes about the stigma they are experiencing, and the discrimination they have to deal with because of diabetes.
Last week, I found myself cringing at the airport when a security guard mentioned that perhaps if my diabetes was better managed I could stop using the devices attached to my body. He knew, you see. His niece has diabetes and she doesn’t need one of those machines.
I was too tired after hours of travel to do anything more than roll my eyes and say ‘That’s not how diabetes works’, and suggest that he doesn’t offer strangers unsolicited advice. I wondered if he had the same level of comfort telling someone wearing a pacemaker what to do to better manage their heart condition. Probably not.
And I snapped a sassy response on the Instagram page of one of my favourite bakers when someone suggested that dipping rhubarb in sugar was a one way ticket to diabetes. As if that’s all there is to this highly complex condition.
I’m tired and yet the stigma I deal with seems quite superficial when compared with that of many of my diabetes brothers and sisters living in other parts of the globe.
Diabetes stigma is real. It is harmful. It needs to end. And we all have a role to play in getting us to that end. I say that knowing that sometimes it’s too exhausting to do anything – and that’s perfectly okay. The full time job of managing diabetes is more than enough. Busting stigma shouldn’t also be on our to do list.
But if you have time, if you have the energy, if you have the will, there are some easy things you can do.
Sign the pledge to end diabetes stigma. You probably already have, especially if you’ve been hanging around here for a while. So perhaps, you could spend five minutes sharing the link to the pledge, or finding someone you know hasn’t signed it, and asking them to. It takes under a minute.
If you’re doing any sort of diabetes advocacy about stigma, circulate the International Consensus Statement to End Diabetes Stigma. Evidence matters, and this document brings together 51 experts across 18 countries. It was published in the Lancet and it is an excellent foundation for any work in the stigma space.
And if you want to see a video of joy, watch the one linked below. This is a compilation of what happened at the Summit to End Diabetes Stigma held in Jaipur in March this year. I assure you that amongst the colour and vibrancy you see in the video, there were difficult discussions, impactful panel sessions and plans for how to make real change.
My new friends from last week were impressed with what’s been done in the diabetes space, and I agree – the community has done so much already. But we’re not done. There’s a lot more to do. We’ve come this far because dedicated people have worked collaboratively. Community members have shown up to share their experiences. I’m so pleased to be part of these efforts. And will keep rolling up my sleeves as we address what still needs to be done.
You might think that a diagnosis of a new chronic health condition would be easier to navigate for someone with my understanding and knowledge of healthcare. And that with last year’s diagnosis of psoriatic arthritis (because it had been a while since I’d added a new autoimmune condition to the stable), that I would apply the same attitude that has worked with T1D.
I did do that. And it hasn’t worked. My first mistake was ignoring the very simple and basic fact that psoriatic arthritis is not type 1 diabetes. Most people probably would have realised that and not made assumptions. I am not most people.
I’ve been quite humbled by the overall experience.
I don’t have answers yet to how to manage this new(ish) condition. The pain is still persistent. The meds I was first prescribed did nothing other cause constant low-level nausea. I wouldn’t call it debilitating (the pain gets that designation at times), but it was unpleasant enough to make me feel bleurgh (technical term) a lot of the time. And to question whether drinking coffee was a good idea.
I have a limit to what I can take, and impacting my love of coffee hits that limit pretty quickly. I persevered for about six weeks with the meds and then decided that I’d had enough. The nausea wasn’t subsiding and the pain hadn’t improved at all. I had been told that it could take up to three months for the meds to impact the pain, so the fact that my hands still hurt pretty much every day wasn’t completely unexpected. I weighed up the pros and cons, and decided that I wasn’t prepared to add constant nausea and eating struggles to daily pain. And so, we went back to the drawing board.
At this point, I learnt about the rather technical little dance that needs to happen when it comes to the escalation of psoriatic arthritis drugs. From a rheumatology perspective, I have to give it three months before stepping up the ladder to the next type of medication. From a dermatology perspective, it’s only one month.
So, that meant I needed to see a dermatologist to prescribe the next drug. He announced that I had ‘failed drug 1’ and therefore would be able to try drug 2. After mentioning my failure three times, I politely interrupted and asked if we could perhaps reframe the conversation to say that the drug had failed me. I’m sure he rolled his eyes as I muttered something about language mattering, but he handed me a new prescription anyway.
But of course, it was never going to be a simple switch. My rheumatologist agreed that I’d been right to stop drug 1 due to the constant nausea. But she suggested we try an injectable version of it before stepping up to drug 2. Also, drug 2 is good for the psoriasis side of things, but less good for the arthritis side of things. ‘Keep that one in your back pocket for now,’ she said. We had a very brief discussion about the practicality of taking the injection, but we both kind of sped through that because we figured that twenty-seven years of T1D meant that injection technique and hygiene wasn’t something needing much attention.
I opened the first box of drug 1.2 on a Sunday night. In the box was one pre-filled, single dose syringe. I have never been needle-phobic, so, I wasn’t prepared for the involuntary gasp when I removed the cap from the syringe. The needle was not ‘just like an insulin sub-cut’ as I’d been reassured by the pharmacist and rheumatologist. It was significantly longer with a smaller gauge (smaller gauge = thicker needle). It looked scary. And needles do not scare me.
I sighed, pinched the skin on my leg where I could find a decent amount of fat and poke in the needle, pushing down the plunger, muttering ‘ouch’ for no good reason because it actually didn’t hurt. Appearances can be deceiving when it comes to needles.
This was all about four months ago now. Has it helped? Nope. Not at all. In fact, the side effects have been even worse. My weeks have taken on a new pattern: injection on Sunday night. Monday – Thursday: constant nausea (absolutely no appetite) plus exhaustion to the point of needing a late-afternoon nap. Friday: start to feel better. Saturday and Sunday: back to feeling normal. And then it starts all over again.
Meanwhile my hands still ached.
So, we’re moving onto a new drug. Will there be side effects? Maybe. Will I see an improvement in the pain situation? Maybe. Will I feel like I have some semblance of control over my health again? Who knows?
I don’t ever remember feeling this way with diabetes. Insulin just … worked. I mean, sure, there is the too much/too little thing that we all know about, but it does what it is meant to do. It lowers glucose levels.
But this has been entirely different and I feel quite naïve thinking that I was simply going to be given a drug to treat this ailment, said drug would fix said ailment, and then I’d just keep on taking it.
All of this has happened alongside managing diabetes and other health things that are constantly there. I’ve been fortunate that I’ve managed to find great healthcare professionals (albeit one who needs some work on his use of the word ‘failure’). My rheumatologist is absolutely delightful and understands my frustrations. I like a doctor who doesn’t tell me to push through or simply accept the lousy things. I appreciate her listening to what I want and knowing my priorities. And I like that she understands that this isn’t my first rodeo when it comes to chronic health conditions.
And yet, even with the great HCPs, and the drug options and the understanding a lot about health and healthcare I remain completely at a loss and humbled, because right now, I am not getting better. And being in pain is hard.
Apparently, there are half a dozen different drugs for me to try. And each one needs at least three months of trialling to see if it’s going to work. I don’t want to do the maths and think about how long it could take to find something that actually helps.
Who knew that all it would take for T1D to seem easy was a new autoimmune condition? Or perhaps it’s just that almost twenty-eight years of T1D-wrangling has lulled me into believing I know what I’m doing. I guess it’s all relative. I know that really, I am generally #NotGoodAtDiabetes (let me count the ways), but compared to dealing with this new condition, I’m actually brilliant. How utterly humbling.

Sunday is Feminist Christmas*. It’s the day that social media feeds turn pink and women get celebrated with morning teas (organised by women) and the lady folk are handed a cupcake (made by women) to shut us up and make us forget that women continue to live in a world designed and defined by patriarchy.
Isn’t that a joyful start to this article? I’ll wait while people shift uncomfortably and refer to me as an angry/difficult woman.
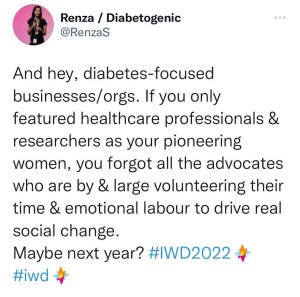
In the coming days in the diabetes world, you’ll see posts pointing to women in the diabetes landscape. These women are generally remarkable and doing great things. But oddly, rarely are the women whose faces appear on a social media carousel actually living with diabetes. A few years ago, I pointed out that while we should be recognising the clinicians and researchers improving our lives, women with diabetes are completely ignored.
So, a little hint to anyone who is putting together content for next week: don’t forget to also highlight the women with lived experience of diabetes who are actually doing so much of the work in our community. Those grassroots initiatives that continue to be life saving and life changing are very often powered by women with diabetes. And, as is often the case, these women do this work on a volunteer basis. All while managing a very demanding chronic health condition on top of all the other work women do.
In the meantime, you should all register for this year’s DiaLeb Annual Diabetes and Women Panel. This is the 7th year and I’m very excited to be on the panel with two remarkable women living with diabetes, and another two women with loved experience of diabetes. Be quick! It’s tomorrow!

Seriously, women with diabetes are brilliant. we deserve way more than a cupcake. But I’ll take one all the same if some bloke would like to organise it.
More on International Women’s Day at Diabetogenic
2023 – Deserving more than a cupcake
2019 – Interweb Jumble #34 – The IWD edit
*The brilliant Wilhelmina Stracke coined this term. You should follow her on Instagram.





 Diabetogenic
