
You are currently browsing the category archive for the ‘Real life’ category.
So often, there is amazing work being done in the diabetes world that is driven by or involves people with lived experience. Often, this is done in a volunteer capacity – although when we are working with organisations, I hope (and expect) that community members are remunerated for their time and expertise. Of course, there are a lot of organisations also doing some great work – especially those that link closely with people with diabetes through deliberate and meaningful community engagement.
Here are just a few things that involve community members that you can get involved in!
AID access – the time is now!
It’s National Diabetes Week in Australia and if you’ve been following along, you’ll have seen that technology access is very much on the agenda. I’m thrilled that the work I’ve been involved in around AID access (in particular fixing access to insulin pumps in Australia) has gained momentum and put the issue very firmly on the national advocacy agenda, which was one of the aims of the group when we first started working together. Now, we have a Consensus Statement endorsed by community members and all major Australian diabetes organisations, a key recommendation in the recently released Parliamentary Diabetes Inquiry and widening awareness of the issue. But we’re not done – there’s still more to do. Last week I wrote about how now we need the community to continue their involvement and make some noise about the issue. This update provides details of what to do next.
And to quickly show your support, sign the petition here.
Language Matters pregnancy
Earlier this week we saw the launch of a new online survey about the experiences of people with diabetes before, during and after pregnancy, specifically the language and communication used around and to them. Language ALWAYS matters and it doesn’t take much effort to learn from people with diabetes just how much it matters during the especially vulnerable time when pregnancy is on the discussion agenda. And so, this work has been very much powered by community, bringing together lots of people to establish just how people with diabetes can be better supported during this time.
Congratulations to Niki Breslin-Brooker for driving this initiative, and to the team of mainly community members along with HCPs. This has all been done by volunteers, out of hours, in between caring for family, managing work and dealing with diabetes. It’s an honour to work with you all, and a delight to share details of what we’ve been up to!
Have a look at some of the artwork that has been developed to accompany the work. What we know is that it isn’t difficult to make a change that makes a big difference. The phrases you’ll see in the artworks that are being rolled out will be familiar to many people with diabetes. I know I certainly heard most of them back when I was planning for pregnancy – two decades ago. As it turns out, people are still hearing them today. We can, and need to change that!
You can be a part of this important work by filling in this survey which asks for your experiences. It’s for people with diabetes and partners, family members and support people. They survey will be open until the end of September and will inform the next stage of this work – a position statement about language and communication to support people with diabetes.
How do I get involved in research?
One of the things I am frequently asked by PWD is how to learn about and get involved in research studies. Some ideas for Aussies with diabetes: JDRF Australia remains a driving force in type 1 diabetes research across the country, and a quick glance at their website provides a great overview. All trials are neatly located on one page to make it easy to see what’s on the go at the moment and to see if there is anything you can enrol in.
Another great central place to learn about current studies is the Diabetes Technology Research Group website.
ATIC is the Australasian Type 1 Diabetes Immunotherapy Collaboration and is a clinical trials network of adult and paediatric endocrinologists, immunologists, clinical trialists, and members of the T1Dcommunity across Australia and New Zealand, working together to accelerate the development and delivery of immunotherapy treatments for people with type 1 diabetes. More details of current research studies at the centre here.
HypoPAST
HypoPAST stands for Hypoglycaemia Prevention, Awareness of Symptoms and Treatment, and is an innovative online program designed to assist adults with type 1 diabetes in managing their fear of hypoglycaemia. The program focuses on hypoglycaemia prevention, awareness of symptoms, and treatment, offering a comprehensive range of resources, including information, activities, and videos. Study participants access HypoPAST on their computers, tablets, or smartphones.
This study is essential as it harnesses technology to provide practical tools for better diabetes management, addressing a critical need in the diabetes community. By reducing the anxiety associated with hypoglycaemia and improving symptom awareness and treatment strategies, HypoPAST has the potential to enhance the quality of life for individuals with type 1 diabetes.
The study is being conducted by the ACBRD and is currently recruiting participants. It’s almost been fully recruited for, but there are still places. More information here about how to get involved.
Type 1 Screen
Screening for T1D has been very much a focus of scientific conferences this year. At the recent American Diabetes Association Scientific Sessions, screening and information about the stages of T1D were covered in a number of sessions and symposia. Here in Australia. For more details about what’s being done in Australia in this space, check out Type 1 Screen.
And something to read
This article was published in The Lancet earlier in the year, but just sharing here for the first time. The article is about the importance of genuine consumer and community involvement in diabetes care, emphasising the benefits and challenges of ensuring diverse and representative participation to meet the community’s needs effectively.
I spend a lot of time thinking a lot about genuine community involvement in diabetes care and how people with diabetes can contribute to that ‘from the inside’. And by ‘inside’ I mean diabetes organisations, industry, healthcare settings and in research. I may be biased, but I think we add something. I’m grateful that others think that too. But not always. Sometimes, our impact is dismissed or minimised, as are the challenges we face when we act in these roles. I don’t speak for anyone else, but in my own personal instance, I start and end as a person with diabetes. I may work for diabetes organisations, have my own health consultancy, and spend a lot of time volunteering in the diabetes world, but what matters at the end of the day and what never leaves me is that I am a person living with diabetes. And I would expect that is how others would regard me too, or at least would remember that. It’s been somewhat shocking this year to see that some people seem to forget that.
Final thoughts…
Recently when I was in New York at Breakthrough T1D headquarters, I realised just how many people there are in the organisation living with the condition. It’s somewhat confronting – in a good way! – to realise that there are so many people with lived experience working with – very much with – the community. And it’s absolutely delightful to be surrounded by people with diabetes at all levels of the organisation – including the CEO. But you don’t have to have diabetes to work in diabetes. Some of the most impactful people I’ve worked with didn’t live with the condition. But being around people with diabetes as much as possible was important to them. It’s really easy to do when people with diabetes are on staff! I first visited the organisation’s office years ago – long before working with them – to give a talk about language and diabetes. One of the things that stood out for me back then was just how integral lived experience was at that organisation. From the hypo station (clearly put together by PWD who knew they would probably need to use the supplies!) to the conversations with the team, community was in the DNA of the place. As staff, I’ve now visited HQs a few times, and I’ve felt that even more keenly. Walking through the office a couple of weeks ago, I saw this on the desk of one of my colleagues and I couldn’t stop laughing when I saw it. IYKYK – and we completely knew!

DISCLOSURES (So many!)
I was part of the group working on the AID Consensus Statement, and the National AID Access Summit that led to the statement.
I am on the team working on the Language Matters Diabetes and Pregnancy initiative.
I was a co-author on the article, Living between two worlds: lessons for community involvement.
I am an investigator on the HypoPAST study.
My contribution to all these initiatives has been voluntary
I am a representative on the ATIC community group, for which I receive a gift voucher honorarium after attending meetings.
I work for Breakthrough T1D (formerly JDRF).
There are different types of burnout. Diabetes burnout, advocacy burnout, and just plain life burnout.
Diabetes burnout rears its ugly head for many of us living with the condition – sometimes starting as diabetes distress before building and building.
Advocacy burnout seems inevitable the more I discuss it with advocate friends. The living with, working in, supporting others with, diabetes becomes a lot. Too much. So much.
And life burnout seems to be inevitable in the fast-paced, never-pause-for-a-breath, always-switched-on lives we live.
When the three collide it’s a triple threat burnout. Welcome to mine.
The white noise hum of diabetes burnout – always there – slowly, but surely had become amplified. It was little things – I was regularly forgetting to bolus when I ate. Not immediately replacing CGM sensors when one fell off. Ignoring making the follow up diabetes appointments I needed to make, the pathology visit I needed to schedule, the supplies stocktake I needed to do to make sure I didn’t run out of anything.
I’ve been hovering on the edges of advocacy burnout for some time and found myself plunged into it earlier in the year dealing with the complexities that played out as I offered my help and support in some volunteer grassroots advocacy here in Australia.
And life burnout suddenly appeared in the form of exhaustion, but an inability to sleep soundly, and a brain fog that I explained away as a perimenopause symptom. Except it was more than that. It was getting to four in the afternoon before realising I’d not eaten a thing all day. And not remembering if I’d showered, or how many days had passed since I last washed my hair. It was a lethargy that gnawed at me all day long.
I focused on plans for a conference in the US, followed by a few days at work headquarters, knowing that it would be a busy and wonderful time, with a lot of interesting work. I could do it. And I did. The conference was excellent. The diabetes advocates there shone so brightly. And every meeting was a huge success.
Smile. Breath. Smile. Breathe.
Until I couldn’t. That moment hit like a tonne of bricks last week.
I’d spent a day in the office at the job I adore, speaking with incredible people doing so much work. I’m inspired daily by the people I work with and learn so much. There were plans set in motion for exciting things to come and I sat in the meeting room I had set myself up in for the day, feeling satisfied and pleased. The workday done, I packed up and stepped out into the street.
And then, a flash, an instant. Suddenly, the pressure bearing down and around on me was so intense and I felt my chest constrict. I struggled to breathe, and my vision blurred. The sounds on the New York streets suddenly seemed to be coming from under layers of concrete, muffled and hushed and yet piercing at the same time. The bright sunlight seared around me, causing me to shield my eyes from the glare.
‘Breathe. Breathe.’ I felt the rising fright of what I know to be a panic attack, and knew I needed to safely just ride it out. ‘Focus. Focus.’ I looked for something I could hold on to. There it was, a small dog, sitting still, staring dotingly at its human seated at an outdoor café, drinking an iced tea. I stood there, slightly hunched over, my arms wrapped around myself, watching this little dog sitting still. I started to count back from 50, getting to 34 before the dog moved, jumping onto its hindlegs, and resting its front paws on its person’s knee.
It was though the crush from the last few months had all converged. I’d tried in small ways to stem it. I limited my time online, muting more terms and accounts that sought to do nothing but argue and inflame. I welcomed the calmness that descended when my Twitter feed was devoid of people yelling about food choices, and when my Instagram feed only showed me the images of my nearest and dearest. I focused my outside of work advocacy efforts to AID access, specifically on the helpers. I threw myself into my job because it allowed me to focus and celebrate the work of others. I amplified the #dedoc° voices and other advocacy to keep my own away from the spotlight. I thought these things worked.
But at that moment, on the streets of lower Manhattan, those attempts didn’t matter or help. ‘But you seemed fine last week,’ said a friend I’d spent time with at ADA a few days earlier. I had been. I was. I thought about how I appear to others. ‘Sometimes, it’s too much. Right now, it’s too much. Forever… it’s too much.’
I felt the uptick in my heartrate. And realised that had been happening constantly. It had happened after the first difficulty with the grassroots advocacy work, and any time I had to face the source of that stress. Sometimes ‘facing’ meant a comment on a LinkedIn post. Sometimes, it meant a somewhat nasty direct message or, even worse, comments that came to me via others. I realised it had happened every time there was some nastiness or other on Twitter. It happened if there was a confrontation of any time around me, even when I wasn’t involved. Anywhere I saw conflict was enough to kickstart an anxiety response.
‘I’m okay’, I said to my friend. And then, ‘It feels too much.’ I felt myself and my mind and the space around me shatter into a million sharp, craggy pieces. And felt my skin being cut against each and every one of those shards.
This is burnout. This is what it feels like. And with it is anxiety and stress and feeling overwhelmed. We all get it to some degree. Diabetes makes it harder. Diabetes advocacy compounds the whole thing even more. Jet lag doesn’t help. Plus there’s a sprinkling of perimenopause over it all. The culmination is a fragility that scares me a bit and leaves me feeling vulnerable. ‘But you seemed fine…’ my friend had said. And I was. Until the burnout took over. And then I wasn’t anymore.

Poo, poop, crap, shit – whatever you want to call it, it’s not really a topic for polite dinner table conversation. So, if you’re at a polite dinner table, bookmark this and come back later. If you’re, say, on a flight to Orlando, stick around. I’m writing this on a flight to Orlando. The topic feels somewhat appropriate, but I digress.
This is the one about bowel cancer screening.
It all started back at the end of last year. I turned fifty and was suddenly on government watch lists for screening different parts of my ageing body. I wrote about my breast cancer screening a couple of months ago. Bowel cancer screening was next. I’m writing about this because I know people around my age have been putting off doing this. I get it. This sort of stuff scares the shit out of people, so I’m writing about my experience and hope that might encourage others to stop avoiding things.
Let me tell you something about the people who run the Australian bowel cancer screening program. They are stalkers. They start by sending you a letter. It’s friendly enough, just a little heads’ up (tails up?) that you should be on the look out for their next correspondence: a bowel cancer screening kit to do in the privacy of your own bathroom. Sure enough, it arrived a couple of weeks later, just as the silly season was in full swing and we were planning a trip to Italy.
The kit sat on my desk for a couple of months, and I kept meaning to do it, but travel, work, life and an utter lack of desire to actually collect samples of my poo meant that the kit taunted me every time I sat at my desk. During that time, I received reminders from the bowel screening program. Eventually, I got my shit together and stopped putting it off.
It was all very easy: you run a swab over your stool (which is sitting in the toilet on a piece of biodegradable, flushable paper) and then shove the whole swab in a little container with fluid and cap it tightly, pop the sample in a zip lock bag and then into a padded envelope. Probably the worst thing about it is that you need to send in two samples, from two different trips to the bathroom meaning you have your sample in your fridge until you next need to take a crap. (Because I’m germ phobic, I wrapped the padded envelop in three more zip lock bags, shoved into a brown paper bag. Totally unnecessary.)
The next day after collecting the second swab, I posted my sample and rewarded myself for being compliant (ha-ha) by having a massage.
About two weeks later, my stalkers friends from the screening program sent me another letter. There was blood in my sample, and I needed to urgently go see my GP. On the same day, my GP started sending me text messages and emails urging me to go see him. Now. Today. I was, of course, panicking because of course this meant THE WORST, even though the screening program letter assured me that in most cases there was nothing to worry about. BUT SEE YOUR GP NOW.
In Australia, we have an awesome public health system, but I decided to go private because it meant that I could see the gastroenterologist my GP referred me to, and I got an appointment within a week. I want to check my privilege here, because this option means there is a co-pay. I don’t know the time frame to see someone in the public system. (My breast cancer screening was all done through the public system and that was super quick, so that may be the case with bowel cancer screening too, but I can’t speak to that.)
The gastroenterologist was delightful. He apologised for being exactly seven minutes late. I laughed in diabetes and with the experience of someone who has spent too many hours in doctors’ waiting rooms told him he was, in fact, early. He looked all of about seventeen years old, but I could tell immediately that this was a doctor who knew his shit. And mine too, based on the report he had in front of him.
This was the sort of consultation that goes perfectly. Sensible questions about diabetes; super clear explanations about what was going to happen, and he did all he could to alleviate my concerns, reiterating what my GP and the screening letter had said – in most cases, a positive result is nothing. But blood in a sample will always trigger follow up, and that means a colonoscopy. He scheduled one for three weeks later. I had it on Monday.
It’s hard to put a positive spin on needing a colonoscopy, but I tried. I told myself that I would be getting an excellent afternoon nap on a Monday, and I could pretend I was a rubbish influencer doing some rubbish detox. After twenty-four hours of colonoscopy prep, I was reassured that I am no rubbish influencer and rubbish detoxes are, well, rubbish.
If you’ve not had a colonoscopy, or not familiar with how the prep works, let me explain: The week before the procedure, I was told to stop eating nuts, seeds, beans and red meat, and aim for a low fibre diet. Two days before, my food choices were limited further to white bread, eggs and grilled, skinless chicken and fish. The morning before, I could have breakfast of white bread and then nothing solid after that. But lots of clear fluids including tea and coffee (no milk), lemonade, apple juice, and jelly (but not red or purple). My mum, ever the Italian mamma, made me chicken broth, strained a million times so it was clear and full of nutrients, and that sustained me while I couldn’t eat.
I started taking the preparation at 4pm the day before the procedure. I mixed the first sachet into a glass of water and drank it down over about 10 minutes. It tasted like a fizzy orange drink. I put on some elastic-wasted trousers (I was warned that I didn’t want to be fiddling around with a belt or buttons), sat down in front of episodes of Grand Designs and waited. ‘You will experience extreme diarrhoea’ said the information leaflet. No shit, Sherlock. (Except, lots of shit. Obviously.) The solution kicked in after about forty-five minutes.
At 8pm, I mixed up the second sachet in a litre of water and drank that over an hour. I spent about six hours all up needing to head to the loo very quickly as everything was flushed out of me. Unpleasant, but exactly what was meant to happen.
By 10pm, I felt that I was going to be okay going to bed without having to keep running to the loo, and I slept through until my alarm went off at 7 the next morning. I made up the final prep sachet (same as the first), skulled it and, fasted from 8am until the procedure at 1pm.
Through it all, my diabetes was perfectly behaved. I increased my glucose target on my AID from 5.0mmol/l to 7.5mmol/l and entered a slightly reduced temp basal. My glucose levels remained steady the whole time. There were a couple of instances when there was an arrow trending down, but nothing that a couple of sips of clear lemonade couldn’t fix.
At midday on Monday, we headed to the hospital for what was an exceptionally positive experience with wonderful encounters the whole way through from the admission staff and all HCPs. I laughed at the amazed reaction from the anaesthetist when I handed him my iPhone with the instructions, ‘Swipe right to see my glucose levels’.
I walked into the procedure room, climbed on the table, chatted with what seemed like a cast of thousands and the next thing I knew, I was in recovery waking up. The gastroenterologist popped by to tell me everything went well. I love that he didn’t bury the lede: ‘Renza, you don’t have cancer. It all went well. There was one polyp that we removed and have sent away for pathology. I’ll call you in a couple of weeks, and you’ll need another colonoscopy in three years’. He commended me on the way I’d diligently followed the prep instructions. Apparently, I can be deliberately compliant!
The anaesthetist came by too, still slightly enthused with my tech and told me that my glucose levels were steady throughout the procedure. Diabetes was the least of my concerns and, as I do daily, I thanked the very clever people behind Open-Source AID for making things just a tiny bit easier.
And so, that’s the tale of my bowel cancer screening and subsequent colonoscopy. Absolutely something I would have preferred to not do, but glad that I did. How lucky we are to have these screening programs! It’s the same equation as with diabetes-related complications screenings: early detection, early treatment, best possible outcomes. Plus, peace of mind that comes with knowing there isn’t anything to worry about right now. And isn’t that a really good thing?
Shit yeah!

Details on this post
Eleven years ago on Mother’s Day, my friend Kerry started something on her socials. Kerry’s mum sadly died when Kerry was just six years old. She doesn’t have a single clear photo of the two of them together. And so, Kerry has urged her mum friends to make sure they take a photo with their kids – a really simple and special way to make sure that memories are recorded. (You can search for #KTPhotoForMum to see some lovely shared posts.)
We’re not short of photos in our household – who is in the age of smart phones? – but I especially love the album that I have of Mother’s Day photos of me and our girl. Seeing her on this day for the last eleven years brings a special feeling of joy.
But there’s another feeling in there that I want to recognise, and that’s how proud I am. Of course I’m proud of her – she’s a marvel (excuse my bias). But I’m talking about hoe I feel about myself as a mother living with diabetes. Because pregnancy and parenting with diabetes is not an easy gig.
I struggle with this sometimes. I don’t want to be defined by being someone’s mum. I achieved a lot before I became a mother and have done plenty in the last (almost) 20 years that I am so very proud of. There’s travel and a career, and media work, lots of published writing and a whole lot of standing on stages talking diabetes advocacy. These are usually the things that I point to when thinking about my achievements. For some reason, I’ve felt it’s diminishing to point to motherhood as an achievement.
But the truth is, that motherhood with diabetes is an achievement and it is defining in some ways. Conceiving, growing a baby, bringing her into this world, and getting her to adulthood is something that carries a huge sense of pride. Because, damn, diabetes made that hard. Every stage of it.
I get it: pregnancy is natural and it’s been happening forever and there are bazillions of people who have done it for a bazillion years, but there is absolutely nothing natural about taking on the role of a human organ. Seriously! It’s hard at the best of times. Being pregnant adds a degree of difficulty that is incomprehensible until you’re in the midst of it. Even today with tools that are far more sophisticated than the basic pump that saw me through my pregnancy, it’s still not easy. (And I utterly recognise how lucky I was at the time having a pump. The women sitting next to me at the Women’s Hospital diabetes & pregnancy clinic on Wednesday mornings who weren’t using a pump were real magicians.)
At that time I was just so in the weeds of dealing with all that came with a diabetes-complicated pregnancy that I never thought what an incredible job I was doing just getting through it. After all when was I meant to cheer myself for the remarkable effort? Was it before or after the 20+ finger prick checks I was doing each day? (CGM wasn’t around then.) Or alongside the complex calculations that I needed to complete before pre-bolusing the right amount of insulin at the exact right time? It certainly wouldn’t have been during the thirty percent of the day I was below target because in those moments, I was too busy worrying about starving my brain (and baby) of oxygen.
And then there was no time after she came along, because babies are all encompassing and take up every moment of the day. And diabetes can also be all encompassing and is incredibly demanding.
I had no time to be a cheerleader for myself because every single part of me was focused on making sure my baby’s elbows were growing properly, and stressing about how any out of range glucose level was harming her growing organs. Any spare brain bandwidth was taken up feeling guilty because I never felt I was doing enough. I felt that I was probably already failing my child. Even though her elbows are beautiful (and her organs seem fine), I still carry that guilt. Almost twenty years later.
These days, as more people with diabetes share their pregnancy and parenting stories, I DO cheer. Every time I hear about chaotic first trimester hypos, and managing glucose levels around second trimester cravings, and third trimester insulin-resistance frustrations, I know they deserve a loud ‘Hurrah!’ and so I cheer. Because look at these amazing people! Look at what they are doing – the work, the emotional rollercoaster, the determined effort they are putting in to keep themselves and their baby safe! Diabetes never plays nice, and for so many, pregnancy is the most difficult time in someone’s diabetes life.
Yesterday morning, I looked at our daughter as we had our Mother’s Day breakfast in the sunshine. Having her is the hardest thing I have ever done – the hardest, the most emotionally challenging, the scariest – but also the absolute best and I am so very proud that I did.
This post is dedicated to my dear friend Kati who I am cheering for every day!

Living with diabetes has made me acutely aware of the importance of screening. Eye screening, kidney screening, neuropathy screening, mental health screening – they’re all part and parcel of my diabetes care.
In my mind, screening is a non-negotiable because I live with a chronic health condition that refuses to stay in its lane, instead, spreading the love around. And by ‘love’ I mean ‘puts a heap of other things at risk’. Diabetes, the gift that keeps on giving.
Similarly, I’ve always (mostly) been on the ball on cervical screening. Regular Pap smears were booked in every two years. Cervical screening is different now. It’s done every five years (yay!) and is expected to protect almost a third more people from cervical cancer than the Pap smears of old (also yay!). AND there’s a DIY version for those who would prefer. I love it when progress makes unpleasant medical procedures slightly less unpleasant!
After last year’s BIG birthday, I knew that there would be more screening, and sure enough, almost before I’d blown out the last candle on my drawn-out birthday celebrations, both the Australian and Victoria Governments were sending me love letters to help me protect my health. The Australian Government’s bowel screening program came with a kit to do the screening at home. And the Victorian Government sent me a letter, urging me to make an appointment for a breast check.
Diligently, I did just that and had a mammogram at a local BreastScreen Victoria centre. That was about three weeks ago. I didn’t think about it again until I was about to board a long-haul flight home and opened an email asking me to come back for a follow up appointment. There were changes on my screening mammogram that needed to be investigated further. I had a fun 30-hour transit home imagining every possible catastrophic scenario (because: melodrama) and have spent the last week and a half oscillating between ignoring things and stressing over them.
And that brings me to today. This morning, I had my follow up appointment, and the short story is all is fine. (The very slightly less story is I had a 3D mammogram, my breasts contorted into expert-level origami configurations, and a million images taken to show that all is okay. Come back in two years.)
Walking back to the car, I took deep breaths, scolded my stupid brain for insisting on making things bigger and scarier than they ever need to be, and then reminding myself that I should be kinder because it’s not just this screening that was influencing how I felt.
I don’t know what it’s like to not live with a chronic health condition that places so many expectations for regular health checks and pressures on my mental health. Honestly, I wish I did. Because I know that the way that I am feeling – the anxiety, the stress, the worst-case-scenario obsessing – is so shaped by twenty-six years of living with diabetes. I can’t switch off these feelings or react differently. I can’t force myself to think of things through any other lens, because everything I see is through diabetes-coloured glasses.
This is the reality of living with diabetes. And it’s the legacy of scary images and campaigns and messaging that told me it was all inevitable. Of course I’m going to expect the worst because I heard that all for so very long. It wasn’t a giant leap for me to head straight to thinking the worst thing about a call back following a mammogram.
And so, because community is everything to me, as soon as I could I reached out to a friend who has had breast cancer. I needed to connect with someone with lived experience. Who better to try to talk through things? And the next person was a friend with diabetes who had recently had an experience that pretty much mirrored mine (and the same outcome). Of course I read everything I’d been sent from BreastScreen Victoria, but I needed to humanise the situation. And the only way I could do that was by speaking with people with lived experience, who could climb in beside me and wrap me up in a quilt of understanding and reality. Community really is everything. – whichever community it is.
WHILE WE’RE TALKING COMMUNITY…
If you’ve not yet shared and signed the petition for equitable access to AID for Australians wth T1D, please do! This is a community-driven initiative, created by people with diabetes in consultation with other stakeholders who have come together to advance advocacy on this issue. It’s getting close to 1,500 signatures already, and I’m seeing it shared widely in community groups and organisations. Thanks to everyone who has supported the community by being part of this advocacy.
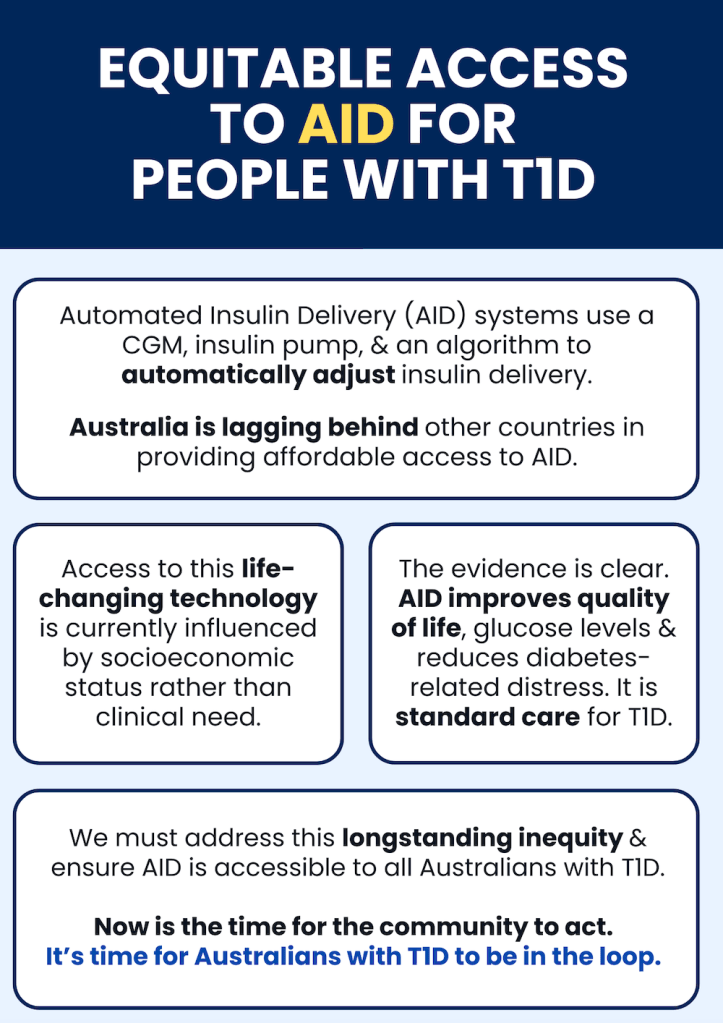
‘Why would you bet against the type 1 community?’ That was a question asked in a session at the ISPAD conference a couple years ago. It wasn’t someone with T1D drawing attention to the community. Instead, it was said by someone working in global health who had seen the remarkable efforts such as the #WeAreNotWaiting movement and grassroots, peer-led education initiatives in low-income countries. These efforts have driven change and improved lives of people with diabetes. They have been led by those with lived experience and supported by other diabetes stakeholders. But the starting point is people directly affected by diabetes identifying a problem, solving it and leading the way. In the history of diabetes – from the first home glucose meters, to building systems leveraging off existing technologies, to global advocacy movements – community powered initiatives have been a driving force for change.
And so, here we are today, coming together once again to advocate for better equity and fairness for all people with type 1 diabetes, this time in Australia, and this time advancing access to automated insulin delivery devices (AID).
Insulin pump funding is broken. AID is standard care and yet far too many people are left unable to use the tech because of how pumps are funded in Australia. Right now, unless a person with T1D has the right level of private health insurance, or meets the criteria for the Insulin Pump Program, they must find the funding for an insulin pump. That needs to change.
We know how to do this in Australia. The reason that pump consumables are on the NDSS is thanks to community advocacy efforts back in the early 2000. And more recently massive community noise helped to get CGM onto the NDSS for all Australians. Of course, these wins worked because everyone was involved in advocacy: people with lived experience of diabetes, healthcare professionals and HCP professional groups, researchers, diabetes community groups and organisations and industry. What a lot of noise we can make when we’re singing from the same song sheet!
Right now, attentions are razor focused on improving access to automated insulin delivery systems because the evidence is clear: AID reduces diabetes distress, improves quality of life, and (for those who like numbers!), help with glucose levels. And as an added bonus for the bean counters – it’s a smart, cost-effective investment for our health system.
If AID is standard care, financial barriers preventing people from accessing it need to be eliminated.
And that’s where we would love your help.
Please sign and share the petition that has been started by Dr Ben Nash and supported by a group of people with T1D (including me). Petitions are a great way to get people talking and interested in a topic. It builds momentum and helps contribute to whole of community conversations. While we know the T1D community is already on board, we’ve now seen a number of HCPs, community groups and diabetes organisations share and promote the petition and are keen to get involved with broader advocacy efforts. That’s pretty cool!

Postscipt:
Understandably, there are questions about why this work is specific to T1D technology access. That’s a fair question and I think that our very own Bionic Wookiee provided an excellent explanation of that when he said this in a social media post earlier this week:
‘AID systems were developed for T1D (where they can track all the insulin going into the system without having to cope with the body’s variable insulin generation). So right now they mainly apply to T1D…
Expanding CGM and pump access to people with other forms of diabetes than just T1D is important for the future. Having wider access to AID for the T1D population will be a beach-head for that.‘
And in a conversation I had about this with UK diabetologist Partha Kar yesterday he cautions that there needs to be a starting point because the sheer numbers of diabetes can be daunting and tend to scare policy makers. He also points out that when it comes to outcome modifying interventions, technology is THE thing in T1D, whereas in other types of diabetes there are other options. I’ll add that those other options often have stronger evidence which is why they already have funding.
Anniversaries – diaversaries – are for remembering. And today, my twenty-sixth diaversary, I’ve remembered that diagnosis day, and a lot of what has happened since. I’ve had a sensor fail. I’ve also enjoyed doughnuts, coffee and sunshine, and an AID so smart it has cleaned up all my diabetes incompetence and delivered a day of 95% TIR. Measure for measure, it’s been a good day!
My life would be impossibly different today if diabetes hadn’t moved in all those years ago. So much of my life, and so many of the people in it, is because of diabetes. The utterly confused and terrified twenty-four year old woman who walked out of a GP appointment after a diagnosis of T1D would never have believed the turn my life would take after I fell head first, and completely accidentally, into a life of diabetes advocacy. She wouldn’t recognise who I am, or how I fill my days and the people alongside me, the never-ending decisions I am forced to make, or the ever increasing stamps in my passport. She wouldn’t understand the normal that is my every day. But in the same way, I don’t remember her normal. (And thanks to Effin’ Birds for so beautifully illustrating that for me…)

Diaversaries are for remembering, but they are also for looking forward. Advocacy features so overwhelmingly in my future (and my present – I’ve spent a day off today working on an Australian grassroots community campaign). And so does advocating beyond our borders with the global access work I am so honoured to do at JDRF. And that means looking forward to people with a shared vision for real community and community involvement in ways that are meaningful and impactful. When I think of the last twenty-six years, community and others with diabetes feature so strongly. Because community is everything.
But perhaps most of all, diaversaries are a good opportunity to be hopeful. Advocacy has shaped who I am and how I have lived with diabetes, but hope has too. It’s as much of a driving force as anything else, something I hold on to every single day. I’m hopeful that access to diabetes care, insulin and other meds and technology becomes more equitable and that the heavy burden of diabetes casts an ever-diminishing shadow.
I stumbled across a book the other day called Women Holding Things. The author and illustrator, Maira Kalman referred to it as ‘love song to those exhausted from holding everything’. It’s quite gorgeous, with beautiful illustrations of all the things women hold – both literally and figuratively.
And I thought about what people with diabetes hold and just how weary and drained the weight of carrying diabetes and all that comes with it can be. I can’t draw, but here are my words that highlight some of the things we hold. It’s a love letter to the strength people with diabetes have gained through holding things, even when we want nothing more than to put it all down.
We hold on because we have no other choice but to do so.
We hold bags carrying around diabetes supplies – right now as I wait to board a flight, I have a separate bag with nothing more than sensors and pumps and alcohol wipes and spares of everything. I will hold it through airports, as I climb on planes, on ground transfer to hotels, and around with me through every step of my journey, a constant companion in my travels.
We hold cups of coffee because sometimes it feels like the only thing that will get us through the day.
We hold a fear of the future and what it can be, a shadow that sometimes stretches longer than we’d like.
We hold emergency hypo snacks ready for those unexpected moments. Or expected… (see: airports).
We hold guilt for some ridiculous reason because we shouldn’t and it is heavy and we would be so much lighter if we could let it go. But it’s there. We hold it.
We hold hope so close to our hearts, trying to balance up the fear or at least make a dent in its weight.
We hold insulin bottles and glucose monitoring supplies and all the little things that are needed to be replacement pancreases.
We hold anxiety and worry, and at times, a quiet uncertainty about what the next day, the next week, the next year holds.
We hold our diabetes friends close because they understand without needing explanations, and we hope that by being there for them as they hold us close, somehow there is a magic law of reciprocity that means we’re all holding less a little less diabetes.
We hold other diabetes stakeholders to account when they fall short of our expectations or fail to understand the nuances of our lived experiences, or underestimate our expertise. Or when they unleash a campaign that instils more fear.
We hold a steady gaze at research to see what our future life with diabetes might hold.
And we hold onto the promises, even the five-more-years promise that we know is a joke, but perhaps, just perhaps if we hold onto it tightly it might, it just might come true.
We hold our heads high as we advocate for better care, more understanding, and greater awareness.
We hold bottles of cinnamon, not because we know it’s a cure, but because it tastes great in the apple cake we’re holding onto for afternoon tea.
For those of us who can remember a before time, we hold on to memories about what life was like before we had to hold onto and carry diabetes.
We hold the hands of those whose diagnosis came after ours because we’re so grateful to those who came before us and held our hands.
We hold the key to lived experience and with it, we hold a unique perspective that must be listened to. Because we hold onto the belief that #NothingAboutUsWithoutUs
We hold a wealth of knowledge that comes from being a world class expert in our diabetes.
We hold a firm grip on the reality of life with diabetes because if we let that slip the consequences are too great to imagine.
We hold an inner strength that often surprises even ourselves.
Sometimes we hold back nothing as we tell our stories and and advocate for what is right.
We hold the power to change perceptions, influence policy, and inspire others.
We hold our spirits high when we feel we’ve had a win because holding onto those small victories carries us on through times where we feel we’re dropping the ball.
We hold our loved ones close, sometimes to protect them, sometimes to draw strength from their support.
We hold the courage to face each day, each challenge, with a bravery we often don’t credit ourselves for.
We hold a steady pace, because we know that diabetes is a marathon, not a sprint.
We hold onto the belief that it will be okay, that we will be okay. Because otherwise, there is nothing at all to hold onto. And that…that is just too heavy to contemplate.

The day after I was diagnosed with diabetes, I found myself in floods of tears, sitting in the stairwell of the Diabetes Victoria offices on Collins Street in Melbourne. I’d fled there from the NDSS shop that was housed on level three after suddenly feeling overwhelmed at the boxes and boxes of curious looking diabetes supplies that were about to be sent home with me. I was slumped against the wall, the emotion of the last twenty-four hours catching up with me. Someone came down the stairs and stopped. She crouched down and quietly said. ‘Hi. Are you okay?’
I wasn’t. Of course I wasn’t. ‘Can I sit here for a minute?’ she asked and somehow, through the tears, I nodded.
As it turned out, she was a diabetes educator working at Diabetes Victoria. And she also had type 1 diabetes. She spoke, I listened. And listened and listened. It was the first time I heard another person with diabetes share her experiences. She told me she too felt overwhelmed at times. And, she told me that right now – so new to it all – it feels so big, and that is perfectly understandable. She assured me that it would feel less big. She told me about bits of her life with diabetes and while she didn’t make it sound like bowls of cherries and puppy dogs, she took away tiny bit of the diagnosis fear that punches you right in the heart. Her stories made no sense at the time, but, as my own diabetes story grew, bit by bit, I understood her experiences.
I continue to search for stories today. I share some of mine – the things I feel comfortable sharing. And sometimes the things that aren’t all that comfortable.
I’m eternally grateful to that diabetes educator I met on 16 April, 1998. I told her repeatedly that her kind reassurance was the only brightness in those dark couple of days. I’m grateful to every other person who has so generously shared their lived experience. I never take it for granted – especially the reliving the trauma of difficult times.
And so tell your story. Only if you want.

Just what is the emotional labour associated with living with a life-long health condition like diabetes? I’ve been thinking about it a lot this week, firstly because I was asked to give a talk about it to a group of researchers to help them understand barriers they may experience with getting participants into their research. It was a great discussion, with plenty of questions and hopefully a new understanding of the burden diabetes unleashes on us. And then, I thought about it when I was feeling the weight of that burden – more so than usual.
The emotional labour of living with diabetes is a complex, often invisible force, shaping our lived experience in profound ways. It’s the mental and emotional effort we put into the never-ending demands of the condition. It’s accompanied by an inner dialogue that asks if we’re doing enough, trying enough, feeling enough, being enough. It comes on top of the physical labour of doing diabetes, which in itself, is significant. It’s an ever-accruing emotional toll of being perpetually alert, constant decision making and wondering how those decisions might impact our immediate and long-term health and wellbeing. The emotional resilience required to do diabetes each day is an additional burden of itself, the sum of all these parts equalling an unforgiving weight that, at times, just feels too damn heavy to carry anymore.
But it doesn’t end there. Living with diabetes is an act of advocacy in itself, even if that advocacy is for ourselves alone and whether we use the word or not. Some people who take on advocacy issues and causes, leading efforts, participating in them, speaking about them. Whether involved in advocacy as a paid day job, consulting-type role, voluntarily, or a hybrid version (me), all of it adds to the emotional labour of diabetes.
Of course advocacy can be energising – striving for better healthcare, pushing for more understanding, and campaigning for supportive policies are endeavours close to our hearts and seeing efforts result in stunning outcomes bolster our energy levels. Working together with others with diabetes to change our communities is motivating. But it can also be exhausting. Each act of advocacy draws from our already limited reserves. The constant need to explain, to justify, to fight for our rights and needs can lead to burnout, leaving us feeling drained and disheartened in a fight that seems unending.
That’s where I spent a lot of this week: drained, disheartened, devastated and frequently teary with the weight of advocacy casting a long, dark shadow.
I know that this is something people with diabetes speak about, and the mental health of diabetes is finally on agendas, but it still needs to be said that being adjacent to diabetes, or being a champion for mental healthcare doesn’t offer a true understanding of just what it feels like. The best allies I know are the ones who recognise this gap in understanding and do all they can to ensure they don’t add to it and try to learn by stepping back and not overshadowing our voices or efforts.
One of the ways people with diabetes have attempted to deal with this labour and resulting burnout is to build peer communities and networks. Solace from the weight of diabetes can be found in others with shared experiences in sanctuaries where our struggles don’t need to be explained but they are deeply understood. These are safe spaces where we exchange stories, share tips, and buoy each other’s spirits. These communities become a wellspring of support and encouragement, where our emotional labour is shared, and our advocacy efforts are collectively bolstered. Safeguarding those spaces is essential if we’re to draw strength from them rather than find ourselves being overwhelmed by them.
In recent years, I’ve found myself becoming more and more selective about where I find that support. Twitter was probably the first to be left behind as I no longer found it a safe space. I’m reminded of that any time I venture back an innocent tweet about my own diabetes choices is attacked from some low carb bro. I replaced the openness of social platforms with closed group chats of others with diabetes, knowing that the support was there without the risk of trolling. Those chats provide the light to guide my way through the shadows.
This week, with the heaviness of all that is diabetes weighing me down, it has been difficult to find that light. The networks I have are always there, but even that is sometimes not enough when everything is overwhelming. Hosting this week’s #docday°, and hearing from advocates from around the world doing incredible things wasn’t enough to help me see clear. I thought of how to push through this, and I don’t have an answer. Except this: One of the things we do so well in our community is lift each other up because our community and other people with diabetes are everything. And so, even while I am feeling weighted down, I can focus on that. And hope that in amplifying and cheerleading my peers with diabetes and their efforts, I’ll rise too.
Two community things you should know about…
Spare A Rose, Save a Life is continuing to accept donations here. Thanks to amazing advocate Tinotenda for driving this year’s campaign.
Sign and share this petition and read the consensus statement initiated by a group of #dedoc° voices which is calling for uninterrupted insulin access in humanitarian crises. Congrats to Lucia for coordinating this work.





 Diabetogenic
