
You are currently browsing the category archive for the ‘Awareness’ category.
Happy International Women’s Day!
I usually acknowledge this day with a post about some of the amazing women that we see in the diabetes world. Instead, today I’m going to take a more personal approach and mention some of the women who have so impacted me recently. Some will have been mentioned before – but maybe that’s because they continue to be the women who I look to. (I’ve linked to their Twitter accounts where possible.)
| Kerri Sparling | Dana Lewis
Alicia Jenkins Cheryl Steele Emma Stendhal |
Moira McCarthy
Rachel Portelli Helen Murphy |
That’s a pretty long list and it barely scratches the surface. But it serves more than the purpose of just signalling some of the women whose paths I’ve crossed in recent times, or whose work has inspired me in some way. It is a list to show just how easy it is to find women who are experts in diabetes in one way or another. It shows how women can just as easily be singled out to stand on a stage, sit on a panel, be interviewed in front of a camera to talk about diabetes.
Because that’s not always happening as equally as we would like.
Last year, at the IDF, the Women and Diabetes stream was led by a man (as it had been at the previous IDF Congress); there is only one woman on the advisory panel for ATTD; gender balance when it comes to speakers at diabetes events is generally not even close to equal; panels are often dominated by men.
All the women I have mentioned have, in some way, been trailblazers. I know many of them quite well, and I have seen and heard the challenges they face, the looks given around them when they speak and write, and the words that are used to describe them when their challenges hit a nerve. There is no one way that we choose to do our advocacy or our work. But our personality – how loud or quietly we do it – shouldn’t be a measure of anything.
Recently, a couple of people have referred to me as ‘strident’. My views and opinions have also been described that way. For the record, I didn’t ask for an assessment of my personality or my opinions; these were offered up to me (by men) who thought that my confidence and directness – and stridency – was part of the reason that I’ve been having a slightly tough time in some parts of the diabetes world lately.
Strident is a word that mostly seems to be directed towards women who will not go quietly, who stand up and challenge the status quo, who are seen to rock the boat, who want to be heard, who have opinions and are not afraid to share them. Sometimes, our anger and frustration comes to the fore and that is seen as us being unable to control our emotions. We’re not always called out overtly; sometimes instead there is reference to the preference for ‘moderate voices’. Moderate voices and opinions are okay. Strident ones? Not so much.
But you know what? I’m owning it. In much the same way that I have embraced the term ‘deliberately non-compliant’, I am now taking on board the term strident. You bet I’m a strident woman and I am proud to say that. And I’m proud to stand alongside dynamic, passionate, smart, controversial, sassy women who will not, and do not go quietly. Strident women – I know them and I am one of them. I am in outstanding company.

Previous IWD posts
‘Art is not a mirror held up to society but a hammer with which to shape it’. (A quote usually attributed to German playwright and poet, Bertolt Brecht, but actually first said by Trotsky.)
Using different artforms as advocacy platforms is not new. In my time working in diabetes (18 years), I’ve been lucky to be involved in a number of different initiatives with foundations very much in creativity and the arts. Perhaps my previous life as a musician – and being married to one for over 21 years – means that artistic approaches are always on my mind when looking at how to tell the story of diabetes.
When planning for the IDF Congress last year, a gap came up in our session on advocacy and diabetes awareness initiatives. Our Living with Diabetes stream committee wanted to look outside the box and move away from traditional awareness campaigns. ‘How about we get Appleton in?’ And that’s how we had a street artist from New York appear on the program in Busan last year in a session with the same title as this blog post!
At that time, I’d not met Appleton in person before, but I had come face-to-face with his artwork. (He’s on Insta here.) There is something quite magical when wandering the streets of NY to look up and see a bottle of insulin stuck to the wall of an old building in SoHo, or in Chelsea. I’d snapped photos and shared them to Facebook, wanting to learn more about the artist: Who is he? What is his story? What is the response to his artwork? After meeting him in Busan, and then again at a mutual friend’s place for dinner in NY, Appleton hosted me and my family in his New York studio one rainy afternoon in January and I learnt a lot about his work.

Appleton on W 23rd street.
But even before meeting Appleton, I’d seen the power of how different artforms have the potential to talk diabetes in different ways.
Australian actor and playwright, Alan Hopgood’s play ‘A Pill, a Pump and a Needle’ from a few years ago, told the story of three women living with diabetes. Chatting after a chance encounter in a café over coffee and cake, this was a quintessential Melbourne story! But it was also a great way to start a conversation with those who were lucky enough to see the play. I sat in the audience a number of times, then took to the stage to be part of the panel discussion. Mine was one of the stories that had been brought to life on stage and it was incredible to hear the number of people who watched the play and said that they could see themselves in the women’s stories. ‘Their stories are my stories are their stories,’ I would think to myself.
One year, my team at Diabetes Vic held an art competition for World Diabetes Day, asking children living with diabetes to submit an artwork depicting diabetes. The only requirement for submission was that the artwork needed to somehow incorporate the Blue Circle. I remember the way these pictures offered a most meaningful and impactful representation of life with diabetes – in ways that we’d not seen before. I still have one of those artworks hanging in my office. Its 14-year-old artist managed to perfectly capture the pain of diabetes balanced perfectly with the hope she felt. I’ve been looking at it a lot in the last week, breathing in deeply and letting her feelings of hope wash over me.
A number of years ago, The Diabetes Hands Foundation asked for submissions for an anthology of poems by people with diabetes. Selected poems were compiled in the book ‘No-Sugar Added Poetry’ – a copy of which sits on my bookshelf and is frequently pulled down and perused. In her introduction, Lee Ann Thill says ‘From words, carefully chosen, purposely arranged, emerges a shared experience and mutual understanding’. In other words, peer support through poetry.

And while mentioning Lee Ann… Diabetes Art Day was created by this dynamic advocate and art therapist to encourage people affected by diabetes to use whichever artform they wanted to express diabetes. I remember sitting around the kitchen table with my family, trying to show how we feel about diabetes with coloured paper, glue sticks and rubber letter stamps and ink.

Illustrator, Janina over at Miss Diabetes is absolutely brilliant in her depictions of diabetes. And, of course, comics by Claire Murray are still my favourite diabetes superhero tales. And my friend Weronika at Blue Sugar Cube, creates stunning pieces – her Spare a Rose designs were so gorgeous.

Click to be taken to Weronika’s Insta page.
Australian advocate Jenna’s artwork is nothing short of stunning. I bought one of her beautiful images earlier this year and need to get it framed so I can stare at it endlessly when I should be writing!

Click to be taken to Jenna’s Insta page.
Melissa Lee has combined her beautiful voice, brilliant sense of humour and story-telling powers to sing diabetes in ways that get us thinking, smiling, laughing…and crying.
As for me? Well, I create through baking and have managed to create some pretty damn fun and delicious cookies to mark important days and initiatives in the diabetes calendar.

And of course, storytelling is an artform, and I know that for me personally, that is how I have connected and felt supported by people affected by diabetes from every corner of the globe. Words have a power that can convey the very helplessness, hurt, hope and heartbreak that is real in diabetes, and as I frequently say, the stories people tell have always helped me make sense of my own diabetes.
Art has the power to reach people in ways that other, more traditional methods don’t. Health campaigns are important, but sometimes they seem just one step removed from the reality of real life. Art has the power to bridge that step and bring people together, and provide a fundamental understanding of the story being told, and the people behind those stories.
So back to the quote that opened this post: art can – and does – shape how diabetes is seen within and outside our community; it can influence how people outside the diabetes community understand diabetes, and within the community, offer different ways to think of things. It can start conversations that encourage us to consider others’ ideas; it pushes boundaries and forces us outside our comfort zones; it gives voice to people in the community who don’t necessarily want to use words to express how they feel. Advocacy using art can also cut through the white noise of health campaigns – often they all look and sound so similar that they are easy to ignore. But for me, I think the most powerful thing they give is humanity and hope to a condition that is often so misunderstood.
When I first started working for a diabetes organisation, the first big project I oversaw was the development of a booklet providing information to young people living with type 1 diabetes. After approaching a few others out in the community working with and supporting this cohort, I was promptly reprimanded by one person who told me in no uncertain terms that I (and the organisation I was working for) should butt out, because this was not our space; it was this group’s area. I was somewhat astonished at the idea of ‘owning’ a segment of the diabetes community. How did that happen? Who decided that? I was a young person with type 1 diabetes at the time (obviously, this was years ago!), and I didn’t feel especially well-represented by any one group, and I certainly objected to the idea of someone deciding that their group spoke for me and my ilk.
The diabetes community is made up of many, many voices (some louder than others), and each person has different priorities for their own diabetes, and the broader issue of diabetes in general. We see that every day with different campaigns that are driven by people in the community. Some of the most visible are movements or campaigns that employ hashtags such as #Insulin4All, (although the insulin affordability discussion encompasses more than just this hashtag), #NothingAboutUsWithoutUs and #WeAreNotWaiting, and, as we are still in February, #SpareARose. (Not too late to donate, folks!)
Actually, #SpareARose is an excellent example of this. It may have been started by a few incredible advocates, but they never felt the need to identify themselves as the ones who led or created it. They encouraged anyone and everyone to be involved in any way they could – to donate, to share, to write about it, to make vlogs. It is owned by all and by no one at the same time!
At ATTD last week, Chris ‘The Grumpy Pumper’ Aldred and I took to the stage to do a presentation on #TalkAboutComplications, which incorporates the under-discussed issue of diabetes-related complications and its intersection with #LanguageMatters. Our talk was in a session that incorporated presentations focusing on peer support and diabetes online community and technology – all very much ‘user-led’ initiatives and movements.
These campaigns are not about everyone having the same idea and perspective. People approach different issues in different ways. One person’s peer support ideal is another person’s living nightmare! And #LanguageMatters remains a topic with myriad ideas and expectations for just how embedded it should be in the hearts and minds of our community and beyond.
But it is undeniable that no one really claims ownership of any of these movements. While Grumps may have tweeted that hashtag #TalkAboutComplications first, I know that he doesn’t feel that he ‘owns’ it, or discussions around it. Rather, he used it as a rallying cry to bring people together – to find a tribe, so to speak, and to connect people with diabetes searching for information and support about the realities of living with diabetes-related complications.
I (and a couple of others) have been accused of claiming ownership of #LanguageMatters because of our frequent posts, tweets and other commentary on the issue, but anyone who has aimed that accusation at me has either never heard me speak about the topic or read this blog. Whilst I may be extraordinarily proud that I work for the organisation that developed and launched the first position statement addressing this topic, and I have been invited to speak about our work a number of times, I very clearly point out the origin story of this movement, and that is very much a story from the diabetes community.
People with, or affected by, diabetes have been speaking about how words and language impact for a long time. Older online discussion boards frequently held debates about PWD/diabetic for as long as I have been diagnosed (and I’m sure, many years before that). Parents of kids with diabetes shared how they felt judged and shamed by the words used by HCPs when their kids A1Cs were out of range, feelings echoed by adults with diabetes.
I remember one of the first articles I read in Conquest magazine (Diabetes Australia’s magazine back when I was diagnosed) was by Gordon Bunyan who eloquently wrote about how words matter. Gordon has become a good mate, and over the years I’ve turned to him regularly to talk about this issue. And I remember hearing how teenagers at camps instigated change when it came to the language used when talking about glucose levels, moving from using good and bad, to the more factual high and low. That was back before I was working for the organisation involved in those camps.
Diabetes Australia, in developing that position statement, wasn’t sticking a flag in the issue, claiming ownership – and nor have any of the people involved in its development. It was a response to something that mattered to people living with diabetes – people who told us repeatedly that the words spoken to and about them, the attitudes that those words conveyed and the feelings they had when different words were used had the ability to empower or harm.
Having organisations build programs, activities, resources and services around what people affected by diabetes are talking about unites the community. It also demonstrates a willingness to listen and acknowledge the value of lived experience. That was the thinking behind the development of DIYAPS and low carb position statements. Acknowledging PWDs’ right to choice of treatment truly does put us in the centre of the discussion.
I should say that I am not undermining that leadership that organisations and individuals show when taking on these issues. It does take people to run with the ideas and turn them into something – whether that be a position or guidance statement, or different service or resource. I admit to occasionally feeling a level of frustration that legitimacy of some of these important-to-the community issues only comes when they have been made ‘official’ by an organisation, but I also know that all stakeholders involved is important; that together we are stronger!
Last week we saw on show discussions that have their foundations very much in the community. They may have moved into the realm of HCPs and researchers, and the conference stage. But it is well worth remembering where – and why – they originated.

DIYAPS – started in the community and now on the program at ATTD!
DISCLOSURES
I was an invited speaker at #ATTD2020, and my registration was covered by the conference organising committee. My airfare and part of my accommodation to attend ATTD was covered by Lilly Diabetes so that I could participate in the DOCLab advisory group meeting which took place on Friday, Saturday and Sunday. Other accommodation was covered by DedocLabs (I am an advisor for the #dedoc° voices program) and Novo Nordisk (I am a member of DEEP). I have not been asked to write or speak about any of the activities I attended, or anything I have seen at the conference.
What would you change about your diabetes diagnosis?
Mine was almost 22 years ago, but much is still fresh in my mind. While there is a lot I am eternally grateful for, such as the speed and accuracy of diagnosis, and the way I was easily able to access specialist care, there are things that I wish were different.
One of those things is the line-up of HCPs that was offered to me. Making sure I knew the basics of daily diabetes management, the importance of knowing how many carbs I was eating, and the impact of activity, were, of course, critically important to learn before I was sent on my way. But diabetes was presented to me with this very one-dimensional approach. It was all about the magic carb/insulin/activity equation. Get that right and all would be relatively simple.
I had the relevant HCPs that could help me get that equation right – the endocrinologist, the diabetes educator and the dietitian. This was the holy trinity of diabetes care, I was told. This was the team that had diabetes knowledge to share.
And perhaps, if I’d been able to keep diabetes all about numbers, that trio would have been enough. Alas, it didn’t take long for this new-to-me medical condition to move to my head. No one mentioned the anxiety and fear that started to accompany the distress that was due to not being able to meet any of the targets I’d been set, and feeling overwhelmed by just how much diabetes there was to do. Or the disordered eating that may creep into my thinking because of this sudden focus on food in a different way. Or the crippling fear of complications that was keeping me awake at night.
I wish a version of these words had been said to me: ‘Diabetes is not easy. You can do this, but it is not easy. But we are here to help you. And endocrinologist and educator can help you with the practical side of diabetes. Food questions can go through your dietitian. We have an arsenal of allied health professionals to think about when it comes to doing all we can to reduce the risk of diabetes-related complications. And if you ever feel that you are becoming overwhelmed or anxious or distressed, if you ever want someone to talk with someone about how you are feeling to work through what’s going on outside the clinical aspects of diabetes, we have someone here for that too. It is perfectly, perfectly normal for you to feel all of those things. It is also perfectly normal for you to not feel them! We can help with whatever you need.’
Planting that seed would have made those first few years – those years before I found an endocrinologist who did say those words to me – so very, very different. I may not have understood why I might need, or rather want, to see a psychologist straight away – I didn’t understand what diabetes was, let alone how it was going to impact on my emotional wellbeing – but I wish that I had known from the very beginning that I had easy access to a one if and when I needed it. And that it was perfectly understandable if I did.
While I believe that GPs, endocrinologists and educators all have a role to play in talking about emotional wellbeing, they are not experts in this area. Having our diabetes HCPs acknowledge the high mental burden diabetes places on us is reassuring, but they may not be equipped with the strategies to help us lighten that load. But a psychologist can – especially one that works with people living with diabetes or other chronic health conditions. Plus, I repeatedly see HCPs say that they don’t have time as it is to ask about mental wellbeing, because there is already so much to do in the allotted appointment time.
Here’s the thing: so, so many people with diabetes are not reaching targets. Now, while I don’t agree with measuring diabetes success on numbers, that is still the way that it is done in many settings. And with that in mind, so many of us are above recommended glucose levels and our A1cs don’t even closely resemble what guidelines tell us to aim for. Clearly what we are doing now isn’t working, in fact, I’ll be so bold as to suggest that the current standard HCP line up is not necessarily best for PWD. Would adding a psychologist to the mix help? Would the expertise a psychologist can offer to help us learn how to address behaviour change, distress, anxiety result in not only feeling better about diabetes overall, but also improve those other measures?
I am not for a second suggesting that everyone with diabetes should have to see a psychologist. I don’t think that PWD should have to see any HCP they don’t believe is helping. But I do believe that we should be able to access a psychologist as easily and readily as we can any other diabetes HCP. Psychologists should be integral in multidisciplinary teams in diabetes clinics in the same way that educators, dietitians and endocrinologists are.
In my experience, it wasn’t until I started working with a psychologist that I got any benefit from seeing the rest of the diabetes team. Go check out the hashtag #DiabetesPsychologyMatters for some more commentary on this from PWD, psychologists and clinicians. It’s already gaining momentum, but I think it’s time that it really took off…

Tuesday last week, I woke up to find this message in my Twitter DMs. I read it and read it again. It accompanied a tweet or two to me about my blog post from the previous day.
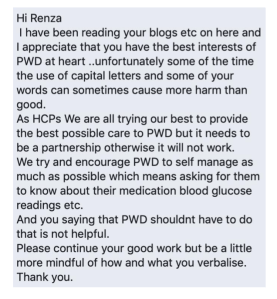
I debated about whether or not I should share this publicly. I wrote some words, walked away, came back to them, walked away, asked a few friends their thoughts, walked away, wrote a bit more and walked away again. I posted it to my closed Facebook page to get some feedback from others and wondered if that was enough.
But then remembered this blog post. #StandUP.
So, here I am, standing up. Because I am upset and angry.
I am not upset and angry that someone didn’t like or disagreed with what I wrote. It would be frightfully boring if we always all agreed with each other and loved the same things.
I am not upset and angry that this message was unsolicited. I believe that people don’t need an invitation to comment when I write and publish things on a public forum. I invite all feedback – good and not so good.
I’m not even upset or angry that I don’t understand what was being referred to in the message. I re-read and re-read and re-read my post, and I can’t see where I ever, ever said that people with diabetes shouldn’t self-manage, or know what meds they’re taking or what their glucose readings are. I couldn’t find it in there. But, people interpret things differently and perhaps my writing wasn’t as clear to them as I thought it was.
I’m not here today to defend the content in that blog post, because that’s not what this is about.
I am upset and angry that I was being told to ‘be mindful of what and how I verbalise’. This is called tone policing. It is telling me that I should moderate the way that I talk and think about my own diabetes. This was an opinion piece. My opinion. People don’t need to agree with it – and they can tell me they don’t. But telling me to moderate the way that I communicate is a very different thing.
I will forever call out and stand up to anyone who tells me, or others with diabetes, to restrain our feelings or opinions, and that is why I am writing this post. Because more than anything, I believe that we have a right to express how we feel about diabetes, in the way we want to, especially when we are sharing our own opinions or experiences. When we are told to be mindful of what and how we are writing/speaking it is a step on the way to censoring and silencing us. We already do that enough.
Often, in clinical settings, we moderate the way we speak. We might minimise how tough things are, or don’t speak out about the way we are treated or the judgement we face. When we are told that we’re not doing enough and are failing, we look down, afraid to stand up for ourselves.
And so, we created spaces where we could be free to share and rant and cry in a way that gave us some comfort. We turned to others who are likely to have had similar – if not identical – experiences. We share our opinions, some of them unpopular, thought-provoking and challenging of the status quo because we feel we have the liberty to do just that.
We have had to be quiet for too long. But that should never be the case in our own space.
The diabetes online community is that space. Twitter, when we use our #xxDOC (or #DSMA) hashtags is that space. Other online and offline support opportunities and groups we have created is that space.
And this blog (and others written by PWD) is that space.
So, back to the message I received last week. I did ask for clarification, and for examples of where I’d used capital letters or words that could be considered harmful, but I didn’t get a response.
Just this message:

No answers, just a threat to mute me. To silence my voice. Sure, it is only being silenced on this one person’s twitter stream, but that was the response to me refusing to be ‘compliant’ and agree with a healthcare professional’s demands that I tone down the way I write about my own opinion. I had not been aggressive, abusive or rude. I had just shared my own opinion and thoughts in my own voice. In my own space.
In a couple of weeks, the diabetes conference juggernaut will descend on Madrid for ATTD.
This one is all about new treatments and technologies in the world of diabetes and, in its thirteenth year, looks to once again be a busy and enlightening meeting.
There is so much on the program that focuses on user-led technologies and initiatives. I think it’s fair to say that PWD have long recognised that technology in diabetes is more than just the devices we wear on our bodies. We have long used technology for support and to connect to others who help us manage the day-to-day life of diabetes, and to learn and share. DIYAPS may be about the systems, but grasping the role of online platforms and support is essential in understanding the #WeAreNotWaiting movement as a whole.
 It’s great that a number of PWD already know that they will be part of ATTD this year, attending satellite events run by different device and drug companies. Some are on the program and some will be there through other opportunities and work.
The more the merrier, I say! Different voices with different experiences sharing and learning is always a great thing. And having the opportunity to meet people in real life after only seeing them online adds another dimension to our peer support networks.
For European diabetes friends yet to secure a place at ATTD, there is another possible avenue in, but you need to be quick. Launching at ATTD is the new #dedoc° voices program. Although #dedoc°has its foundations in Germany it is truly an international community, involving people from all over the world. #docday° events (always a highlight at these conferences) involve diabetes advocates from across Europe and the US, and even the odd Australian, too. It’s great to see this new initiative is helping more advocates get a seat at the diabetes conference table as active participants.
APPLY NOW
If you want to be considered for the #dedoc° voices program, you need apply, which is super simple – just go here, where you will find out all about the program and how to throw your name in the ring! Applications close on Friday, so chop chop!
Successful applicants will have their travel and accommodation costs reimbursed, and will receive full registration to the conference.
Good luck. And hope you see you there.
Disclosure
I am an advisor to the #dedoc° voices program. I do not receive any payment for this role.
I am an invited speaker at ATTD 2020. Lilly Diabetes is covering my travel and part of my accommodation so I can participate in the DOCLab advisory group meeting held during ATTD.
I wrote a post a while ago called ‘You Do You’, (and revisited and expanded on it here). It’s where I wrote about how everyone should have the freedom to do diabetes whichever way they see fit. I’m pro-choice in all aspects of life*, especially when it comes to PWD choosing their own management tools.
And I think that people with diabetes should have the choice to BE the people we need to be. And the people we are. I touched on this on my post on Monday when I spoke about how I felt intimidated online because my opinions and thoughts, and the way I addressed issues, were not everyone’s cup of tea. I felt that I was being called out for being myself. And that wasn’t okay.
No two people with diabetes are the same; no two people with diabetes will have precisely the same management ideas and preferences, and no two people with diabetes will react and respond to situations in exactly the same way.
THAT IS OKAY.
Diabetes is messy, frustrating, weird, annoying, amusing (rarely, but sometimes), scary, boring and a whole lot of other adjectives. And how we react and respond to it is our own business and no one else’s. You BE you, because you have the right to do that.
You have the right to be as loud or as quiet as you want.
You have the right to be as bitter and angry as you need to be in the moment.
You have the right to celebrate and be joyful about your diabetes.
You have the right to call out things that upset you just as much as you have the right to commend the things that make you satisfied.
You have the right to step away from groups, situations, people who upset you.
You have the right to disagree with others. Having an opposing view does not mean that you are attacking another person.
You have the right to have an opinion on what you see in the world of diabetes – even if it is happening on the other side of the world. I was incredulous when it was suggested that I shouldn’t question something happening in a healthcare system of which we are not a part. (I may not use the healthcare system in the US or the UK or Italy or anywhere other than Australia, but I am allowed to comment on what I see being done in those places.)
You have the right to be passionate and not be told that is a character flaw.
You have the right to be emotional because diabetes is real in a way that only makes sense to those of us who are living with it or have a loved one living with it. I don’t know how to take the emotion out of this, so you bet I will be emotional at times. I don’t get to clock off at the end of the work day and not think about it.
You have the right to use the words and language that works for you when talking about your own diabetes and if anyone tells you that #LanguageMatters is actually preventing PWD from doing that, tell them to fuck right off. It’s not. It never was. It never will be, and anyone who says it is has missed the point of the whole movement.
You have the right to use the word ‘fuck’ or whatever else you want to use. Profanity helps some people and we shouldn’t be told to wash out our mouths if others don’t like us using those words. (Sorry, dad.)
You have the right to be the sort of advocate you want to be. Or to not be an advocate.
You have the right to share your experiences – even the ones that don’t shine a particularly positive light on health systems or HCPs. No one – NO ONE – should silence us when we turn to our peers to seek support, or talk about what is going on in our diabetes lives.
You have the freedom to talk about your own diabetes, especially in the diabetes online community which we created for this very reason – to be able to share our experiences, learn from each other, support our peers and build each other up.
So, this? This is me being me. This is me standing up and not going quietly. This is me saying that I will be the person with diabetes I need to be, because it’s the only way I can be true to myself and true to my community.

*Except vaccinations. I don’t believe in choice there.
When the diabetes community comes together, great things happen. And one of the greatest things I’ve ever seen has been Spare A Rose, Save a Child.
Most people now know the origin story of this annual campaign. The short version is that back in 2013, a group of US diabetes advocates came together to do something for the global diabetes community. Using Valentine’s Day to signpost the campaign, the idea was simple: ‘spare’ one rose on Valentine’s Day and donate the saving to Spare A Rose, Save a Child. That one rose saving was enough to provide a month’s insulin to a child in an under-resourced country. All funds raised would go directly to the charity Life for a Child.
It’s really important to understand where Spare A Rose started, and the community aspect of the campaign. This didn’t happen for any other reason than a group of people directly affected by diabetes wanting to help others who needed it: for the community; by the community. No one took credit, no one was the face of Spare a Rose, no one raved about their involvement or contribution. It was about the whole community.
That’s where you step in. Because Spare a Rose is a community campaigned, owned by everyone who has anything to do with diabetes, anyone and everyone can get involved. And there are lots of ways you can do that.
Obviously, you can donate. (Please donate!) That’s the first and most important call to action here! And it’s easy – as easy as 1 – 2 – 3!

But also, we need to get this outside the echo chamber of the DOC.
Change your twitter and Facebook profile pics to highlight Spare A Rose and tell people why you’ve done it – and encourage them to as well. (Twibbon has a super easy way to do that here.)
The Spare A Rose site has lots of different images and messages you can share. Of course, use your social media reach, but also print some out and leave them around your office or local café.
Share, share, share! Amplifying anything and everything you see about Spare a Rose helps get the message out. I make no apologies that my SoMe feeds will be seen as if through rose coloured glasses for the next six or so weeks. Roses are lovely. Spare roses save lives.
Last year was the campaign’s most successful ever, raising a total of USD$56,340 / AUD$79,447 (or 12 months of insulin and education for 939 young people with diabetes). We have a target this year that I’m afraid to say out loud, because it is so audacious, but if there is one thing our diabetes community does, it is come together for those who need it.
So, please, #SpareARose (or two, or a dozen) and save a child. Seems like an awfully good way to start the year.

So, this is 2020? How are you going? I returned from overseas to a country literally burning and choked in smoke; a government that is refusing to accept that climate change is real; and a news organisation making up the narrative to suit themselves (arsonists are everywhere, apparently).
Bet you didn’t expect me to get so political before midday on a Monday!
Today is my first day back at work after three weeks of holidays in New York with my family. We spent the time basically relocating our Melbourne life to New York: finding a favourite café that served decent coffee, drinking great quantities of said coffee, wandering the streets, playing with (other people’s) dogs, warming up in bookstores and catching up with friends. It was the perfect way to farewell 2019 and welcome 2020.
As I have mentioned a million times before, I don’t do resolutions. You may not know this, but I live with diabetes, and that in itself gives me enough reasons to not reach goals and targets. I don’t need to add another list of things of which to fall short.
For the last three years, I’ve chosen a word that I’ve hoped would oversee and direct my way of thinking and acting for the year. As it turns out, that was a load of rubbish. Because each time, as I searched for the word that I wanted to guide me, the one I settled on went against the very grain of who I am.
The words were pause, focus and reset – and behind them was the idea that I would respond in ways that were really out of character; words that would silence or calm my natural responses.
But that’s not me. I walk towards things (usually at pace), I’m impulsive, I’m reactive. Sure, these may not necessarily be the best traits for a mindful, calm existence, and they can be exhausting, but welcome to my life: Hi, I’m Renza.
This year, I’m ditching the word idea, and using a phrase that better suits me, and that phrase is Stand Up.
We are living in a world that does not need people to be silent. Manners are all very important, but it is very possible to have manners and be polite, but still challenge things that we see as not right. We don’t need to be told how to think, how to feel, how to respond to something that upsets us. We don’t need to tone police ourselves – or others. We don’t need to accept what we are given.
And in the diabetes space, we don’t need people to be meek and mild. We need people who are disrupters and who speak their minds and who call out the bullshit. We definitely need to make sure that the voice of PWD is the loudest in the room, and that anyone who tries, even for a second on any platform, to tell us to pipe down is called out for it.
We do not need people to go quietly, and I am somewhat horrified that I did just that at the end of last year when I was feeling intimidated and vulnerable online. If I’m honest, I don’t recognise the person who switched her Twitter to private and wrote this thread to explain it to the people who were asking why.
Being angry is okay because there is a lot to get angry about in diabetes care. Not standing up means that we accept the situation for how it is. We can do it in a way that is nice and friendly, but sometimes it takes more than that. And that is okay.
I have never cared about being popular in the DOC or being considered one of the cool kids. I have never worried about follower numbers. I searched for this community because I needed support and I needed to feel part of something amongst people who were just life me. Other people with diabetes.
When I re-read my twitter thread from before Xmas, my heart broke NOT at what had happened; but at how I felt that the only way for me to stop feeling so unsafe was to turn away from the community – MY community. It was this tweet that set my tears running again:

I thought that if I had wandered into the DOC for the first time instead of the welcoming place it was, I saw PWD being challenged, I would have run away. THAT was what broke my heart – the very idea that I would not have discovered people like Kerri, Georgie, Cherise, Melissa, Mike, Dana, Grumps, David, Manny, Jeff, Mel, Frank, Alanna, Kelly, Ashleigh, Scott, Annie, Alecia, Bastian, Daniela and so, so many others. I don’t know how I would have navigated the murky waters of life with diabetes without those people: MY people for whom diabetes actually invades our DNA and the DNA of our loved ones. People there for the right reasons – not for the accolades, not for increasing follower counts. They are community-minded, open to opposing ideas and thoughts, and don’t consider themselves superheroes.
If I had have gone quietly, I would never have learnt from them; never had the support of people who understand; never had people like that at my back when I do stand up.
So, I don’t go quietly ever again. I stand up as I always have. I accept that doing that will send me into periods of advocacy burnout; I’ll deal with that when it happens, surrounded my friends and peers who get it.
So yes, this is 2020. I’m back. It’s really nice to see you here.

Each year, as we stop, look back and take stock, the reason that we are feeling so tired becomes apparent. This year is no different for me; my work travel calendar was the most intense it has ever been, with nine long haul trips, some for only a day or two. Combined with regular domestic travel, I can truly say that I have seen the inside of airports far too much. I stopped adding up the trips I did once I passed 100 walks down airbridges to board planes because it was making me weepy.
But on top of the usual exhaustion this year, there seems to be an extra element of fatigue that goes beyond what I’ve experienced before.
But first, let’s talk highlights, because there have been many of them.
The year kicked off with Spare A Rose and whoa, did we start the year with a bang! With the true philosophy of SaR at the forefront (an initiative for the community, by the community), we not only reached our rather audacious target, we smashed it! A cheeky and opportunistic little extra push saw a smiling Grumpy Pumper unleashed to the whole world for just a moment The DOC didn’t break, but the final tally of for the campaign meant that 939 kids in under-resourced countries would be receiving insulin for a year. Amazing!
My favourite issue, #LanguageMatters, only went from strength to strength, and the publication of this piece in BMJ, followed by this podcast, was a brilliant way to get it outside of the diabetes echo chamber. The importance of language featured on the programs of major conferences such as ADA and #IDF2019 with stellar panels speaking about why it really does matter.
My diabetes turned 21 and tied up in all the emotion of that, my pancreas’ performance review didn’t go all that well. Maybe next year? (Unlikely.)
Possibly the most exciting, heart-warming, rewarding and humbling thing I did this year was co-facilitate a workshop in Manila with some of the most dynamic, compassionate and enthusiastic young diabetes advocates I have ever met. I’m thrilled have had a chance to catch up with a couple of the people from this meeting and can see the wonderful work they are doing in more than trying circumstances.
Peer support was never far away. One of my favourite digital campaigns came from Diabetes Australia (remember – I work there so consider my bias) with our The Lowdown campaign. What a brilliant way to showcase how a digital campaign can reach and connect people from all over the world, and encourage them to safely speak about a topic that doesn’t seem to get anywhere enough coverage. I spoke about the campaign’s success in a number of places this year.
My own personal peer support experiences happened all around the globe at conferences, advisory board meetings and other opportunities to see friends and colleagues with diabetes. These moments ground me and help me make sense of what I am seeing and hearing, and are critical for keeping me balanced.
A special shout out to these two peers and dear, dear friends: Bastian and Grumps. We saw each other an inordinate number of times this year, literally all over the globe, travelling on planes, trains and automobiles for our #DiabetesOnTour. I do think we should launch a calendar of the 2020 pics. (Admittedly, we may be the only ones remotely interested in that idea.) When I talk about my diabetes tribe, it’s friends like these two. We’ve celebrated through some pretty amazing things this year, stood up to elevate the lived experience over and over, and also counselled each other through the tough bits. We’ve held post-mortems of long days, sitting in hotel foyers and bars, trying to make sense of what has happened, working out how to always improve, and plotting and planning more and more and more. I am so grateful to them for being the scaffolding holding me up when I’m away from home and feeling overwhelmed.

So, now the reason for that elevated exhaustion…
When I first wrote about advocacy burnout back in January this year, I had no idea at the time that it would set the scene for a difficult and sometimes troubling theme for the year. I get tired and overcome at times throughout the year, but 2019 was different and I’m not really sure why.
There were moments this year where I did honestly wonder how much more energy I have to stand up over and over again to a lot of what I was seeing. I don’t like using war and battle analogies in diabetes, but I did feel that I was fighting a lot of the time. Diabetes advocacy is a tough gig to begin with. Adding burnout on top of it makes it seem shattering.
Being attacked by HCPs for daring to voice my thoughts and challenge their behaviour, or getting it from certain, more confrontational parts of the diabetes community, or having industry reps tell me I don’t know what I’m talking about for daring to suggest that maybe their lame attempts to simulate diabetes in gameshow-style gimmicks at conferences could be better directed at actually engaging and listening to PWD all added up.
Or perhaps it was the repeated examples of ‘diabetes for laughs’…and realising that we are a long way away from HCPs truly being allies in our daily encounters with stigma.
Or perhaps it was feeling that we needed to justify just how important the #LanguageMatters movement, and the decade of work we’ve done really is. I can’t even begin to tell you how upsetting this little incident was.
It added up and several times I’ve felt overcome. I feel like that today. Which is disappointing because on measure, the highlights, the positives and the amazing community should overshadow the negative encounters.
And that is why I’m taking a break from Diabetogenic. I need some time away from feeling as though I want to analyse what is going on and comment on it. I have a wonderful holiday planned with my gorgeous family where we will see friends and wander wintery streets, rugged up in pompom hats. And then, will warm up once back in Australia to finish recharging my seriously diminished batteries, ready for a new year that’s already shaping up to be so, so busy.
Until then, I hope you have a wonderful holiday season, celebrating however you see fit. Thanks for popping by. And I’ll see you in 2020, clapping my hands and raring to go!






 Diabetogenic
