
You are currently browsing the category archive for the ‘Real life’ category.
Last week, I was invited to speak as the consumer in a peer support symposium at ADS ADEA. My talk was called ‘People like me’ because more and more, I’ve come to understand that the real value for me in peer support is the combination of the masses with diabetes – as accessed through the DOC – as well as those who form a part of my ‘inner circle’, or tribe.
So, obviously, my first slide was this one:

And then, I introduced the audience to my tribe from last week:

People like me! The #DAPeoplesVoice Team (L-R) Ashley, Melinda, Renza, Frank
The peer support symposium was coordinated by the ACBRD. Last year, they produced this report for the NDSS. They brought together four speakers, each speaking about different considerations of peer support.
After I gave my personal perspective on the peer support that works best for me, Professor David Simmons from Western Sydney University spoke about the evidence. The idea (as outlined in the symposium abstract) was to ‘…identify ways in which they are in synergy and/or tension with one another’.
David began by speaking about the Peers for Progress model, highlighting its four core functions of peer support:
- Assistance in daily management
- Social and emotional support
- Linkages to clinical care and community resources
- Ongoing support, extended over time.
I can only speak for myself and my own experiences, but the peer support I have carved out for myself meets all these points. While points 2 and 4 are probably the most relevant to me, I certainly have used my peers to assist with the day-to-day grind of living with diabetes and have also found connections with clinical support through my peers.
My experience is certainly not structured or formal in any way, however, for me, it works and it works superbly. Which was another point that I made – we need to find the right sort of peer support and that may be different for different people.
Some PWD may prefer to have something that is very organised. I prefer a more ad hoc, dip-in-and-out-as-I-need-it approach, and focus my energies on what I require at specific times. I also love the online community and the support it offers because it meets many of the things I’m looking for: flexibility (there’s not a meeting on the first Monday of each month to attend and if I can’t make that, I miss out); broad reach and a variety of people (which means that I will always find someone to provide support, no matter what the issue; diversity of experiences so my own understanding of what is going on with others is constantly growing, evolving and, often, challenged; all over the world allowing me to connect with people whatever the day of day – or wherever I happen to be (speaking of which…anyone in Lisbon next week?).
Another discussion point during the symposium was to do with the need for evidence to strengthen the case for peer support, which will ensure adequate funding to run programs. I find this a slightly double edged debate, really. I understand that with limited funding, those holding the purse need to know that money is going to go to programs that are known to work. But equally, I know peer support works. People with diabetes know peer support works. Melinda Seed, clearly frustrated (as am I) at the constant need to defend the value and importance of peer support, posed an interesting question, here:

Now, I don’t doubt for one moment that HCPs get a lot of benefit from attending diabetes conferences. Of course they do – they hear from leading experts, learn about the latest research finding, network with colleagues, speak with industry about new diabetes technologies and treatments. The leave feeling inspired, have improved knowledge, feel supported by others doing what they are doing, and have new tips and tricks up their sleeves top improve their practice. They know that. We all do. And yet where is the evidence to support it?
(For the record, someone did point out on Twitter to Melinda that the difference is that conferences are privately funded and therefore do not stand up to the same scrutiny that programs seeking public funding do. Melinda responded (quite correctly) that this argument doesn’t really hold water as many attendees there attend on the ‘government dime’. It is an interesting discussion….)
I think one of the problems we might have is that we narrow the definition of peer support sometimes, and perhaps some people think that it’s too fluffy and feel-good, and just about sitting around someone’s kitchen table and chatting. But as I said in my talk, there is much more than mere ‘tea and sympathy’, (although, I’m reticent to dismiss the power of such interactions because I know that sometimes those moments do produce a lot of support from people who are otherwise feeling very isolated and alone.)
I am speaking at the World Diabetes Congress at the end of this year and will be challenging the notion that peer support is all about group meetings. It is more than the traditional ‘support group’ model. One example I gave was the Pumpless in Vienna story (yeah – I’ll tell that whenever I can!). It was through peer connections that my friend Jo found a pump. It can also be seen and found in other ways – camps, information sessions, structured education programs. Peer support can be found in a lot of places, even if that’s not the term we give to it.
CEO of Diabetes Australia, Greg Johnson, and me talking peer support after last week’s symposium.
Disclosures
Roche Diabetes Australia has covered my travel and two night’s accommodation for my stay in Perth as I am a presenter at the Roche Educators Day (RED). There is no expectation from Roche that I will write anything about the RED, but I expect I will because it’s always such an interesting and enjoyable day!
The remainder of my time in Perth is part of my role at Diabetes Australia.
A recurring theme throughout last week’s ADS ADEA meeting in Perth was the need to manage expectations. I think, in general, we do a really lousy job of this in diabetes.
We’re told that can expect to live a ‘normal life’ after a diabetes diagnosis, when that’s not necessarily the truth.
We’re told we can expect to eat whatever they want, when really, the effort that goes into calculating medication doses depending on the nutrient value of our foods is hard and it may be easier for some to actually limit food choices to make things a little easier.
We’re told to expect a cure in five years’ time, when the truth is that a cure is not even on the distant horizon.
We’re told that we can expect new technology to significantly reduce the burden of living with diabetes, when the reality is that sometimes, it’s more – not less – work.
We’re told to expect person-centred care, when, really, our health system, is not designed to cater for the individual needs of people living with diabetes.
We’re told that emerging technology will be fully automated, smart and cure-like, but we are not told that there will still be human-input necessary and that the devices are not as smart as a functioning pancreas.
We’re told that if we keep our A1c below 7% we can avoid complications, and yet, there is no guarantee, and some of us do develop complications despite an A1c regularly hitting that magic number.
We are told that if we count carbs and dose the right amount of insulin at the right time, we can keep our glucose levels in range, often neglecting to be told that there are a lot of other factors at play.
We are told all this, and then, when these expectations are not met, we are told we’ve failed. Or we are disappointed.
Here’s the thing. The tools are actually really great. Our health system here in Australia is mostly terrific. The majority of our HCPs genuinely do want to give us the best care they can. We don’t need to oversell things as much as we do.
Our expectations are being set so realistically high, that it’s impossible to meet them.
So, THIS is what I would like to say about all the things I’ve covered above to help manage expectations:
Your life will be different after a diabetes diagnosis. But that’s okay. Your new normal is going to be different to your old normal, but hopefully, there will be very things that diabetes will prevent you from doing. Acting like a pancreas is not really normal, but you can do it!
Yeah, you can eat whatever you want. But it’s undeniable that certain foods are harder to manage after your pancreas decides to go on strike. Find what works for you – and that can change. But do be prepared for food to become something that can be a little fraught because you may find that some of your most favourite foods are a little difficult to deal with.
Researchers are brilliant and amazing and the advances in diabetes management are actually quite mind blowing, but a cure? We’re nowhere near that yet. Keep up to date with everything and try to mine through it to work out what is relevant for you. Keep getting excited about management and tech advances – but do keep it in perspective. (Also – consider the source. I promise you that the Channel 10 news or Buzzfeed is NOT going to be where you learn that diabetes has been cured forever.)
You are going to have a lot that you will want to know and work through, and possible a variety of healthcare professionals to see. As wonderful as it would be to have someone to coordinate it all for you, you’ll have to put in the leg work to find the right team, the right service and the right people. And then, once you’ve found them, it’s still up to you to direct what you need. Otherwise you might find yourself at the mercy of a system that is not really going deliver exactly what you need to get the most from it.
You may have heard that in the US there is a (hybrid-closed loop) pump/CGM combo. Some are calling it an artificial pancreas. It’s not. The tech is incredible, but it’s not fully automated. It still requires calibration and it still requires operator input. This is not me being negative, because the tech is exciting. It’s me being realistic about the level of automation
No new devices are going to completely remove the load diabetes adds to your life, or your involvement in their operation. Insulin pumps need buttons pushed; CGMs need calibration, food needs to be considered. Full automation may be the goal, but it’s a while off.
An A1c of 7% or below will indeed reduce your risk of developing diabetes-related complications and there is a lot of evidence to support that. But it doesn’t eliminate the risk. That’s the annoying and somewhat unfair reality of diabetes. Unfortunately, it’s the reality. Obviously, do what you can to manage your diabetes as well as you can. But don’t expect that a number is a guarantee of anything.
Carbs and insulin are only part of the equation. How you’re feeling emotionally, illness such as colds and flus, hormones, nutrients other than just carbs, the phase of the moon (well, maybe not) … all these impact on your numbers. And they change. Don’t expect that there is an equation that will work all the time.
In life, we’re often told to expect the unexpected. But in diabetes, the unexpected is often only that way because what we have been told to expect is unrealistic. If we were told the truth, and provided with realistic expectations from diagnosis – and throughout our diabetes lives, perhaps we wouldn’t feel that we’re constantly falling behind and failing.
Here’s me and my boss talking about expectations in technology.
Disclosures
Roche Diabetes Australia has covered my travel and two night’s accommodation for my stay in Perth as I am a presenter at the Roche Educators Day (RED). There is no expectation from Roche that I will write anything about the RED, but I expect I will because it’s always such an interesting and enjoyable day!
The remainder of my time in Perth is part of my role at Diabetes Australia.
There’s lots happening, but I can’t look away from my Loop app at the moment because I’m so damn excited and obsessed! (I’ll be writing something about it sometime this week.)
But if I wasn’t doing that, I’d be (re)reading these things…
Why it costs so much to see a specialist
I’ve always paid to see my endos privately. In fact, I generally ‘go private’ for all my healthcare needs – I can’t remember the last time I was bulk-billed for a medical consultation.
It does cost a lot, and I am grateful I can afford it, but the excessive costs often discourage people from seeking the right care they need. Of course, we do have excellent public health in Australia. My choice for seeing HCPs privately include wanting continuity of care, and not being subject to frequently very long waiting periods.
This piece in The Conversation looks at why specialist care is so expensive. And what can be done to reduce costs.
Lookiee! A diabetes Wookiee!
For those who participate in OzDOC (and other DOC activities) you may have come across David Burren. I met David last week to talk all things tech (actually, I just fired questions at him about Loop and he patiently answered them without rolling his eyes even once). He’s started a diabetes blog all about diabetes and technology and, thankfully, it is in language that even I can understand.
Check out David’s Bionic Wookiee blog here.
Statues are like tumo(u)rs.
With all the nonsense going on in America at the moment, this piece from McSweeney’s most adequately explains why the ridiculous idea that statues commemorating less than favourable moments in history need to remain. Here’s my favourite part:
I view this tumor as an important symbol of your body’s history and heritage. Removing the tumor would be yet another example of misguided medical correctness in today’s liberal America. I protest this surgery and refuse to whitewash your rich medical history. The tumor must be kept prominently displayed inside your body.
Do better, America. We all know you can.
More on what’s on the inside
Mel Seed’s blog about normalising mental healthcare in diabetes follows on from DX2Melbourne and is well worth a read. Read it here.
Diabetes is just…
This…

Faster insulin coming to Aus
A couple of weeks ago, I shared on my socials the exciting news that ultra-fast insulin, FIASP, had received TGA registration. No actual ‘launch’ date info as yet, although next week is the ADS ADEA Annual Scientific Meeting, so we may hear more then.
And in news that we already know…
Apparently, CGM is not just for abdomens anymore… File under ‘No Shit Sherlock’.
Swear-y
My blog emails keep getting blocked by the profanity filter at my husband’s work. Every now and then, he forwards me the message he’s received which states that the email was not delivered due to ‘offensive language’. #SwearyWife
This Twitter account definitely wouldn’t make it through, but it’s one of the best things I’ve seen on the interwebs for a while. I’d like to print THIS up poster size and put it on the wall of my office/wear it on a t-shirt, but perhaps that’s not appropriate.
D-parents and sharing the scary parts of their child’s diabetes online
I’ve linked to Moira McCarthy’s writing before because I think that she gets it right every single time she writes about the role of parents in their child’s diabetes.
This piece asks parents to consider if sharing their child’s scary and dramatic diabetes stories online is doing more harm than good. (I rather clumsily explored a similar issue last year in this post.)
Read her piece at ASweetLife here.
4Ts on Diabetes Mine…
Last month, during National Diabetes Week, in an endeavour to get our 4Ts message out as widely as possible, the good folks at Diabetes Mine allowed me to write a little about our campaign. You can read that here.
Living and loving someone with diabetes
As much as I think I am the most delightful and easy-to-live-with person in all the world, I have to admit that diabetes can and does impact on all relationships… and makes me perhaps not the most delightful and easy-to-live-with person. Aaron and I chalked up 23 years together yesterday. Diabetes has been part of the equation for over 19 of those years.
Diabetes advocates Nicole Johnson and Lorraine Stiehl have written a new book which has been called a practical guide to loving a person with diabetes. I’ve ordered a copy and will be leaving relevant pages open for my loved ones to read.
You can get a copy of What To Do When Your Partner Has Diabetes: A Survival Guide from Amazon.
Meme-y and true
There are a lot of diabetes memes out there, but sometimes I see one that just hits the mark so perfectly. Such as this from a TuDiabetes community member:

At #DX2Melbourne last week, we had a live webcast in an attempt to include people not invited to be part of the event to hear from some of the bloggers and contribute to the discussion. The hour-long webcast was about diabetes and mental health.
With delusions of Jenny Brockie and Tony Jones, I facilitated the discussion – which was actually quite difficult as there were thirteen of us sitting in a row meaning we couldn’t all see anyone other than who was sitting directly next to us without leaning dangerously forward. Also, I kept nearly falling off my stool, which suggests that I am the most ungraceful creature to have ever been positioned in front of a camera.

I’d put together some questions and discussion points to guide the discussion, but was very open to any tangent the group wanted to take to really navigate and explore the topic of diabetes and emotional wellbeing.
As the discussion flowed, I couldn’t help but feel a sense of déjà vu. Another talk about how diabetes affects us emotionally; another talk about not getting the support from psychologists and counsellors that we need; another talk about how usually it’s not even recommended that we may need to speak with someone about the mental health aspect of living with a chronic health condition; another talk from well-connected diabetes advocates saying that there is more to diabetes than simply being told our A1c, or any other number for that matter.
Amongst all the chatter, I asked myself how many times I’d participated in talks, how many talks I’d given, how many tweet chats I’d tweeted in, how many blog posts I’d written that were about the emotional side of diabetes. And then today, on my TimeHop app came this tweet, from an OzDOC tweet chat about mental health, held exactly 12 months ago today:

I’m not saying this because I think we’ve ‘done’ this topic and should leave it alone now. Not at all. I’m just suggesting that we’ve been having the same discussions about this really important topic for a long time, and yet diabetes care still seems to have this imaginary, yet somehow real, line down the middle, with the physical aspects of diabetes to one side, and the emotional aspects on the other as if the two are not fundamentally connected.
I knew that there would be some people listening in who would be hearing all of this for the first time. It would be the first time that although they had probably worked out that there was something missing from their diabetes care, they weren’t sure what it was. Or, they may have known they needed to speak to a psychologist or a counsellor, but didn’t know who to ask about it…and anyway, they may have thought, surely if this was something that lots of people with diabetes feel, someone would have mentioned it by now, right? Right???
Nineteen years I’ve had diabetes. And for at least seventeen of them, I’ve understood and known the importance of checking in on how the emotional impact of diabetes is contributing to how I am managing my diabetes. Or how I am not managing my diabetes (see above tweet….).
The idea that we can separate our mental health and emotional wellbeing from our diabetes is ridiculous. A condition that permeates every aspect of our life, moves in, makes itself a home and lords over us with terrifying threats of what lies ahead, impacts on our abilities to manage the day-to-day physical things we need to do.
Those watching the webcast at home could submit questions for the panel. A couple of diabetes healthcare professionals were watching and one asked a question that, as I read it, made my heart sink. He said that he sees people with diabetes who he believes would benefit from seeing a psychologist, but he is concerned that they will be offended if he suggests it. He asked the panel for ideas on how to broach the subject without causing offense.
Why did my heart sink? Because the question showed that there is still so much stigma associated with seeing a mental health professional, that other HCPs – on the ball, sensitive ones who know and understand the intersection between diabetes and mental health – feel worried that they might upset someone with diabetes if they suggest referring to a psychologist.
Until we normalise psychological support – until at diagnosis when we’re introduced to our new diabetes HCP best friends and psych support is part of that team – the stigma will continue. I’m not suggesting that everyone will need or want to see a psychologist. But putting it on the list, alongside a dietitian and a diabetes educator and an eye specialist will at least people understand that, if needed, there will be someone there to help with that particular piece of diabetes. (And to be perfectly honest, I really do wish I’d seen a psychologist at diagnosis rather than the dietitian who has scarred me for life with her ridiculously large rubber-mould portions of carbohydrate she insisted I eat at every meal!)
I don’t feel as though I am a failure because I have needed to consult a mental health professional in the past. I don’t think that it suggests that I can’t cope or that I can’t manage diabetes. I see it as important a part of my diabetes management as anything (and anyone) else. A lot of the time, I don’t feel as though I need to see someone. But other times, I do. And that is fine.
DISCLOSURES
Abbott Diabetes Care covered all my costs to attend #Dx2Melbourne, and provided all attendees with two FreeStyle Libre sensors and, if requested, a scanner. There was no expectation from Abbott that I would write about the event or any of their products, and everything I do write about it is my opinion, in my own words, and in no way reflects those of Abbott – or anyone else, for that matter.
On Monday and Tuesday of this week, I attended and facilitated Abbott Diabetes Care’s #Dx2Melbourne event which brought together eleven Australian diabetes bloggers. (All my disclosures can be found at the end of this post.)
(Just a recap – the DX (or Diabetes Exchange) series of events have now been run about half a dozen times. Other than #DX2Sydney and this year’s Melbourne events, the others have been held in hard-to-take cities including Stockholm, Berlin and Lisbon and have been attended by bloggers from the UK and Europe.)
#Dx2Melbourne reunited most of the bloggers who attended last year’s event, with some new faces thrown in for good measure. I was introduced to Alana Hearn for the first time, finally got to meet diabetes yoga guru Rachel Zinman, and caught up with Helen Edwards. (All the links to the blogs of the ‘repeat offenders’ who attended #D2Sydney can be found on this post.)
Some may believe that I am naïve in saying this, but the event is not about product. In fact, apart from a 45-minute presentation – the session that kicked off the two days – there was no other discussion about Libre or any other diabetes product unless it was specifically raised by one of the bloggers. Abbott did not have a new product to push; Libre has been out for over 12 months now in Australia.
(I am not, however, naïve enough to think that events like this are not part of the health industry’s 21st century marketing strategy. But, as I said last year when responding to a comment on my blog about this, this is the 21st century marketing. And I’m glad that consumers have a place in this strategy, because it would be far worse if industry was continuing with 20th century marketing strategies which completely excluded people with diabetes, and did not offer us any opportunity to directly engage and work with industry. Any device company NOT doing this is falling way behind and needs to catch up.)
As the Abbott team stated in their welcome, the idea of the DX events is to continue their commitment to bring together people living with diabetes to share ideas. And for Abbott to get an idea of what it is that is important to people with diabetes and what makes us tick – albeit a very select and privileged sample of advocates.
With this in mind, for me, the most valuable part of the event was the discussions that were completely driven by the bloggers. In an open session where we were exploring ‘why we blog’, I listened carefully as everyone articulated their reasons for going online and sharing their stories with strangers.
Reasons varied – some do it because they simply want to tell their story, some because they love to write, some have specific issues within diabetes they want to open up for discussion, some see it as an advocacy platform. What we don’t hear – ever – is anyone saying ‘Because I want to make money doing it’. I can be all evangelical about it and say it’s because we’re a choir of angels, but mostly I think it’s because we’re smart enough to know the limitations of what it is that we do, as well as understanding the strength is in connecting, not money-making.
We also considered the shortfalls of having an online presence.
I’m an over-sharer and I know that there is a lot I write that many others wouldn’t feel comfortable sharing – and some people have told me that it is sometimes difficult to read. I also write about issues that are of no real concern to others, and they are more than happy to let me know that I’m wasting my time and energy on such irrelevant (language) matters. I also know that as soon as I put something out there, I am opening myself up for comment – both positive and not-so-positive. We had a discussion about how we manage unwanted attention and, in the most extreme cases, trolling.
I have never regretted anything I have written or shared, and have never taken anything down because I’ve felt it was too personal. But I have had some very unwelcome and sometimes nasty comments sent my way.
I found this a really useful, but somewhat challenging, discussion. I have written about some very personal experiences, probably most notably, pregnancy loss. I’ve also written a lot about how diabetes impacts my mental health. These are two topics that are frequently hidden away, surrounded by shame and secrecy – precisely the reason that I am committed to writing about them.
However, the times I’ve been trolled – and fortunately, that hasn’t been often – it has been when I’ve shared very personal stories. They’ve been the times where I have found myself at my most vulnerable, and being so exposed makes any sort of negativity harrowing.
It was reassuring to discuss – and remind each other – that even though we are voluntarily putting ourselves online, we are not inviting people to be nasty and disrespectful. Online is real life, despite what some people may think. This is the space where many of us convene to work together, support each other and share information; it’s not a place for personal attacks.
I left the event on Tuesday feeling utterly exhausted, but also filled to the brim – a feeling that only comes after spending a solid period of time with others treading the blogging and advocacy boards. I was reminded of the similarities as well as the differences we experience living with diabetes. I felt buoyed by the various issues that draw our attention. I felt desperate at the access issues I still hear about – both here in Australia and overseas. But most of all I felt part of something that is much bigger than me, much bigger than my blog and much more powerful that anything I can do on my own.

Abbott Diabetes Care covered all my costs to attend #Dx2Melbourne, and provided all attendees with two FreeStyle Libre sensors and, if requested, a scanner. There was no expectation from Abbott that I would write about the event or any of their products, and everything I do write about it is my opinion, in my own words, and in no way reflects those of Abbott – or anyone else, for that matter.
I was slightly mortified at an exchange I heard recently between a person with diabetes and a healthcare professional. The HCP was correcting the PWD, who repeatedly referred to themselves as ‘(a) diabetic’, urging them to not use the word as some find it offensive.
Sometimes, it seems that we forget that the idea of discussing, and hopefully improving, the language used about diabetes is to better the experience of people with diabetes. My personal crusade is not about completely eliminating the word ‘diabetic’, for example.
I know many people with diabetes who use the word – as both a noun and an adjective – and are very comfortable to refer to themselves that way. This piece from Mel Seed at Twice Diabetes explains why she is more than happy to use the word. I appreciated her side of the debate. It all fits neatly into my philosophy of ‘My diabetes, my rules’.
But the point of the whole #LanguageMatters movement is not about people with diabetes defending the language choices we make. It’s about others. The Diabetes Australia Language Position Statement as never intended to be for people with diabetes. It was always for healthcare professionals, the media and the general community.
Rosie Walker, on her Successful Diabetes blog, captured it all perfectly when she said this in a recent post about diabetes language matters:
‘This is not a call for people living with diabetes themselves to ‘mind their language’. Anyone is perfectly free to refer to themselves and their condition however they wish – as in most other areas of life. This is about how other people, and especially health professionals and scientists, use language in relation to diabetes and those with it, and especially when they are not in earshot or attendance…’
When a healthcare professional tells someone with diabetes to not use a word to describe themselves, it’s just another example of trying to control the PWD. In the same way that we want choice about the devices we use or the treatment plan we employ, we demand choice in the words we use to describe ourselves and our diabetes.
I have started a separate page on Diabetogenic about all things #LanguageMatters. Click here or on the link at the top of the page for more.

You know that old word play about why we should not assume anything? Because ‘assume’ makes an ‘ass’ out of ‘u’ and ‘me’. Yes, it’s lame and I don’t like using ‘u’ for ‘you’ (because I’m a word nerd and don’t do ‘text speak’), but the sentiment is good.
There are so many assumptions that come with diabetes. And almost all of them are destructive.
‘People with diabetes must have eaten too much <insert food/drink type> as a kid.’
‘People get diabetes because they’re fat.’
‘People get diabetes because they don’t exercise.’
‘Diabetes means you are sick.’
‘People with diabetes could be managing better if they just tried.’
Many of us will have had these sorts of comments made directly at us. Some of us will have heard people say these things. Most of us will have seen these sorts of comment perpetuated in the media and in popular culture anytime diabetes gets a mention.
And they are all wrong.
It’s time that we removed all negative assumptions and replaced it with just this:

Imagine how different things would be if that was the starting point of diabetes discussions. Instead of the judgement and finger pointing that often is associated with a diabetes diagnosis, the first thing that everyone said was ‘And now let’s talk about living well with it.’ Instead of the threats, the attitude was ‘You can thrive with the right treatment’.
Finding out someone has diabetes does not in any way give you a window into their life or an indication into their behaviour. But it does tell you that they have a health condition that requires regular management and the best possible treatment.
Imagine how much easier life with diabetes would be – and how much kinder the conversation would sound – if the next time we told someone we have diabetes, the only thing we heard was ‘Are you getting the healthcare and treatment you need?’
Wouldn’t that be a great place to start the conversation?
There have been many occasions in my daughter’s twelve-and-a-half years that, as we’re about to walk out the front door, we’ve looked at each other and stopped. ‘Well, one of us is going to have to change…’ one of us, usually I, say. There we are, standing there in almost identical outfits.
But despite her affinity for stripes and jeans, and oversized grey cashmere knits, and constant comments about how much we look alike, she is not me. We are different people; we like a lot of different things; she loves ice-cream and I really don’t; we have different things that bother us.
I seemed to forget that in the last couple of days and a gnawing feeling in the pit of my stomach – a problem that is mine – overtook my rational side, and I thrust it upon my girl.
This story isn’t about my kid – I am not here to tell her story. This tale is about how I dealt with my fear of her developing type 1 diabetes.
To set the scene: she has been a little under the weather. Before the end of last term, she had a head cold. Her lips were dry and cracked from having to breathe through her mouth, and she was revoltingly sniffily.
She had two very relaxing weeks at home to mark the break between semesters one and two, and returned to school last week very rested and perfectly well. And came home on day two of term complaining of a sore throat, sore head and dizziness. The next morning, she woke up with a full-blown head cold again, and she said her stomach was also a little sore and upset.
This persisted for the rest of the week and over the weekend, so I decided it was time for her to visit the GP. I made an appointment for the middle of the week and as we waited, she continued to complain of a sore stomach and some nausea. She was tired and generally poorly.
And that was where the gnawing monster started to rear its most ugly head, whispering viciously to me. ‘She’s drinking more. Isn’t she?’ came the first comments. ‘Did you notice how many times she has refilled her glass with water?’ it hissed as I stood in the kitchen throwing together dinner, and she popped in to mention something to me. ‘Didn’t your mum say something about her drinking a lot when they took her to the opera a couple of weeks ago?’ I was reminded. ‘She went straight to the bathroom the second she got home. She’s been doing that lots…’
Suddenly I found myself noting empty glasses in the house and listening out for the loo being flushed. I surreptitiously glanced at her when she walked into a room, assessing if she looked as though she’d lost any weight recently. (She didn’t.)
Eventually, as casually as I could, I asked her if she’d noticed any changes in how she was feeling. ‘Darling,’ I said, as we sat on the couch during a commercial break in Masterchef. ‘Have you noticed that you’re thirstier than usual?’ I scrolled through my phone as I asked her, not really looking at anything blur by and pretending that it was just a passing comment and I hadn’t really stopped breathing as I waited for her response. ‘Nup,’ she answered.
When she came back from the bathroom a little later in the evening, I asked her, in the same (false) off-the-cuff way if she thought she was needing to pee more frequently than usual. ‘No,’ she replied, without hesitation.
As nonchalantly as possible, I said, ‘Sweetie…I feel like…I’ve noticed that you seem to be drinking more…and maybe going to the bathroom a little more than you usually do,’ I hated myself for saying it to her and drawing her into my concern.
‘No. I haven’t.’ And she told me how many times she remembered going to the bathroom that day. She reminded me that she keeps forgetting to take a drink bottle to school and sometimes doesn’t drink anything until she gets home. (I ignored that bit of information, even though I probably should remind her to do something about that and hydrate regularly…#BadMotherMoment2198756)
I should have let it go. But I didn’t. ‘I’d really like to check your blood sugar. Would you let me do that?’
(I’m going to stop there, because even as I write this I know how I sound. And in an effort to defend my behaviour (mostly to myself rather than anyone reading) I want to point out that I have checked her blood sugar no more than about half a dozen times in her whole life. I don’t whip out a meter and jab her at the first sign of anything out of the ordinary. I just don’t do that and never have. But regardless of that fact, it doesn’t make it right that on this occasion I allowed my anxiety to spill over and start to become hers.)
In what I can only call one of my less excellent parenting moments, I asked her several times, even though she refused, until she eventually stormed from the room telling me that there was no reason for me to be feeling worried about this because she was not drinking more or peeing more.
I’ve not been able to stop thinking about the whole situation. I am horrified at how I allowed my irrational, unfounded fears to flood out of me. I am angry that the worry that is always in the back of my mind was allowed to grow and grow and unleash its full force onto my darling girl.
In the past, I have sought help from a psychologist about these fears and concerns. I know that I am irrational. I also know – of course I know – what the stats are, and the percentage chance that she will get diabetes. I also know that if she does, we are equipped to ensure that she gets the best possible care and the best possible support. I know it will not be the end of the world.
But mostly, I know that my fears are not her fears and never should be.
We went to the GP. My kid outlined her symptoms, and mentioned that I thought that she was going to the loo and drinking more than usual, but denied that was the case. Pleasingly, the GP did a urine test. All was fine.)

One of us had to change. (NYC 2014)
(Settle down, Mum & Dad…)
I don’t have any tattoos on my body. And I rarely wear medical ID jewellery. How are these things connected?
Well, a lot of people with diabetes have diabetes tattoos, often on the inside of their wrists. Many say the reason they decided to tattoo their medical condition quite prominently on their body is because they don’t like to wear medical ID jewellery, (or don’t want the hassle of remembering to wear it). A tattoo is as permanent as you can get! Once it’s on, it’s on!
I’ve never really been interested in getting a tattoo, and I certainly have never even entertained the thought of getting a medical ID tattoo. This is obviously a very personal decision and I actually really like a lot of the diabetes tattoos that I’ve seen online. But it’s just not something that is very ‘me’. (And perhaps somewhere in this deeply cynical body of mine, a teeny tiny part of me that things maybe, perhaps, possibly there will be a cure for diabetes in my lifetime. And that unicorns exist.)
I do try to make an effort when I am travelling alone to wear my medical ID bracelet that I bought from a number of years ago. But the truth of the matter is that I very, very rarely do. Call me vain or shallow (guilty, guilty), but I don’t like the look of most medical ID jewellery, and even more, I don’t like looking down seeing a constant reminder of my medical condition staring back at me. I love wearing bracelets, but one that screams ‘chronic health condition’ is not really what I want to see when I am typing away and hear the jingle jangle of my bangles.
Today on my Instagram feed, this came up:

It’s from Pep Me Up Diabetes Blog which is run out of Germany by my friend Steffi. Steffi is awesome. I’ve met her in person a couple of times now as she’s also part of the Roche Bloggers Group. To date, her business has mostly sold very cool stickers for FreeStyle Libre sensors and scanners. She gave me a couple of stickers last year in Munich and I quite enjoyed sporting this one on my arm over the top of my sensor:

Now, Steffi has broadened her business to include temporary tattoos such as the one showcased on her Instagram feed today, as well as a couple of others which are also fabulous. In fact, if I were to get a permanent diabetes tattoo, I suspect that it would look like one of these:
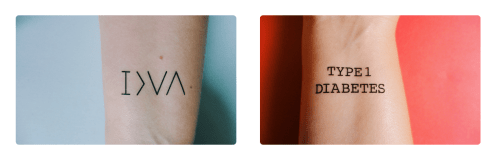
(The first one means ‘I am greater than my high and lows’.)
I can see the merit of using a temporary diabetes tattoo. For me, travelling alone would be the time that I think it would be most appealing. But there are a lot of other situations that would be great too: music concerts and festivals, large sporting events, or even as a ‘try out’ for a more permanent inking!
I really love this idea – well done Steffi – and it is another example of some truly wonderful and fun things that are going on in the diabetes world by people with diabetes. Do support them if you can!
Want your own temporary diabetes tattoo? You can order here. And Steffi ships all over the world. Even Australia!
GIVEAWAY!
Steffi has kindly offered to send me a couple of tattoos for a giveaway. Want one? Click here and tell me when and why you would use one of these tattoos.
Wait – I think I found an alert bracelet I like! As I was scrolling through the Pep Me Up website, I found this and ordered it!





 Diabetogenic

