
You are currently browsing the category archive for the ‘Awareness’ category.
I regularly say that I wish I had an assistant to take care of all the diabetes admin. I’d like to be able to hand over all the scheduling, paperwork and the general keeping track if it all that takes time, brain power and forces us to find room that those not living with diabetes can dedicate to making sure they remember if there is milk in the fridge or when the new season of The Good Place starts.
It would be a thankless job, and I doubt that anyone would be interested in doing it, but I can dream.
A couple of weeks ago, Diabetes Australia officially launched KeepSight, the first ever national eye screening program for people living with diabetes. It’s actually a super easy concept: PWD register to be part of KeepSight and then receive reminders when it is time to have an eye check. No more needing to remember the last time you had a check-up.
This is similar to the cervical screen program that has been around for a number of years now. I have relied on reminders from that program to alert me when it is time to make an appointment for a screening check. KeepSight will help us keep track of our eye checks.
I could give stats about the number of people who are missing out on regular eye checks, and even more stats about rates of diabetes-related eye complications. But I won’t. Because that is not what is getting me excited about this program.
I’m excited because this is one of those simple ideas that goes towards making our lives with diabetes easier. And, quite frankly, there’s not enough of that happening!
Click on the link below; it takes literally two minutes to register.

Now, if we could just find a way for insulin scripts to never run out, diabetes supplies to be endlessly replenished when running low and all our other appointments sorted, we’d be halfway to making this condition just a tiny but easier to manage.

Disclosure
I work for Diabetes Australia, but I am not writing about this because I have been asked to. I am doing it because I genuinely think this is a program that goes towards helping those of us living with diabetes and I will always share anything that does that.
But you do need to be aware of who pays my salary each week and consider my bias when I share things by my employer. You have a right to know that, which is why I will always make sure that it’s clear – each and every time I write about anything in which I am involved. Transparency is important.
This post marks one thousand posts here on Diabetogenic*. That’s a lot of senseless rambling, ragey-moments, times celebrating and despairing about diabetes, and links to brilliant ideas and post… or to things that have either amused, frustrated, delighted or annoyed me.
A thousand posts in and diabetes is still a constant in my life (damn it). And I remain not good at diabetes…and I have many of those thousand posts to prove it.
There are clearly some recurring themes that I write about. I say that I am a one trick pony, but perhaps that’s not completely true. I seem to have a few tricks up my sleeve, really. And now I’m confused, because ponies don’t usually have sleeves and my metaphors are very, very mixed.
Here are the things that seem to have taken up a lot of writing time and words over these thousand posts…
 Most of the time, I am pretty positive about living with diabetes. Let me be clear: that doesn’t mean I love it, or even like it. But I feel that generally, I know where it belongs in my life and it seems to fit in that place as well and happily (begrudgingly) as it can.
I know that one of the reasons that I feel this way is people in the diabetes world I am lucky enough to call friends and peers. Online friends, in real life friends and those who cross both boundaries are a critical part of my living-well-with-diabetes strategy. Knowing that there are only a very few places around the world where I couldn’t find someone from this community to have a coffee/tea/prosecco/mojito with gives me an incredible sense of comfort. (And reassurance in case of diabetes emergency…)
I say that my peers with diabetes help me make sense of my own diabetes and that’s true. Knowing people who understand innately what it is like to share a body with diabetes means that I never feel alone. Diabetes is so isolating at times – even for those of us surrounded by great people who support and encourage us. As much as I need those people and am grateful for them, it is others living with diabetes that help me realise that I am never, ever alone in dealing with the ‘diabetes things’.
The diabetes online community is made up of lots of people and not all have diabetes. We each bring our own experience and perspective to it. I’ve learnt so much from those living arounddiabetes and how they incorporate it into life, because it comes with its own set of challenges and victories. That is why the community is so valuable – its diversity and range of experiences and perspectives.
I regularly talk about the value of community and diabetes peers and finding our tribe. It can take time to settle into just who and what that looks like, and it changes because there are always new people around. But it is so worth it. My tribe? I love them so hard.
 I am not the tattooing type but if I was, I think that I would have this phrase inked on my body somewhere (or maybe I’d be really pretentious, and have it written in Latin: Nihil de nobis sine nobis, according to Google translate.) It remains a frustration of mine that this isn’t the starting point for pretty much anything and everything to do with diabetes care. The fact that we still need to fight for a seat at the table – or a ticket to a diabetes conference – is, quite simply, not good enough. Having others speak for us, on our behalf thinking they know what we need, is offensive. It should never be the case that non-PWD voices speak for us or over us. Ever. Our stories are powerful, but they are ours and we should have the platform to tell them in our own way; in our own voice. Tokenism is rife and sometimes, that frustrates me even more than when we are completely excluded. The delusion of inclusion is, I think, worse. Whilst there may have been some strides made to true co-design and inclusion, we have not come far enough and until we get this write, I’ll have a lot of content fodder for this blog.
I like food. I write about it a lot. And I want to be Nigella. That’s really all I have to say about it right now…

Waffles in Brussels. Both were excellent.
 Apparently, stating the obvious is still necessary in diabetes. We are more than numbers; our A1c does not define us; our worth is not wrapped up in our glucose levels. We have been saying these things for years…decades…and yet there are still times that this is what we are reduced to.
New treatments, devices, drugs, education programs are measured in reduction of A1c. Perhaps this is because it can be measured, but talk about only getting part of the story. I can’t help but think that if PWD were part of establishing research protocols, there may be far more than numbers to assess the success of a treatment or therapy. (See also: nothing about us without us…)
 In recent years I’ve written about the issues specific to women, health, sex and diabetes a number of times because there is so little out there about it. And it seems it resonated with a number of women who wrote to tell me (and the HCP who saw me in the fresh produce section at my local Woolies and yelled how she loved my idea of giving lube in diabetes event bags).
Anyway…talking about the stuff that may not be the easiest is important. It’s the only way we get remove stigma and encourage people to share their stories. Which helps others. That’s why I have openly written and spoken about miscarriages and infertility. And eating disorders. (I know – not an exclusively women’s health issue.) There is nothing shameful or embarrassing about these topics. Other than we don’t speak about them enough.
Learning from and supporting others
 The Interweb Jumbles I write are my favourite (and cheat’s) way of pulling together all the things I’ve seen that have interested me and leaving them in future place for (my) future reference. Plus, I love sharing what others in the diabetes community and world are doing.
I have always benefited from the generosity of others in this community who have shared my work and I pay that back whenever and wherever I can. Supporting each other is critical.
There’s so much going on in the diabetes world all the time and I highlight the things that resonate because I think that if they mean something to me, they may mean something to someone else, too.
 From pseudo-science rubbish, to ridiculous made-up diabetes cures to anti-vax delusions. How much writing material have they provided!
I live in hope that one day – and may that day be soon – we won’t still have to read about these charlatans trying to convince us that all that ails us can be cured with fairy dust and positive thought, or that vaccines are evil and cause diabetes, or that ‘wellness warriors’ are the true experts and professionals when it comes to diabetes.
While a lot of what I write is spent mocking these fools, there is an underlying seriousness to it all. Who can forget little Aiden Fenton who died after his parents stopped giving him insulin, instead leaving him to be treated by a ‘slap therapist’?
Anyone who is sprouting any treatment that is not based in science when it comes to diabetes or perpetuating anti-vax rubbish is as barbaric as the man who was charged with Aiden’s death.
 Diabetes happens because of something not working properly with our pancreas. But it affects every single part of us – something that astoundingly still seems to surprise some people.
Considering our mental health and emotional wellbeing is critical when assessing just how diabetes impacts on our every day. For some, diabetes seeps into every single part of us and for others, we keep it at bay and manage around us. For most of us, there is an ebb and flow of just how that works.
And while we’re talking about the whole person, diabetes-related complications may be specific to a particular body part, but those body parts remain connected to the rest of us.
For so long, we get metaphorically chopped up with as only bits of us get attention and focus. But nothing in diabetes is ever in isolation. That’s just not how it works.
 The trick this (however-many-trick) pony is most known for is #LangaugeMatters and you know what, I’m happy to wear that. I really am. If I was to stop this blog today (thought about it…1,000 has a nice rounding off feel to it), and never spoke about diabetes ever again (oh, if only), I would not be disappointed if this was what people thought of when they thought of me and this blog.
Language matters. It does and I refuse to, for a moment, believe that it doesn’t. I am certainly not the only person playing in this space and I am so grateful to have a tribe of language matters peers and colleagues can rise above the small details to understand just why this issue does really matter.
___________
Thanks to everyone who has read one or more of these thousand posts. Thanks especially to the people who keep coming back. I can’t promise that there are going to be a thousand more posts. And I can’t promise that I will learn any new tricks other than the ones that I seem to have on repeat at times. These issues remain important to me and perhaps to you too.
* At EASD, my mate Bastian Hauck gave me a head’s up that I was getting close to publishing the 1,000 post on this blog. I’d not have had a clue otherwise. Thanks, Bastian!
I am blunt and I am direct. I am often criticised for my lack of finesse and accused of having the subtlety of a sledgehammer. Guilty, guilty, guilty as charged.
But I have always believed that the best way to address any issue is to get it out in the open, talk about it and normalise it so people feel comfortable discussing it.

New Yorker Cartoons.(Click for image details.)
This has resulted in some uncomfortable times. There was the time I spoke at a healthcare professional event about some research we’d conducted on diabetes-related eating disorders, and the subsequent information resource we’d developed about the issue which provided information for people could seek help. A dietitian stood up during the question time and told me in no uncertain terms that this work was irresponsible and that we had just written an instruction manual showing people with diabetes how to develop an eating disorder. I reminded her of the research I’d just presented which showed that over 60% of the women in the survey had explicitly stated that they had omitted, altered, or restricted insulin for the purpose of weight loss and suggested that no one needed an instruction manual – we already knew how to do it. I also pointed out that over 80% of the women had never had a conversation about it with a HCP, so perhaps it WAS time we started talking about it so people knew how and where to get help.
Then there was the time at ADATS when I introduced the concept of DIYAPS to pretty much everyone in the room, terrifying them all. That was fun. As was the bit where a couple of endos suggested that I needed to be ‘reined in’.
After writing a booklet on diabetes and pregnancy. After being awarded a grant to publish it as a national resource, we sent the booklet out to all women with type 1 diabetes aged 16 – 40 years. The response we received from a bucket load of parents was that they did not want this issue raised with their daughters and how dare us for sending them information suggesting they have sex and get pregnant. (For the record – the booklet did neither of those things. It did, however, reassure young women with diabetes that a healthy pregnancy was possible, and that pre-planning said pregnancy was the best way for that to happen.)
When I was at Diabetes Vic, my team developed two resources about diabetes and sexual health and contraception (one for young women and one for young men). We knew that this information was desperately needed, and that young people wanted to know about how to be safe having sex, but there were concerns that the response from some quarters would be that we were promoting promiscuity. (Surely that word should only be accompanied by someone who has teleported here from the 1930s.)
And, of course, the pieces I’ve written on sex and diabetes have elicited a huge discussion about how they had never before even seen anything about diabetes, women and sexual health – and, it turns out, it was the first time many women had even seen the topic raised.
There is so much more: I write about pregnancy loss, because as hard as it was to live through it, it was harder to feel alone. I write about the emotional toll of diabetes because too often all we hear about is the impact of numbers. I write about burnout because it is a reality for me – and so many others.
These taboo topics are elephants in diabetes rooms around the world and it’s time we did more than just acknowledge them – we need to change that.
Disordered eating behaviours, concerns and problems with sex and sexual health, diabetes-related complications, mental health conditions are facts of life. People experience them. There is nothing shameful about any of them.
NOT talking about them makes them seem shameful.
How do we get to a point where those topics that have been so difficult to broach previously become as everyday as a conversation about a broken arm in a cast; that when we need to discuss something about our sexual heath or mental health with a health professional we are as comfortable as talking about an earache?

I’d quite like this SHAG elephant in a room!
Today I’m talking about cervical screening checks. Because yesterday, I had mine. (Oh, did I mention that I’m an over-sharer?)
Let’s be honest. No woman ever gets excited about having a cervical screen. At least, no woman I’ve ever met. Maybe if they handed out lollypops at the end, (or something more applicable for the area being screened?), we might get more excited, but as things go, rocking up for our scheduled cervical cancer screening is not really one of those things we anticipate with glee. (Or maybe you do. And if so – good for you!)
My OB/GYN – who is now purely my GYN because the OB part of me has shut up shop for good – called me (well, his receptionist did) while I was in Berlin. The call came at some ridiculous hour of the night, so I ignored it, rolled over and went back to sleep, making a note to return the call when I got back to Australia.
I knew that was I was well overdue for a check-up – I’d been thinking I needed to make an appointment and was also a little confused about the new screening procedure and process. It’s changed since my last screening. I knew that pap smears were a thing of the past and that a new cervical screening check had replaced it.
But I didn’t really understand about the change to timeframes or just what the new check was all about. So, I made, and prepared myself for, the appointment.
I’ve known my gynaecologist for a long time now – about seventeen years. He knows diabetes and pregnancy which was why I started seeing him. He was the one who I went to for all my pre-conception care and then he was my OB each time I was pregnant. He has seen me at my absolutely lowest as I dealt with the heartbreak and trauma of recurrent miscarriages. But he also was the one who handed me our daughter the day she was born, so he has seen me at my most elated, too.
This time, I walked in with absolutely no intention of talking about babies, other than mentioning that mine is now fourteen which obviously makes no sense because surely I am still only 36 and I had her when I was three days shy of 31. (This is a lie. No one believes it.) I was there to talk about how hopeless I was because I’d completely neglected thinking about needing a cervical screening check. And have the said check.
There is a reason that I continue to go back to the same doctors for seventeen years. It’s because they don’t judge, and they treat me as though I have a life outside the body part in which they specialise. (Which is good when seeing this particular doctor, because I am more than my vagina.) Before getting to the reason I was there, he asked me how I was and what I was up to. We spoke about the work I was doing. He asked specific questions about my health and asked me how I found the Dexcom that was clearly visible on my upper arm. We started to talk about DIYAPS, and how that was working for me. He wanted to know about my family and how they were, and what sort of a kid the tiny baby he delivered on that day back in November 1998 had become. (She reads a lot more now. And has more sassy opinions.)
Then I mentioned that I had been a little remiss in organising my cervical screening check and started to say how I was usually a lot better at this and that I always, always make sure my diabetes screening was up to date and that I NEVER miss an appointment with my ophthalmologist, but that this one had slipped through the cracks. He didn’t shake his head and tell me to be better. Instead he said, ’It’s great you’re here today. Life is busy and there is a lot going on.’ It may not be healthy to love your gynaecologist, but after that comment I remembered why I had always been so fond of him.
He then explained how the new screening worked, and why the changes were made. He spoke about what was involved today and how long it would take for me to get the results. ‘We call you whatever the result,’ he said and I realised that was a really useful piece of information. If I had a missed call from his rooms in seven to ten days’ time, not knowing that calling everyone was routine, I would have worried that something was wrong until I’d been able to speak to someone.
He started by taking my blood pressure. ‘Is your blood pressure usually okay when you have it checked?’ he asked. ‘Yep. Always fine. Why? Is it high?’ My heart rate was slightly elevated, and I was anxious. (See point above about no one wanting to have this particular screening check.) ‘A little,’ he said. ‘But I know that you’d be anxious about this. It’s nothing to worry about if you have recently had your BP done and it was okay.’
I have always appreciated how this doctor, when asking questions, explains why he is asking them. ‘Any changes to your period, bleeding in the middle of your cycle, or bleeding during or after sex?’ He asked, going through what each of these things could mean.
The rest of the examination took all of about 5 minutes. He explained everything that was going on, and I distracted myself during the bit where I had a piece of cold metal inside me by asking about the HPV vaccination.
I’m not sure if that was necessarily the best time to have a conversation about why it’s important to have this vaccine (there’s more about it here, including who the vaccine is for and when they should have it). He told me it protects against the types of HPV that cause around 70% of cervical cancer, as well as other cancers (vaginal, vulval, anal, throat and penile), and protects against genital warts.
We then both had a lot to say about our frustrations with anti-vax lunatics and their anti-science idiocy, and why Pete Evans should be sent to an island (one other than Australia) and left to his paleo devices where he can’t harm anyone else. (Thankfully the cold metal instrument has been removed, and I was covered up by a sheet again by this stage. We were both getting a little ranty and I was waving my hands around; being completely exposed could have made that awkward…)
When I was dressed and sitting opposite him again, he asked if I had any questions. I had a few, and he answered them clearly. I mentioned again that I would make sure that I had future checks as scheduled and he suggested I be less hard on myself.
He’s right, of course. Diabetes alone puts so much pressure on us – as well as all the screening we need to keep on top of there is the daily stuff too. (I love that he understands diabetes and realises just what it takes to deal with it.) Add to it the other things we need to stay on top of – such as screening of our lady bits – and it’s no wonder that sometimes something will slip through to the keeper.
And of course, there are a number of other reasons that we delay or postpone having this particular check done. For some women, there can concern or embarrassment. Even if we know that the actual procedure takes only minutes, it’s not especially comfortable. And then there are concerns about the state of our lady garden. According to a 2018 survey by a British cancer charity, a third of women won’t make an appointment for a cervical screening if they haven’t waxed or shaved their pubic area, and are embarrassed about how their vulva looks. I could scoff and say how ridiculously shallow, but you bet that I have had that concern too.
I know that this, as with all screenings, is important because early detection of any changes means early treatment and that is always the best approach. And so, I’m trying to stop beating myself up for the fact that I was overdue getting this done and instead pat myself on the back for actually having made and kept the appointment. I’ve done my bit. I now wait for the results and then take it from there.
More information about cervical cancer screening here.
Click for source of image.
Have you ever heard of an ‘Everesting Challenge’? No? Neither had I until recently. It involves a cyclist climbing a single hill the number of times that’s required to reach a total ascent of 8498 metre to equal Mt Everest. Oh – it gets better. It has to be done in a single ride. It’s known as one of the toughest cycling challenges in the world and I’m exhausted just writing about it. Now I know what it is, I can confidently say that I will never be completing this challenge.
But Neil McLagan is, and he is doing it for a really good cause. He will be raising funds for Insulin for Life (IFL) Global. I’ve written about IFL Global before, and have done some (volunteer) work before, promoting what they do.
As a refresher, IFL Global is a not for profit organisation, raising awareness of the lack of insulin and diabetes supplies in developing countries. The organisation collects and transports insulin and supplies and then distributes them to clinics and health professionals in these countries, as well as offers a complications screening program in places where this simply does not happen.
IFL Global’s mission is that no one should die because they can’t afford or access insulin. Their efforts save lives and help those with diabetes survive and thrive in their communities.
Obviously this is something that I will support – not by starting to do extreme cycling, but by promoting those doing it. And that brings me back to Neil McLagan.
Neil will be undertaking his ‘Everesting Challenge’ by climbing Admiral Road in Bedfordale, Western Australia more than eighty times. Apparently, that is going to take him more than eighteen hours. It’s not the first time that Neil has undertaken this sort of challenge. Last year he rode solo and unsupported from Sydney to Perth raising funds for another diabetes cause. Over twenty days, he spent a total of almost 180 hours on his bike, riding a total of 4011kms (almost 2,500 miles). He says that his ‘Everesting Challenge’ will be one of the most physically and mentally difficult single day challenges. He’s not kidding!
Oh – did I mention that Neil has type 1 diabetes?
He is hoping to raise AUD$20,000, along with a lot of awareness about Insulin for Life Global. Without the work they do, a type 1 diagnosis for many people in the counties where they have a presence would almost certainly mean a drastically shortened life.
This is where you can help.
Look – if you’re inclined to get on a bike and ride it for the equivalent of climbing Mt Everest while fundraising for IFL Global, all the power to you. Please let me know and I promise to throw more than just a couple of bucks your way.
But if you’re like me and would prefer to sit in a café reading about people like Neil, you can still help.
You can make a donation by clicking here. Every donation counts – don’t ever think that $5 won’t make a difference.
And you can follow Neil’s story by liking his Facebook page here and following his adventures, and sharing it with your friends.
Please do consider making a donation to Neil’s efforts. Insulin for Life Global is truly a very important cause and is making a massive difference to the lives if people with diabetes.
Yesterday, Diabetes Australia launched a new campaign called The Lowdown (please read my disclosure statement at the end of this post). It’s all about hypoglycaemia, and designed to get hypos out in the open by encouraging people with diabetes to share the realities of what hypos mean, look and feel like.
I love this campaign because it’s truly about people with diabetes. You’ll see and hear our stories and our experiences, and it will provide a forum for us to learn from each other. (Vote 1 peer support!)
There is stigma associated with hypos. Have you ever had a low and been asked ‘What did you do for that to happen?’. Or has someone ever asked you why you are not better prepared if you find yourself without enough (or any) hypo food on you? Has someone overreacted when you have been low, making you feel that you need to manage them at the same time as dealing with your hypo? Or has someone told you that you shouldn’t be having (as many or any) hypos?
All these things have happened to me and the result was that often I simply wouldn’t say when I was low, or I would downplay the situation. Reading stats such as ‘people with diabetes have on average <insert arbitrary number> of lows a week’ always made me feel like an overachiever, because I could guarantee that I was having more lows than whatever stat was quoted.
One thing I could rely on was that my friends with diabetes never made me feel like lows were my fault, or that I was hopeless because I didn’t have enough stuff with me. More likely, they would silently pass me a few jelly beans or fruit pastilles and leave me to deal with things myself, which is exactly what I need to do when low.
The last thing I need is someone throwing a million things at me (‘Here…I have juice, sweets, sugar, a glucose IV…’)and stressing out (or even worse – saying that Iam stressing them out) and asking every two minutes if I am okay. (I know that people are doing this out of concern. But seriously, the last thing any of us need when we are low is dealing with someone more flustered around us!)
This campaign is for PWD by PWD and that is why I love it. I’m hoping it will help us understand that others are dealing with the same crap around lows that we are. And that it is nothing to be ashamed of. Getting things out in the open is always a good way to reduce stigma and make people feel comfortable talking and seeking the help they may need.
So, let’s talk about lows. Share your story and read what others have to say – remembering that, as always, we are not a homogenous group and you are likely to read a variety of different stories. That’s great! Hypos affect people in different ways. For some they are significant and can be terribly scary, and for others they are simply an inconvenience that just needs to be dealt with and then they can move on. No one’s experience is any less or more legitimate than another’s.

Just some of the people who have already contributed to #TheLowdown2019
How to get involved
It’s easy!
Share a video or photo about how hypos make you feel. Share your post on your social media account (Facebook, Twitter, Instagram etc.) using the hashtag #TheLowdown2019. Please make sure you use the hashtag so we can find your contribution and share it and add it to our website.
If you’re not on social media, you can email a photo of yourself (perhaps holding up a card with one word which best describes how hypos make you feel) to thelowdown@diabetesaustralia.com.au
This page of The Lowdown website explains more.
Disclosure
I work for Diabetes Australia and have had some input into the development of this campaign. I am writing about it because I hope that it will get more people engaged and interested in what the campaign has to say, and encourage contributions.
I have not been asked by anyone at Diabetes Australia to write about The Lowdown here or on any other social media platform (but I’m sure they’re pleased I have).
Transparency is always important to me and I declare everything relevant (and not relevant!) on Diabetogenic. You need to understand and consider my bias when I am writing and sharing. You can always contact me if you have any questions about this.
So, something happened to me in Berlin that hasn’t happened for a while. I had a hypo. Actually, I had more than one.
In one of those perfect storm situations where everything that could go wrong did, I found myself with a red Loop, no CGM, and in a pissed off mood. My Dex sensor had died in the morning and I couldn’t restart it because my transmitter died at the same time. I knew this was coming – I’d had the warnings. And I had a plan. I would use the reset app and get the transmitter going again.
Except it didn’t reset. I checked and double checked that I was doing all that I needed to do, but the bloody thing wouldn’t work. I still wasn’t too stressed – I had a back up transmitter with me, plus I was at a tech conference surrounded by DIY tech nerds (I say this with great fondness).
I put it all out of my mind, and focused on DOCDAY, launching our #SpareAFrown stunt and then getting on with the rest of the day.
Three hypos later (thanks conference hypo syndrome, running around Berlin like a headless chook and more activity than normal), I was exhausted at the end of the day.
But, as I gorged myself on fruit pastilles I realised a few things. I realised that fruit pastilles really aren’t all the tasty and actually a little gag-y when needing to get them down quickly.

Bleurgh
And I realised that the return of hypos made me very annoyed. ‘Three hypos today,’ I announced. ‘This is lousy.’ I complained to anyone who would listen, and probably stamped my foot a little too.
But there is a silver lining. Kind of. As I whinged and moaned about my day of lows, a friend asked if I had symptoms for my hypos. I stopped and thought about it for a moment. ‘Yes…I felt them all,’ I said. ‘You’ve got your hypo symptoms back,’ he said.
I hadn’t thought about that, but it was true. I had felt the undeniable heightened anxiety that indicated that I was low for each of the three hypos I’d had that day. My heart rate had increased a little – not too much, but enough for me to notice. And that feeling was confirmed with a finger prick check.
These hypos were relatively easy to manage – a few of the bleurgh fruit pastilles and all was good. If I had to explain them in one word it would be ‘annoying’. But I did feel exhausted and drained. I was more than just jet lag and conference-tired; I was jet lag, conference and hypo-tired.
By the end of the day, I had my back-up transmitter paired and the two hour warm-up passed. I calibrated and my Loop turned green, and said a little prayer of gratitude to the Loop gods. The hypos stopped, and the next day I went back to ticking along as I have become accustomed after eighteen months of Looping.
And that’s where I’ve been since then. Absolutely one of the best things about Loop is the way that it helps me manage lows. I’m not for a moment saying that the system is so perfect that there is no risk of lows. Of course there is. But these days, I get enough warning and the system does its bit so that a mouthful of juice or a couple of jelly beans is all I need to manage any incoming lows.
That day was the most I’ve thought about my own hypos in a long time. Of course, I think about hypos in general a lot. Being on the PAC for HypoResolve means that I talk and think about it a lot. And other initiatives, or talking with friends with diabetes means that it’s never a topic of conversation all that far from mind.
Which brings me to this…
There is a new website being launched by Diabetes Australia about hypoglycaemia. The idea behind it all is to reduce the stigma associated with hypos and also to encourage people with diabetes to share their own experiences of living with lows. Diabetes can be such an isolating condition – we know that. Hypos are part of the deal for so many of us. And yet, many of us are afraid to talk about it too much for fear we’ll be told that we’re not managing our condition properly.
This new project hopes to bring the conversation out into the open a little more and you can get involved.
If you are an adult with type 1 diabetes or type 2 diabetes on insulin, share what hypoglycaemia means to you, or even just share the word you would use to describe hypos. Email a photo and your words to thelowdown@diabetesaustralia.com.auand you could feature on the new website. Or, share a photo holding the word you would use to describe hypos using the hashtag #TheLowdown2019.
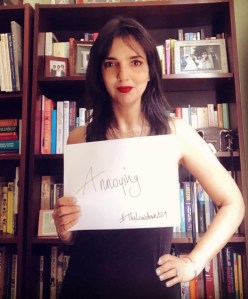
My third ATTD, and as soon as I started reading through the program, flagging the sessions I planned to attend and the technology I was keen to get my hands on and learn more about, a familiar feeling started to settle over me. It was there the first time I attended the conference and again last year.
And that feeling is that this conference, more than any other, reminds me just how unlevel the diabetes landscape is. With the shiniest of the shiny and newest of new technology and the most impressive treatment options available to people with diabetes on show, the vast gap between the haves and have nots is stark.
I was not the only person to acknowledge this. My first full day in Berlin saw me in an advisory committee meeting with diabetes advocates from across Europe, and when asked about the most pressing issues in diabetes, access was at the top of the list for every single one of us. Most (if not all?) of us in that room live in places with outstanding funding and reimbursement programs for diabetes drugs, technology and education – having to go without or ration insulin isn’t something we have ever needed to consider. Even those of us self-funding CGM are in a position of extreme advantage to be able to cover the significant out of pocket expense. But we all know that for millions of people across the world, this is not the case.
And then, later in the week at the Ascensia Diabetes Social Media Summit, another issue that came up again and again was choice. Choice refers to range of factors in diabetes. Choice of the type of technology we use, including the different brands; choice of the healthcare setting we feel best suits our brand of diabetes; choice of the specific healthcare professionals we see. It is also the freedom to be comfortable with our choice of technology, not feeling we need to conform to what others believe is the right thing.
But just how real is the whole idea of choice in diabetes? And when it comes to technology, how much of the decision about what we are using and how we are managing our diabetes is truly our own?
When access to basic education and treatments is severely limited, there is rarely any choice at all. In some places, a diabetes diagnosis is life and death, and surely in those cases all that people are choosing is life. How they manage that is probably not contemplated at all. In countries where diabetes does actually equal a death sentence, no one is debating whether TIR and A1c is how they would like to track their diabetes management.
But we don’t need to look to countries where outcomes are still so desperate to see lack of choice. Just this week, a very distressed mother of a young child with diabetes called me because they had just been told they were not permitted to use the pump they had chosen after careful deliberation and research.
This isn’t uncommon. Diabetes clinics across Australia make it difficult for PWD to be able to use the technology we have decided is the best choice for us. Sometimes that means not being able to use the specific technology we want (i.e. refusing to sign the necessary paperwork for a pump), or it could mean not being given the right to choose the brand of device we prefer.
At ATTD, I frequently heard about how healthcare is being transformed, and that may be true for those of us not disadvantaged by the country where we live and are trying to access care. We should celebrate the advances being made and the better outcomes so many of us have seen. But at the same time, we need to find a way to not get so far ahead of ourselves that we leave the most vulnerable further and further behind.

Click for original tweet.
Let me tell you what is worse than jet lag. Jet lag combined with food poisoning. These are the two extra circles of hell Dante forgot about.
While I am recovering and trying to get my body to accept coffee again, here are some photos from last week’s ATTD conference which was in equal measure amazing, overwhelming, frustrating, intimidating, brilliant and exhausting. I’ll explain more in coming posts, but for now, enjoy the images.
How to deal with jet lag when arriving in Europe #1: night time walk to major tourist site and be amazed.

How to deal with jet lag when arriving in Europe #2: find (half) decent coffee.

How to deal with jet lag when arriving in Europe #2.1: drink all the coffee.

And then drink some more.

#docday is always a highlight. Little dogs called Jamaica make it even better. (Jamaica on the left; Bastian on the right.)

Hello Solo… New pumps headed our way.

MySugr is ALWAYS on message.

Flavour of the conference #1: DIYAPS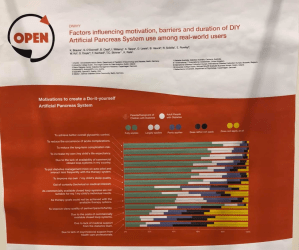
Flavour of the conference #2: Time in Range

Vegetables. I craved them.

Because there were so, so, so many dense carbs!

Not that I was complaining. (Especially when mini doughnuts came in Diabetogenic colours!)

Oh – did I say that #SpareARose was mentioned? A lot?

Such as at #docday. (Grumps looking especially grumpy because I’d just announced #SpareAFrown.)

And then? Then there was the smile-a-thon, as we smashed through target after target.

Next week, I’ll go into detail about some of the different sessions, highlights and satellite events I attended. It was a frantic few days – so worthwhile in every possible way. And as always at these conferences, finding those who live diabetes – themselves or with a loved one – provided the necessary grounding throughout the conference. This year, that support was even more pronounced with every single person who was asked to step up to promote #SpareARose doing so in spades. This is all the community. That is what it is all about…
DISLCOSURE
I attended the ATTD conference in Berlin. My (economy) airfare and part of my accommodation was covered by DOCLab (I attended an advisory group meeting for DOCLab), and other nights’ accommodation was covered by Roche Global (I attended the Roche Blogger MeetUp). While my travel and accommodation costs have been covered, my words remain all my own and I have not been asked by DOCLab or Roche Global to write about my attendance at their events or any other aspect of the conference.
Although Valentine’s Day is over and florists are back selling red roses at a reasonable price, the Spare A Rose, Save a Child campaign is still going. We run until the end of February which means that there are still ten days to go.
The tally for 2019 is already looking strong. We have hit just over $28,000, and we know there is another $8,000 or so pledged from a friend of the campaign, so we’re sitting around $36,000.
And that brings us to today’s blog post which actually begins its story back in August last year, and it goes like this…
One afternoon, I was working from home and an email came in from Scott Johnson. Scott is awesome and I adore him; and was intrigued by the subject title: ‘An idea from my dad’. Scott’s dad (who is clearly as awesome as Scott) did indeed have an idea. He thought that a great way to get people to donate to Life for a Child would be to get a smiling photo of the frowniest of them all in the DOC – The Grumpy Pumper. And I was charged with the task of convincing him to do it.
To be honest, I thought that this was not going to be an easy ask. There are literally hundreds of photos of Grumps online sporting his trademark frown. (See exhibit A) Convincing him to smile – and smile in a photo for all to see – was not probably going to be met with a lot of resistance.

Exhibit A
The conversation went like this:
Me: So Grumps, Scott’s dad thinks that you smiling in a photo should be used as an incentive to get people to donate to Life for a Child.
Grumps: Are you fucking joking? (Pause) Oh, okay. I’ll smile, but don’t get used to it.
We kind of forgot the idea, but with #SpareARose in full swing and the 2019 tally being so close to the $40k mark, we thought that now was the time to bring out this idea and see if it has legs.
Here is the deal. If our tally hits $40K by Friday night (Berlin time), Grumps is going to #SpareAFrown, and get his smile on at the MySugr event that is happening at ATTD.
This is where you come in. #SpareARose is a community initiative. It was started and is run by the diabetes online community. It is owned by us and it is a wonderful example of the community taking care of one another around the world. Grumps is a part of this community, and a part of the #SpareARose family, and he is a grumpy bastard. All good reasons to make a donation.
We’re calling on the community to step and donate to get us to $40K. If you have already donated, thank you. Is there any way you can throw in another $5? If you have been meaning to donate, but haven’t managed to do it yet, please do it now. Share the donation link with everyone you have ever met.
And share the #SpareAFrown idea, to get Grumpy to use muscles in his face that just don’t get a work out and help us get to $40,000, all of which will be donated to Life for a Child to provide insulin to children who would otherwise not be able to access it.
Let’s get Grumps to #SpareAFrown to save a child.

Click on the rose to donate.
DISLCOSURE
I am currently at the ATTD conference in Berlin. My (economy) airfare and part of my accommodation has been covered by DOCLab (I attended an advisory group meeting for DOCLab), and other nights’ accommodation has been covered by Roche Global (I will be attending the Roche Blogger MeetUp). While my travel an accommodation costs have been covered, my words remain all my own and I have not been asked by DOCLab or Roche Global) to write about my attendance at either events.





 Diabetogenic
