
You are currently browsing the category archive for the ‘Devices’ category.
‘Oh, it’s beautiful.’ These were the words the followed the sharp intake of breath as I saw the Kaleido pump stand at EASD last week. I didn’t say it to anyone in particular – I was wandering the expansive expo hall alone at the time. It was completely involuntary. The stand was a rainbow – I may have said to someone that it looked like a unicorn had thrown up in there.

You can read all about the Kaleido here. This is where you get to read about the specs and the details all tied up in the usual marketing spin that is inevitable when it comes to diabetes devices.
 My take on it – after a long chat with one of the developers – is that this is a nifty little pump. It is simple – really simple – with far fewer bells and whistles than available on other pumps. There is no CGM compatibility. At this point there is no bolus wizard calculator, however, following feedback from customers, the company is developing one.
The simplicity is actually part of the beauty in a lot of ways. Those of us experiencing data burnout might find some relief in a pump that is loud and proud in its claims to be a delivery device. Full stop.
 Enough about all that. What I want to talk about is how it looks. This could be because I am shallow – let’s start with that – but I think there is more to explore in here.
There was a lot of excitement from diabetes people at the event. There were a number of times that in conversations with fellow PWDs the Kaleido came up. Photos were instagrammed and tweeted, with a lot of attention being given to the gorgeous design and kaleidoscope of colours available. (Get it? Kaleidoscope…)
And inevitably, there were comments from people asking if colour is really something to be getting so excited about.
My answer to that is: actually yes.
At the moment, there are people around the world deciding what colour their next iPhone will be. Apple recently announced a rose gold case to accompany the grey and gold already available. People make decisions based on how it looks, the emotional pull, how it will look with what they are wearing.
 So why is it perfectly acceptable for decisions about other tech to be about how it looks and how it makes us feel, but it’s not okay for us to take this into consideration when thinking about which insulin pump we want to use?
Obviously, we need to feel confident that it will deliver insulin accurately, that it won’t malfunction if you look at it the wrong way, or that, if something does go wrong, there is good customer service. Of course all of these things are important.
But if we can assume that it will pass the accuracy test (approval processes are tough!) and that, being a new company, they will be doing their utmost to get their customer service game right, then how it looks and makes us feel is an absolutely reasonable and rational thing for us to consider when making a decision.
The first time I went to EASD (back in 2012), I met Fredrik Debong from MySugr and he said we need to make diabetes sexy. I agree. This is a condition with a serious image problem. MySugr is all about injecting some appeal and fun into diabetes, while producing a product (a kickass app) that people love and use because the functionality is brilliant.
Funking it up a little is a good thing. And this little pump is a step in the right direction!
No – I am not funded by Kaleido. No I did not receive any product. Yes, I did ask when it is coming to the Australian market. There is no official word on that yet, but we are certainly in their plan. The launch markets will be in Europe.

It’s day two of the 2015 EASD conference in Stockholm. Sunday and Monday showcased some impressive symposia – including industry announcements – and yesterday the official opening ceremony started the conference proper.
 We arrived in Stockholm around midday on Sunday after 26 hours in transit, so the afternoon was spent settling into our hotel which, bizarrely, has only round windows giving the odd sense that we are in a boat. Seventeen floors above ground level. In the sky. Weird, but gives an incredible view of each morning’s sunrise!
In keeping with EASD tradition, the conference is very science-y. There is little about the psychosocial aspects of diabetes and minimal input from people with diabetes. I have developed a twitch in my right eye because I keep hearing the word ‘diabetic’ and as much as I try to tell myself to get over it, it just doesn’t sit right with me coming out of the mouths of clinicians.
There is much mention of the ‘patient perspective’ and on Monday there was an entire symposium dedicated to it. Unfortunately, there wasn’t an actual ‘patient’ on the panel, which surely is weird. It is, right?
But despite the limited presence of PWD in the official programme, there are a lot of satellite events and activities taking place.
 Yesterday was #DOCDAY, an event organised by Bastian Haulk from he German online community. He had hired a space in downtown Stockholm and invited bloggers, advocates and others with diabetes to come along, network, chat, and talk about what we are all doing in our different communities and the larger DOC. Bastian asked me to say a few words at the introduction and I highlighted for me what is the most important thing when we are talking about the DOC: No one owns this community. No one is more important or more relevant or more powerful.
Sure, some of us are very fortunate that we get to actually meet IRL and attend conferences, but we do it as part of our jobs – whether it be like me (through my work at a diabetes organisation mixed with my online work) or through independent consulting or other work.
But regardless if you are in the room or following along on Twitter, everyone has the same right to be here and to be part of it.
Two separate blogger summits have been organised by industry – I will be attending the Johnson and Johnson DOC Exchange event tomorrow and Friday. These activities showcase just how smooth PWD and industry can work together – disclaimers and all that sort of stuff out in full view!

The Exhibition Hall here is, as expected, huge. Whilst the usual suspects are all here in force, there are also a few new faces on the scene. The Keleido pump is something to watch – if, for no other reason, than the gorgeous colour spectrum! More in coming days!
 While we’re talking new stuff, check out this gorgeous range of clothing from Anna PS (Scandinavia). Anna is delightful and started this company to address a gap in the market, producing high quality t-shirts, bathers, underwear and more to accommodate diabetes devices such as pumps, CGM receivers, pens etc. The clothing is of the most beautiful designs – the fabrics are divine. (And yes, she ships to Australia!)
There is a lot on show and a lot being presented and as in previous years, I have found this conference a lot more daunting than other meetings like ADA or our own ADS-ADEA. but there is plenty to write about and share. More in coming days.
I recently gave a short presentation on wearable medical devices that provide constant, real time data, and what that means for people on a day-to-day, minute-to-minute basis.
I had a slide that was a word cloud, including some of the (non-sweary) words I use regularly.

Being conscious that the crowd were not all necessarily diabetes-savvy, I focused on the data aspect and what that means for me emotionally more than the technicalities of the technology.
Afterwards, over tea and Arnott’s cream biscuits (Kingstons FTW!), I spoke with a (non-diabetes) healthcare professional – a GP who had never seen either an insulin pump or CGM before.
‘What great technology! It’s like you don’t have diabetes anymore,’ the GP said to me, clearly not having listened to any of my talk – especially the bit where I said sometimes tech could actually be more overwhelming and a constant reminder of my diabetes. Or the part where I said that as much as I love the devices, I still need to drive them and do a lot of work.
I shook my head gently and smiled. ‘I wish. And one day, I hope it will be like that. But this tech, whilst terrific, is part of my arsenal in the significant self-management tasks I do each day to manage my diabetes.’
He looked far less impressed.
‘Oh,’ he said. ‘So it’s not all that great?’
‘No, no. I’m not saying that.’ I wondered if he had actually heard anything I said. Because as much as I talked about the overwhelming side of the technology and all the data, I spoke a lot about how useful it is too.
‘It’s complicated,’ I said. ‘Sometimes I love this tech; other times I hate it. But mostly, I am glad I can use it the way I want.’
I munched on my Kingston biscuit, thinking. ‘I guess it’s kind of how I feel about my mobile phone. I love it – it means that I can reach everyone I want to whenever I want to and they can reach me. It means I can check Twitter and Facebook to see what everyone is up to. I can check the weather. I can receive emails and reply to them all the time. It’s great, right?’
‘And it’s a pain in the arse as well. Pretty much for all the reasons that it is great. But regardless, I wouldn’t be without it.’
He nodded. ‘I think I get it now. That’s an analogy that makes sense to me. Diabetes is so huge. A lot of it doesn’t make sense.’
It was my turn to nod. ‘So much of the time I am guilty of forgetting that not everyone gets the intricacies of life with diabetes. I try not to have expectations that people know about it, but find it difficult to explain. Maybe I need to come up with non-diabetes explanations.’
‘Like ‘life is like a box of chocolates?’ Forrest Gump managed to do it.’
I laughed. ‘Actually, that’s a pretty good analogy for diabetes too,‘ I said.
He thanked me and walked away, promising to learn more about diabetes technology.
I spoke with a few other people, ate another (couple of) Kingstons and got ready to leave. As I was collecting my things, I heard the GP speaking with someone else. ‘The technology is great,’ I heard him say. ‘But it can be frustrating at times. Kind of like the frustration from having a mobile phone and being reachable all the time.’
I smiled to myself and left the room.
A couple of years ago, when CGM was first launched into Australia, the typical thing happened. The device company took their shiny new product to health professionals around the country, showing off their wares. There were dinners and events and showcases, all highlighting the new technology.
Now, obviously with a product like CGM which requires HCP initiation, it is important to promote the product to the people who will be getting consumers hooked up. I understand that.
Nonetheless, it was with much envy that I saw HCPs being given a trial of the product. They were connected to a CGM and given an empty pump for four days – the number of days a sensor was meant to be worn.
I was desperate to get my grubby hands on one of these. I had read all about CGM and how much people with diabetes living overseas loved it. I read about how it made people feel safer and less frightened about hypos. I learnt that it helped to level out …well…levels. It sounded exciting. I wanted to try it myself.
The HCPs on the trial I spoke to were incredibly dismissive about this technology. Over the few days they were wearing it, I heard comments such as ‘It’s making me obsessive’ or ‘I can’t stop looking at the pump and watching what’s going on’ or ‘When I calibrate it, the numbers don’t match exactly’ or ‘The infusion set insertion process is terrible. I bled everywhere!’
I heard them say repeatedly that the technology was rubbish, that it wasn’t worth the cost, and that all it would do for people with diabetes is make them more distressed and anxious about their diabetes. Plus, it hurt.
Not one of them had diabetes themselves.
I started to get annoyed. I recall sitting with one of them after hearing this pronouncement yet again, feeling quite angry. ‘You know,’ I said. ‘You don’t get to say these things. You don’t get to write off this technology after a few days of wearing it, making claims that it is pointless. This is the latest technology that we have to manage our diabetes. It’s first generation so of course it’s not perfect. The second, third and probably even fourth gen products probably won’t be perfect either. But it is a new and worthwhile tool to help us manage our condition. It is exciting. We are hopeful. You don’t get to trash it.’
I remembered this whilst siting in a session on the first day here at the American Diabetes Association Scientific Meeting. It was a ‘Meet the Expert’ session and the topic was about personal experiences of the artificial pancreas.
Kelly Close (she’s amazing – read all about her here) was talking about her experiences of being involved in trials for a couple of different artificial pancreas projects. It was fascinating hearing about the AP and her excitement about the current technology being trialled – and about what is still coming.
Her enthusiasm was obvious. In fact she actually commented on why enthusiasm and excitement need to be employed when talking about advances in technology. We need to create a buzz and have people talking and asking questions and going on trials and writing (and blogging) about our experiences.
On the panel with Kelly was Chris Aldred (better known as The Grumpy Pumper) whose role in the session was to be the one challenging all the hype. He immediately explained that he had not used the AP, and had some questions. He was skeptical about a few things.
Being skeptical is absolutely okay. We shouldn’t ever blindly accept any new treatment without asking questions, but that actually adds to the buzz. It forces people who have experience with the device to talk about the good things and its limitations. It also helps alleviate a lot of the concerns people may have.
I thought back to my experience with the launch of CGM back home. When the HCPs who were privileged to try the then-new tech were trashing the product, I wish that there had been a voice to be able to respond to those concerns. I wish that the trial of the product had been extended to people with diabetes who could see it for what it was and how its application worked in the real world. And who could share their experiences – absolutely the good and the bad – with other PWD.
That’s exactly what I did when I finally got to try CGM. You bet the first gen was clunky. It did have accuracy problems and I did bleed a little most times the sensor was inserted. But whoa! It was amazing technology for the time and made a huge difference to me. When I understood how the trends worked, I knew how to respond to them. I could address things before they became problems.
I left the AP session on the first day pretty excited and inspired. And wanting to be part of the buzz – either as a trial participant or as someone on the periphery talking about it, reading about it, hearing people speak about it.
Read more at diaTribe where Kelly shares her AP trial experiences.
Today, diabetes can bite me. I changed out a perfectly good – and working perfectly – cannula this morning because it had been in for four days and I sometimes follow some diabetes rules.
Fresh out of the shower, I stabbed in my line and knew straight away something wasn’t right. I am more than used to (and expect) the little sting that comes with the introducer needle piercing my skin. But this one really hurt. And then when I primed one unit of insulin into the empty cannula it hurt. Really hurt.
So, I ripped it out. Which was a good idea! I present exhibit A:

This resulted in swear words galore because I am classy and a lady. I pulled another infusion set from the cupboard, ripped it open and shoved it in my skin. And again – ouch! I didn’t even bother to prime it – I just ripped it from my skin. Which again, proved a good idea. I present exhibit B:
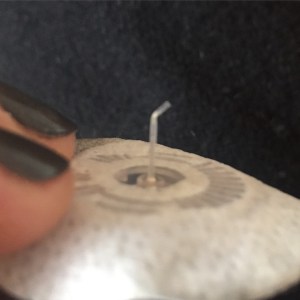
Ripping this one out was fun. It bled. Down my leg and onto the floor. So I swore again (more classy, more lady) and cursed the diabetes gods and possibly stamped my foot. Actually, I definitely stamped my foot. And threw the useless thing across the room at which point the puppy thought it had a new play toy.
The next cannula went it without a hitch and is behaving itself. Third time lucky.
So, what did I learn from today’s exercise? Not much. Probably that I shouldn’t follow diabetes rules and should have left the four-day-old-slightly-manky-but-working-perfectly cannula in. Because nothing good comes from following rules. Yep. That’s what I’m taking away from this. Also, I need a cupcake.
I could never ever work in advertising. A combination of cynicism and disbelief at anything I ever see in an ad would make me a difficult employee!
There is a very real gap between the truth of diabetes and what we see in advertisements for diabetes products. I frequently find myself shaking my head in disbelief at the way diabetes is portrayed.
This is what a stomach using an insulin pump looks like. That is my stomach (apologies if you are eating, drinking or just looking). Those dots are the ghosts of infusion sets past in various stages of healing. There is also probably some tape residue stubbornly stuck to my skin. Pretty (gross), isn’t it?

#NoFilter. Obviously
This is what a stomach in a pump ad looks like. Magically, any hint of previous infusion sites have disappeared.

This morning, here is what my meter announced my BGL to be. (Hashtag: fuckoff)

This is what the reading on pretty much every box and poster of BGL meters looks like. (Hashtag: bullshit)
 CGM graphs in real life look like the trajectory of rollercoasters with mountainous highs and cavernous lows, while the slick promotional materials show straight lines, nicely fitting in between the upper and lower alarm limits.
People in advertisements for diabetes paraphernalia are always outdoors, happy and rolling down hills, big smiles plastered on their faces. They wake up looking well-rested.
Real people with diabetes may spend time smiling and happy (I love rolling down hills – especially at this time of the year and getting all covered in Autumn leaves), but I’m putting it out there and saying that their glee is not because they have just done a BGL check. Unless the result is 5.5mmol/l. Each and every time. (See about meter photo. There was no smiling at that!)
I get it. No one wants to see my stomach on an ad for insulin pump therapy – that’s not selling units of product! But surely there needs to be a middle ground somewhere. I would like there to be an occasional BGL reading of over 15mmol/l on a poster for a meter. Because it happens. It’s not the end of the world and it doesn’t mean the meter is crap. And a stomach with a few pock marks from old infusion sets doesn’t reflect the quality of the infusion set. It reflects reality.
Diabetes isn’t pretty. It’s an ugly, scary and pretty un-fun thing to live with a lot of the time. That doesn’t mean that I spend most of my time in a ‘pity me’ funk, but I do admit – quite honestly – that it is shit at times. How about we aim for a bit of honesty and truth in diabetes advertising? Telling it like it is doesn’t mean we are weak or showing defeat. It’s just being authentic.
I have always known that stress affects my diabetes. Stressful situations – particularly prolonged ones – have the potential to send my BGLs into the stratosphere. Regardless of constant rage-bolusing or the complete avoidance of any food containing a scrap of carbohydrate, getting numbers in range when feeling stress is almost impossible.
The thing though that surprises me is how even small stresses can affect BGLs. Wearing a CGM gives great insight into this. Often, I see sudden rises in BGL that almost as suddenly drop back to within range.
After a day with a few unexplained (or unexplainable) spikes on my CGM graph, I decided to see if I could work out what was going on. These spikes didn’t seem to correlate with meal times, so I knew it had nothing to do with food intake.
As explained previously, I was wearing CGM under some duress, really. Aaron was away for work and it was on only for my peace of mind. To minimise feeling overwhelmed, I basically had my settings so that the only alarms and alerts I’d receive would be when I was dropping too quickly or when I was low. The high alarms were effectively turned off.
But after seeing spikes, I started to wonder what was happening. I turned the high alarms back on the next day and started paying attention to when I was starting to go high. Each and every time, it was because I was in a situation with some element of adrenaline-causing stress.
One time it happened when I was caught in traffic and I wasn’t sure I would make to school before the bell rang. I started getting more and more anxious that I would be late.
Another time, I was in a meeting that was running overtime and I needed to move my car before the parking meter expired.
And then, there was the time that I walked in the door to find the letter from VicRoads informing me that my medical review was fine and that my license wasn’t being suspended. And that I did not need to provide an eyesight report. (The outcome here was good, but before I read the letter, just seeing the logo on the front of the envelope, thinking about the difficult phone calls to VicRoads staff and taking a few minutes to consider what could be inside had my stress levels increasing.)
The adrenaline response is so clear on the graph. In all of these instances, there was a spike (not always huge, but definitely visible) that only lasted a short while. Often the blip would be only half an hour or so.
Stress isn’t always bad though. Had I been wearing a CGM when I jumped out a plane last year, I am sure that the stress response – from the excitement, the anticipation and the outright fear! – would have been reflected on the graph.
Excitement – from all sorts of things – may make you feel great, but it can still cause a spike. Managing stress-causing situations – especially those out of your control is sometimes impossible. And sometimes, you want to do things that are going to cause that blip. Some adrenaline-releasing activities can be very, very fun!
Keeping an eye on the leaps and bounds of my CGM graph reminded me (yet again) of the complexity of diabetes and how pretty much everything impacts on it in some way. I turned the high alarms off after a couple of days. I was starting to get concerned about the number of uncontrolled stress-inducing situations that I was having that particular day and the alarms themselves were starting to stress me out. So off they went. Because that was ONE thing I could control!
Last night, I rather smugly put this picture up on my Instagram:

‘Look at me,’ the picture screams. ‘I am winning at diabetes!’
And then, this morning, after eight hours of uninterrupted sleep, this was how my pump screen looked:

W.I.N.N.I.N.G.
So, riddle me this, why did I wake – after eight hours of uninterrupted sleep – feeling so completely and utterly exhausted? I wasn’t up overnight to go to the loo or let the dog out or deal with a low blood sugar. I just slept. Peacefully.
There was no explanation.
Until I looked at this:
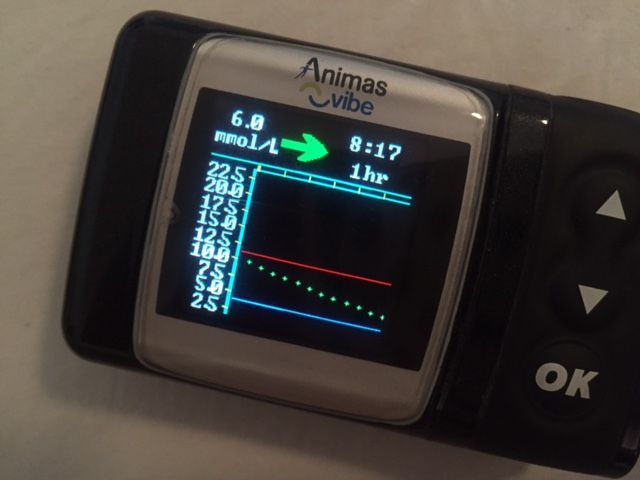
And this:
And this:

And then it all made sense. Except it didn’t. How had that happened? Had I sleep-walked into the kitchen, sleep-baked a pavlova and sleep-eaten it? Had I reached over in my sleep and eaten some of the jelly snakes on my bedside table?
The answer is no. All I had done in those eight hours was sleep.
Without my CGM on, I would have had that pre-bed BGL and the morning BGL as the only pieces of information. And it would have looked damn pretty. I would have spent all day thinking about how lovely and pretty and stable by BGLs had been overnight.
But with my CGM on, I know a lot more.
Which is great, except I’m not sure that I want to know. Because now I feel like I have to do something about it and quite frankly, I am still not in the headspace to be analysing glucose levels and making basal changes and being all diabetes-smart.
My CGM is on this week as a security measure. I really didn’t feel like putting it in, but I knew that I needed to. I am counting down until I can rip it out on Friday morning, which is a far cry from trying to get as many days as possible out of each sensor as a cost-saving measure.
I now know why I am not feeling particularly rested, but I feel even less rested with all this information at hand. THIS is when data is paralyising – when we just don’t have the ability – for whatever reason – to do anything with it and all it does is overwhelm us. Ever more.
I was sitting on the bed in my underwear, a towel wrapped around my wet hair, doing a full set change on my pump.
Mornings are a little hectic around our place. I am a pretty organised person but despite best laid plans, mornings still have the potential to head into a disordered mess. I blame the dogs – especially the puppy – who in their cute four-legged way have the potential to derail the morning routine.
But today, everyone was calm and just getting on with the job of getting themselves sorted and out of the house at the right time. Even Sooty was minding her own business, quietly chewing on a pair of Aaron’s socks in a corner.
The kidlet climbed onto the bed next to me to speak about something that was happening at school that day, talking a million miles an hour and brushing her hair at the same time. Excellent multi-skilling!
Without missing a beat in her commentary (or grooming), she watched me draw insulin into a new cartridge, flick the outside of the syringe with my finger and push a few tiny air bubbles out, a little spray of insulin heading into the air. I inhaled, thinking what I always do when I smell insulin, ‘The smell that keeps you alive’.
I connected a new line, loaded the cartridge into my pump, tightened the cap and primed. A couple of drops of insulin fell onto my bare legs.
And then, I peeled away the tape, pulled off the blue cap and pushed the cannula into my skin, quickly pulling out the introducer needle.
At that point the kidlet stopped speaking to me about school, her hairbrush poised mid-air.
‘Ouch,’ she said. ‘How can you do that and say it doesn’t hurt?’
‘It doesn’t,’ I said simply. ‘At least, not much. And that one really didn’t hurt.’
I feel that diabetes has desensitised me to so much. I have become more accepting of my own mortality and, even though I don’t like to think about it, I am resigned to a shortened life span. As I age, I expect limiting complications. I accept pain more readily. I know that my health cannot be taken for granted and that my immune system has the potential, at any given moment, to do something stupid. There are days that I feel an exhaustion that I am sure is connected to diabetes, but deal with it by simply getting on with things. I wear robot parts on my body and no longer even bat an eyelid when I catch a glimpse of them taped to my skin.
And I don’t feel the pain of needles anymore.
I looked at our beautiful daughter. ‘You would be surprised at what your body and mind are capable of, darling,’ I told her. ‘These things keep me healthy. I’ll do pretty much anything for that.’
She hopped off the bed and headed into the kitchen for her breakfast. I threw on my clothes for the day, gathered up the rubbish – the used pump line and cartridge, and packaging from the new ones – and followed her into the kitchen.
The smell of insulin lingered in the room.
Without opening my eyes – without really waking up – I reached under the covers, searching. It wasn’t there.
I ran my hand ran across my abdomen. Right…over my bellybutton…left. There it was. I found what I was looking for. Or rather, I didn’t find it.
My eyes flew open and I sat up.
Where was my pump? It wasn’t attached to me. I felt the little knob of my infusion set, but the smooth disc that connects it to my pump was absent.
There was a dry feeling in my mouth and my head was fuzzy. I continued searching amongst the tangled bed sheets until I located my pump. It was lying on the very edge of the bed, almost falling off. I reconnected it and started to assess the damage.
How long had I been unconnected? Disconnected? Not attached?
It was about 3am. We’d had a late night and by the time sleep came, it was well after midnight. I guessed that I’d been separated from my pump for about two hours. Not as bad as it could have been, but long enough.
I checked my BGL and discovered it was creeping up into the mid-teens, which explained the dry mouth. ‘Oh,’ I thought ‘And the need to pee.’
I got up, threw on a t-shirt and, pump in hand, went to the bathroom and then stopped by the kitchen to chug two long glasses of water.
Cherry, our cat, wound her way around my bare legs, pleased for company, as I stood over the sink, looking out the window into the dark garden. A wave of nausea rushed over me. Breathing deeply, I contemplated taking an anti-nausea tablet, but the feeling had passed. I stumbled back to bed after giving myself a correction bolus.
By the time I woke up in the morning, my BGL was in range and the dry feeling had gone, my head was clear. Crisis averted.
I am usually really diligent about reconnecting my pump if, for whatever reason, I remove it. I am particularly conscientious about it at bedtime because I am a notoriously heavy sleeper and the likelihood of me sleeping through climbing BGLs is high (as will be my BGL by the time I eventually do wake!). This is especially an issue when not wearing my CGM and there are no warning alarms to wake either me or (more typically) my husband.
This was the case last night. No CGM (I don’t want to talk about how I accidently ripped out my last senor AFTER ONLY 6 DAYS as I was getting dressed), no alarms. Just a pump lying dormant; dripping insulin onto the mattress instead of into me.
This week marks 14 years of wearing a pump. For over 5,000 days I have had this device attached to me for pretty much 24 hours a day. You would think that I simply would never fall asleep without it safely attached to me
And yet, I did. Because as much as having diabetes is part of my DNA, robot parts are always extra.
I got up and ready for work, and as I was driving in I realised that I’d forgotten to put on a couple of the enamel bangles I wear most days – especially when I am in all black, as I am today. Perhaps I’m just having a forgetful day, I thought, and weighed up the option of turning the car around. I decided that having forgotten my life-saving medical device at home would probably be accepted as an excuse for being extra late, however forgetting to accessorise would probably not. I proceeded to work, my arms unadorned.
One of my lovely and clever work colleagues came to the rescue though, and, MacGyver-ed me up a solution using nothing put coloured post it notes and sticky tape.
Once again, crisis averted.






