
You are currently browsing the category archive for the ‘Awareness’ category.
I’m a bit of a goody-two-shoes most of the time. I like rules; I like to play by them. If someone hands me a policies and procedures handbook, I read it and then tick boxes as I make sure I do what is expected of me. Playing by the book is my MO! (You can see why being diagnosed with diabetes is not really in sync with this philosophy…)
So, it pains me greatly when I see a rule that I don’t like – especially one that I can see no reason to be there!
I am in Adelaide from tomorrow for the Australian Diabetes Society – Australian Diabetes Educators Association annual conference. Actually, tomorrow, I am presenting at the Roche Educators Day which is very exciting and also making me a little nervous. Speaking to healthcare professionals about the benefit of using social media is sometimes a terrifying thought. In fact, the people listening are the definition of a tough audience. (So, if anyone who is attending tomorrow is reading this, please be kind and nice and gentle and open to discussing this topic. Please!)
It has been great that the planners of the conference for the last couple of years have actually bothered to consider how social media can be used to talk about what is going on in the presentations. There was some great tweeting last year – admittedly, mainly people from Diabetes Victoria and the Australian Centre for Behavioural Research, but nonetheless, definitely an improvement on previous years. (So maybe, all the talking to healthcare professionals about social media is starting to pay off??)
This is all great. All heading in the right direction! Social media at our premier diabetes healthcare professional conference is here to stay. So I was really disappointed to see this year that the social media guidelines on the conference website state the following:
The use of photographic, video, or other type of recording devices is strictly prohibited in all oral sessions (i.e., platform, plenary, invited, etc.) and poster sessions at the ADS ADEA 2015 ASM. Therefore, it is also strictly prohibited to post photos/images or video recordings from these sessions on any type of online site, including social media platforms, blogs, personal Web pages, etc.
Now, I recently got into trouble for breaking a similar rule. When I attended the ADA meeting in Boston, I was live tweeting Bill Polonsky’s sessions, and tweeted a couple of his slides*. Within minutes, the SoMe boffins from the ADA sprang into action:
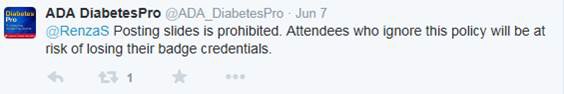
I was firmly rapped over the knuckles. There were a few follow up tweets from DOC peeps obviously as pissed off as me about the policy. We all thought it was pretty crazy.
So let me explain why I don’t like this policy.
I completely understand if there is a restriction around photographing unpublished data. That makes sense. But I believe that the people in the room are smart enough to not take photos of anything if they are told that it is unpublished. They would understand why there was such a restriction and, I believe, not publish the data.
But if the data is in the public domain and available for everyone, then what is the harm?
I live tweet conference sessions because it is a great way to capture what is going on in the moment at the meeting. I am also very aware of what a privilege it is to be in the room! Most people with diabetes don’t get the chance, so this is an opportunity to share what is being discussed.
Of course, I quote what the speaker is saying, or highlight key points, but with a 140 character limit, the value of a picture and its thousand words is never truer!
It also means that there is less chance of me misinterpreting what is being said.
Live tweeting from conferences is a fabulous way to reach a far broader audience – frequently an audience that may never actually be in the room – yet is directly affected by what is being discussed! And I have said it before, but one of the reasons that it is so great to have consumer reps in the room is because we share the information. How many of us actually have HCPs who do that when we see them?
I tweet and blog and talk about them – as do my peers – and that is how we find out what is hot, what is new, what is coming up.
This policy is ridiculous. And it needs to be changed.
*For the record, one of the tweets I sent at ADA was a photo of Dr Gregory House. Dr Polonsky was using a photo of him to illustrate a point. It was a good point. It was a good photo. Plus, I love Hugh Laurie and any chance to look at him. It was worth getting told off for!
Being fiercely independent about my health is something that I cherish. I have a strong need to own my own health and well-being and direct the course taken to manage my diabetes as best as I possibly can. I do this with full disclosure that the mess ups are mine as much as the successes. The buck starts and stops with me.
But sometimes – always, actually – it helps to know that there is support at hand when needed.
That help might be in the form of someone to accompany me to appointments (thanks dad, who has chauffeured me to almost every single ophthalmologist appointment I have been to in the last 17 years), someone to meet me afterwards over coffee so I can debrief and share what happened, or someone to actually sit alongside me whilst in the consulting room, taking note of what is being said. Having a second set of ears is always a great idea, especially if what is being covered off is challenging in any way.
I usually attend appointments with my endo alone, although sometimes, my mum may be with me to keep my company. We use it as an excuse to then catch up for coffee and cake. Other times, when there has been something ‘big’ to discuss, Aaron comes along and listens intently, rarely commenting unless he can see that I am uncertain about something. And then we go for coffee and cake.
I pretty much always see the GP alone, but truly, my GP appointments are always super quick and about something so specific – and usually simple – that I don’t need to take someone along for the ride.
Most of the time, I am happy to be on my own. I relish the time in the waiting room – all alone, nice and quiet, and usually a trashy mag or two to catch up on.
The day I was diagnosed with diabetes, I was squeezed into an end of day appointment with an endocrinologist. I asked Aaron and my mum to come along to help me understand what was happening. The next day, as I saw the dietitian and diabetes educator and endo again, they were there, and together we took in all the new information, letting it swirl around us and settle uncomfortably. A new health reality that involved needles and numbers and thinking about food in a different way. This needed a team approach.
It was incredibly useful to be able to ask them questions about things I had only half heard or half understood as my mind tried to take in all I was being told. I found myself turning to mum for suggestions around food, and to Aaron about how I was feeling and what I was worried about.
As I got used to ‘having diabetes’ I asked fewer questions and learnt to focus on what I needed to know. These became the things that we would discuss in appointments and afterwards, blocking out the ‘white noise’ of the things we didn’t need to know.
I have people around me who know a great deal about diabetes; people I can call on when I need to for advice and company and a friendly face in the waiting room. Someone on my side; someone by my side. My own personal wingmen.
A friend I’d not seen for many years contacted me the other day. Apart from occasionally seeing her name pop up on my Facebook feed, we have had no contact for over ten years.
Out of the blue, she got in touch because she had recently had a miscarriage and was feeling pretty down. She wanted to speak with someone who had been through the experience and she had seen some of my posts about how I felt immediately after I miscarried a couple of years ago, and some follow up posts since.
As we spoke – well, I mostly listened, because I knew that was what she needed – it struck me that it is always the subjects that are taboo that are the ones we need the most support with.
In diabetes, it is still complications that seem to be a topic we are uncomfortable speaking about. We speak about them in hushed tones, as if by not giving them a name we don’t give them weight.
We are scared to ask questions, because we are afraid we will say the wrong thing. We don’t want to upset people and we don’t want to look like we are prying.
But perhaps that is what we need to do a little. We need to pry.
And we can do that in sensitive, caring ways that can and do help.
I learnt how valuable having someone gently pry could be back in 2003 when I had my first miscarriage. As I was enveloped in grief and trying to work out what to do and get through the days, a friend picked me up and took me out for a coffee. She had her new baby boy with her, which was just what I needed. A gorgeous little smiling poppet, who was happy to sit on my lap and be cuddled and have his chubby cheeks kissed.
‘Renz,’ she said. ‘Tell me what happened.’
It was the first time that someone had actually asked me that. Most people asked if I was okay, which clearly I wasn’t, but that wasn’t the answer they wanted, so I would smile through my tears and nod.
But here was someone actually asking me to tell them exactly what had happened. And I did. She listened, reached out and held my hand when the tears gently started and hugged me at the end. She didn’t offer any advice, didn’t tell me it was ‘for a reason’, (seriously – the worst response ever), or tell me that everything would be okay.
She just listened. And then she said, ‘I am really sorry’. It was just what I needed, and I nodded through that too, thanking her for giving me permission to tell my story, even if it was difficult for her to hear.
I have employed this tactic over the years – not only when I hear about pregnancy loss, but other things too. It is really hard to stay silent sometimes, because we want to reassure people, we want them to know that they will be okay and we want to take away their pain.
However, I have found that that is not what people want. Often, they are just looking for an outlet; a way to tell their story and be heard.
It doesn’t even need to be something really big for this technique to work. When I tell people that I have had a hypo, I don’t want them to look for solutions. I don’t want then to workshop what happened leading up to the low or to talk to me about what I had (or didn’t have) for lunch. I just want them to listen.
I really don’t expect them to fix things. I know for me, I just need someone to legitimise how I am feeling. And acknowledge that it is tough.
My husband has the best response when I tell him I’ve had a crappy diabetes day. ‘Diabetes sucks,’ he says to me, leaving it at that. And he’s right. It absolutely does.
This weekend, I gave a talk about finding good support to a group of people living with type 1 diabetes. I can’t remember the last time I stood up in front of PWD and just chatted about life with diabetes. Recently, all the presentations I have given have been for HCPs and the tiny few I have given to PWD have focused solely on social media and technology. It was kind of nice to go back to basics and talk about supporting each other more broadly.
So, here is my secret admission: I always feel like a fraud when I am about to give a talk. Seriously, who am I? I live with diabetes and all I can do is share my (frequently clumsy) experiences. I always prepare, but my talks rarely, if ever, end up how I planned. I wind up taking weird tangents, sharing far-too personal stories and then when the anecdote comes to end, I stand there a little shocked with nowhere left to go other than to sheepishly say, ‘Right…so where were we?…’
Anyway, I was talking about how we can work with our HCPs to get the best support – and finding support outside our HCP team. And how great families and friends can be with their support, but somehow, there is nothing like being around others with diabetes because they just ‘get it’.
There was lots of nodding and chatter and laughter in the room. It was really informal – just a (large) group of people sitting around chatting. These are my people; this is my tribe!
This was my favourite kind of talk. The audience was really engaged and wanted to share their stories. I love that for a number of reasons – one of them being that it means I have to do less work! But mostly, because I always learn something new. Because there before me is a room full of experts!
Someone came up to me afterwards and thanked me for my talk. And I thanked them. Because as much as I love sharing and talking about my diabetes, I love hearing from others even more.
 ‘Got your lunch?’
‘Yep.’
‘Got your jumper?’
‘Yep.’
‘Got your homework?’
‘Yep.’
‘Okay. Grab your bag and let’s go!’
And that is how we walk out the door in the morning – after eating breakfast, getting dressed for school and brushing hair and teeth.
I then drop the kidlet at school and make my way to work.
I don’t think about what her BGL is doing throughout the day. I don’t think about what time her PE class is and if she ate all her morning tea beforehand. I don’t think about anything to do with numbers – other than knowing that she has her maths homework.
Kids have a lot to think about in their day. Kids with diabetes – and their parents and their teachers – have more to think about.
Jump over to the Diabetes Victoria blog where you can reads about the fabulous new resource launched today. It’s called Mastering Diabetes and it is going to help all children at school and childhood settings in Victoria.
It may have been a while ago, but I do still Remember the Days of the Old Schoolyard!
I see strength everywhere I look.
I see it in myself as I dig, dig, dig deeper to manage diabetes as best I can.
I see it in my friends with diabetes as they face the challenges diabetes throws at them each and every day.
I see it in other people with diabetes as they get up and push on through the stigma and the discrimination and the assumptions and the judgement.
I see it in our lack of sleep and bodies not doing what we would like and our fear and our uncertainty.
I see it in parents of kids with diabetes as they rise again after a night of missed sleep and their fear and their uncertainty.
And I see it in the healthcare professionals working with is, advocating for us and helping us make sense of the labyrinth of our health system.
We are told that we get diabetes because we are fat, because we are lazy, because we ate the wrong food, because we didn’t move enough, because our bodies were feeble.
We are told that we are not doing the best we can, that our numbers are too low, too high, not enough.
We are told that we are not following the rules.
We are told there is no funding, no money, we cannot access what we want, what we need, what we choose. And then we are told that we failing when we don’t achieve unreasonable targets.
We are told we have no willpower, we are not resilient and we have no expertise.
We are told we are sick.
We are told we are weak.
We face all this. All the time. And yet every day we get up. We live a life like everyone else and manage a condition on top of it that would drive most people to distraction.
We become strong, because we have no other choice.
Pricking our fingers, injecting our bodies, watching how what we eat, how much we move, how we feel affects everything – we manage all of those things with little complaint.
We fight demons, we blame ourselves.
But we get up.
I see strength in every person with diabetes – whatever their numbers, whatever their management.
We get up. We do it. Every. Single. Day.
Tell us again that we are weak. Tell us again.
Following the announcement at the end of last week from Diabetes UK that a new CEO had been appointed, there was much chatter online about whether or not the best person had been selected for the role. I have no opinion on this. I do not necessarily agree that you need a person with diabetes to be the CEO of a diabetes organisation – there are many other ways that meaningful engagement can take place ensuring that the organisation is representing the needs of people with diabetes.
What I was far more interested in was the direction the discussion took – specifically about the inclusion – or, as was being discussed, not – of consumers/patients/PWD/whatever you want to call us at professional conferences.
I watched on in silence as healthcare professionals, PWD and consumer groups all weighed in on the subject.
I am rarely a fence sitter, and on this issue, my position is very clear. Very, very clear.
I have yet heard a good argument as to why PWD should not attend diabetes conferences. In Australia, just as in the UK, we have the same limitations about people with diabetes having access to drug-branded information. This is archaic because, well, the internet. But whatever. (Read more here.)
Notwithstanding these code regulations, there is no reason that a PWD should not be welcome at a professional meeting about diabetes, hearing about diabetes research, learning about diabetes medications and technology and talking with the healthcare professionals working with people with diabetes. And if it is deemed that we are not fit to see the brand names of drugs, then keep us out of the exhibition spaces, but allow us to attend information and networking sessions. (For the record, I don’t support that idea either, but if that is what is necessary for us to be able to attend the sessions, then so be it.)
I would go one step further. PWD should be involved in the planning of these meetings. Why? Because surely if HCPs working with PWD are hoping to improve their knowledge and understanding of diabetes, a big part of that is gaining a better understanding of people with diabetes. And there is no one who gets that more than those of us living with diabetes.
I absolutely do not subscribe to the ‘why can’t we have a professional conference for health care professionals’ viewpoint. Well, of course you can. But there is no reason that PWD should not be involved in this and attend alongside healthcare professionals.
I’ve been more than a little vocal on this in the past. Search ‘consumer involvement’ or ‘PWD at diabetes conferences’ on this blog and you might just come up with a few things. I’ve given talks both here in Australia and overseas about it. I constantly expound the value of the consumer voice and consumer participation and consumer involvement.
The thing that interested me in the discussion I was following was just how hostile it was at times. With 140 characters or fewer at our disposal, we can’t always be as tactful as we might be in person. Sometimes, being direct is the only way. And knowing a few of the people involved in the discussion, tact is perhaps not a characteristic that they generally employ. I say that without any snippiness at all – it is part of the way they get their point across. I get it – I am often accused as being like that and I wear it as a badge of honour. As far as I am concerned, the involvement of PWD is non-negotiable and if I sound pissed about it, I probably am!
But being hostile and aggressive is not likely to result in a favourable resolution.
Working for a diabetes organisation puts me in a unique position. As part of my work, I get to attend the very conferences from which other PWD are excluded. Plus I am frequently invited to speak and this privilege is due to a combination of my diabetes org work and also my work as a blogger and diabetes activist that I do outside of paid employment. It’s a sticky situation that I manage as best as possible. There are disclaimers everywhere and even the whiff of a conflict of interest is declared.
However, there is one thing that I have learnt from ‘being on the inside’ and that is working collaboratively is highly likely to produce results more than being combative. There is a lot of negotiating required at times and an understanding that things take time. Sometimes lots of it. It’s taken me a lot of time to understand that!
Call me – and those who are trying for a more collaborative approach – political or bureaucrats. You can think we’re sell-outs. We’re not. At all. We actually have a seat at the table and are working for people with diabetes. And you want us sitting at that table! Come join us.
So, think you want to get involved, but not sure how? There are myriad ways that you can try to work with organisations. If paid employment is not what you are looking for, there are many volunteering opportunities including Boards (some may be paid positions), advisory panels, expert reference groups or simply, pick up the phone and pitch your idea!
I am always interested to hear from friends overseas about how they access their diabetes supplies. In some places, discussions, negotiations and, it seems, arguments with insurance companies are required before product is delivered; in other places, people with diabetes require a prescription from their HCP to purchase consumables as well as medications. And, in other places, access is so limited and sporadic there are no processes in place to guarantee supply of the things we need to manage diabetes.
In Australia, the process is actually quite simple. A diagnosis of diabetes means that a person is eligible to be registered on the National Diabetes Services Scheme (NDSS). Once registered, PWD can use the NDSS to access most diabetes (non-drug) consumables.
The supply of insulin (or other diabetes medication) here is part of the Pharmaceutical Benefits Scheme (PBS). A prescription is required from a doctor and that is taken to a pharmacy to be filled.
In my experiences, insulin is not always kept in stock, so I make sure to call ahead and have it ordered in for me. Most people with diabetes I know do the same thing – many have been caught out thinking that we could simply show up, hand over our prescription and be given the insulin (after being warned about how it needs to go into the fridge NOW – RIGHT NOW).
The NDSS is an initiative of the Australian Government. Diabetes Australia has, for the last 28 years, administered all aspects of the NDSS, which apart from product supply and delivery also includes information and support services for people registered on the Scheme.
When I need BGL strips or pump supplies or needles, I can access whichever products I choose to use by either ordering over the phone, online, or at an NDSS outlet, which could be downstairs at work (see disclaimer), at a hospital, community health centre or, most commonly, a pharmacy.
Sounds easy-peasy-lemon-squeezy, and for me, generally it is.
The NDSS rules and regulations are all set out by the Department of Health and then carried out by those actually distributing products. It’s for that reason that there are limits on the quantity of product you can purchase in one hit. Again, I’ve not had a problem with that. I had a form filled in by my endo a number of years back that stated I use above the upper limit of strips. I am therefore able to order more than the 900 strips per 180 days that is standard. (For those doing the maths at home, that is five strips per day. This is what is recommended as a guide by many HCPs. Of course, diabetes does not operate to a guide, which is why there is the flexibility to order more if required.)
I have recently noticed quite a few people online complaining that they are having difficulty accessing the quantity of product they require.
So, what do you do if you have this problem? The first thing to do is to remember where the rules and regulations come from. Of course it is frustrating to be faced with someone telling you that you are unable to have as much product as you need – especially if you are ordering within the limits, but even if you are ordering outside of that quantity. But don’t shoot the messenger. A pharmacy assistant telling you that you can only order 180 days of strips or needles is just doing their job. (It’s a completely different issue if they are telling you that they will only give you one or two boxes – that is not okay!)
You can write directly to the NDSS or even better, to the Commonwealth Minister of Health. Be clear and concise about why you need to be able to order the quantity you require.
This is also the time to remember that your local member is there to serve you.
Remember that if you are writing to an MP, they may not have the understanding of diabetes that you do, so use generic terminology – and don’t use ‘diabetese’. Keep it simple and try not to get bogged down in detail.
If you believe that you are not able to access what you need – the actual product and/or the product in the quantity you require – there is something you can do about it. That something is not bitching and moaning on social media, by the way. It’s taking action and actually doing something that will result in change.
I have written before that there are going to be some changes in the next twelve months with NDSS product supply. There is absolutely no reason to believe that the subsidised scheme is under threat, however the changes will certainly mean that the way we have accessed diabetes supplies in the past will change.
FUN BIT! Disclaimer
I work for Diabetes Victoria and Diabetes Australia. The majority of the work I do is funded from the Registrant Support Services part of the NDSS. This is a different funding stream to Product Supply and Delivery.
It was a lovely morning – a lazy weekend sitting in a local café, drinking fabulous coffee, skimming through the papers and discussing the Amy Winehouse doco we’d seen the night before. The kidlet was still being spoilt by her grandparents, and Aaron and I were making the most of a leisurely breakfast.
We were at one of our favourite cafes in our area. The coffee is consistently excellent, the food is great and the owner is one of the nicest people I have ever met. Being in his café is one of my favourite things to do on the weekend. (Plus they make the most amazing home-made marshmallows. Totally bolus worthy!)
We finished up after sneaking in a second round of coffees, and meandered to the front of the store to pay.
‘They look awesome,’ the guy ahead of us was saying to the barista, pointing at the delicious-looking fudge-y, chocolate brownies on the counter.
‘Yeah; they are really great. So sweet. You get diabetes just looking at them.’
The next noise was the sound of my head spinning and my hair whipping around.
‘No you don’t,’ I said – loudly enough for them both to hear. The customer turned around and the barista looked at me. I was a little terse, but not rude.
‘I mean it. Really, they are so sweet,’ said the barista.
‘Doesn’t matter how sweet they are. You still won’t get diabetes eating them. You really shouldn’t say that. It’s not true.’ I turned to Aaron. ‘I’ll be outside. I’m done here.’
And there it is. Again. The stupid, ignorant, insensitive, offensive, throw away comments about diabetes. Comments that also happen to be untrue.
At Nova the night before, we watched the heartbreakingly sad story of Amy Winehouse in the brilliant, but harrowing, documentary Amy.
This incredibly talented young woman was hounded by the media as she dealt with addiction. And at the moment when she most needed support and help, late-night television show hosts thought it was amusing to make fun of her. They thought it was hilarious to comment on her alcoholism or weight loss or drug abuse. They thought that a vulnerable young woman who was falling apart was a great target for their cheap jokes.
And apparently, diabetes is too.
It is not funny. People who are living with health conditions are not a punch line. Diabetes is not here to use as a material for a cheap joke. The condition that I work so bloody hard to keep in check – every minute of every single day – is not a chance for you to try to be witty (which, incidentally, you are most likely not!).
All of that came flooding to my caffeine-fuelled mind as I stood there, waiting to pay the other morning. ‘Am I overreacting?’ I asked Aaron when he walked out of the cafe. ‘No. Not at all.’
People who are dealing with health issues – no matter what they are – need support. We need people to try to understand what we are doing. We occasionally need to be reminded that we are doing the best we can.
It’s actually quite simple. Diabetes is not a joke. Stop thinking it is.
Amy Winehouse singing The Girl from Ipanema is a thing of beauty. Here it is.
I recently gave a short presentation on wearable medical devices that provide constant, real time data, and what that means for people on a day-to-day, minute-to-minute basis.
I had a slide that was a word cloud, including some of the (non-sweary) words I use regularly.

Being conscious that the crowd were not all necessarily diabetes-savvy, I focused on the data aspect and what that means for me emotionally more than the technicalities of the technology.
Afterwards, over tea and Arnott’s cream biscuits (Kingstons FTW!), I spoke with a (non-diabetes) healthcare professional – a GP who had never seen either an insulin pump or CGM before.
‘What great technology! It’s like you don’t have diabetes anymore,’ the GP said to me, clearly not having listened to any of my talk – especially the bit where I said sometimes tech could actually be more overwhelming and a constant reminder of my diabetes. Or the part where I said that as much as I love the devices, I still need to drive them and do a lot of work.
I shook my head gently and smiled. ‘I wish. And one day, I hope it will be like that. But this tech, whilst terrific, is part of my arsenal in the significant self-management tasks I do each day to manage my diabetes.’
He looked far less impressed.
‘Oh,’ he said. ‘So it’s not all that great?’
‘No, no. I’m not saying that.’ I wondered if he had actually heard anything I said. Because as much as I talked about the overwhelming side of the technology and all the data, I spoke a lot about how useful it is too.
‘It’s complicated,’ I said. ‘Sometimes I love this tech; other times I hate it. But mostly, I am glad I can use it the way I want.’
I munched on my Kingston biscuit, thinking. ‘I guess it’s kind of how I feel about my mobile phone. I love it – it means that I can reach everyone I want to whenever I want to and they can reach me. It means I can check Twitter and Facebook to see what everyone is up to. I can check the weather. I can receive emails and reply to them all the time. It’s great, right?’
‘And it’s a pain in the arse as well. Pretty much for all the reasons that it is great. But regardless, I wouldn’t be without it.’
He nodded. ‘I think I get it now. That’s an analogy that makes sense to me. Diabetes is so huge. A lot of it doesn’t make sense.’
It was my turn to nod. ‘So much of the time I am guilty of forgetting that not everyone gets the intricacies of life with diabetes. I try not to have expectations that people know about it, but find it difficult to explain. Maybe I need to come up with non-diabetes explanations.’
‘Like ‘life is like a box of chocolates?’ Forrest Gump managed to do it.’
I laughed. ‘Actually, that’s a pretty good analogy for diabetes too,‘ I said.
He thanked me and walked away, promising to learn more about diabetes technology.
I spoke with a few other people, ate another (couple of) Kingstons and got ready to leave. As I was collecting my things, I heard the GP speaking with someone else. ‘The technology is great,’ I heard him say. ‘But it can be frustrating at times. Kind of like the frustration from having a mobile phone and being reachable all the time.’
I smiled to myself and left the room.





