
You are currently browsing the category archive for the ‘Peer support’ category.
For more information (all Australian sites):
Diabetes conferences and scientific meetings in 2020 have looked very different than in previous years. It looked as though we were off to a flying start with a successful ATTD in Spain back in February. But not long after all the attendees returned to their corners of the globe, the world turned upside down and decided that, along with everything else, in-person meetings were done.
Major professional conferences such as those run by ADA, DUK, EASD, ISPAD, ADS & ADEA and IDF have all either happened, or will be happening, virtually, with a Zoom (or other) platform being where we meet, rather than a massive conference centre in a major city.
As ever, I search for a silver lining and if there is one it is this: the pivot to virtual conferences means that some of the main barriers in the way preventing PWD attending diabetes conferences are somewhat reduced. With travel, accommodation and a lot of the other expenses out of the way, it may be easier for advocates who would like to attend to find their way in. Let’s look at that as the disruption we needed to have to get PWD flocking to meetings in droves.
There is still the matter of registration passes, and we know that is not always the easiest thing to overcome. The registration fee is significant, and some conferences only allow HCPs and researchers in. Usually, press passes provide a way to get passed security, but they require letters of assignment (sometimes from diabetes organisations who ask PWD to act as ‘on the ground’ reporters), or other criteria be met. And, of course, there are invitations to attend satellite events extended from device and drug companies to some advocates. While there is often criticism at these methods, they have meant that there are PWD at conferences, many of whom provide information back to the community.
At ATTD, there was a new way in. Advocacy group #dedoc° launched a new program, #dedoc° voices, which you can read all about here. For the pilot of the program in Madrid, the diabetes advocates whose applications were successful had access to all parts of the meeting.
#dedoc° voices is happening again for EASD (coming up next month), and it’s not too late to apply. And as an added bonus, successful applicants will also receive registration to the ISPAD conference in October. ISPAD is the International Society for Pediatric and Adolescent Diabetes, so if you are a parent of a kid with diabetes involved in advocacy and peer support, you may be super keen to attend this one.
To apply, go here. #dedoc° voices is open to PWD now, so if you have always wanted to attend a major diabetes conference, there is nothing stopping you from applying, right now. Any one from anywhere around the world can apply – the only consideration is how you’ll manage time zone horrors if you don’t live in the same zone as the conference. (But please don’t come crying to me about that – I’ve spent the last six months settling in for hour long meetings hosted out of Europe of the US which begin long after sunset and involve perky people just waking up while I yawn and struggle not to fall asleep in my Zoom square!)
What are you waiting for? Apply now and come be a part of one of the biggest diabetes meetings in the world. I promise there will be lots of other PWD there for you to (virtually) meet up, and share ideas with. Come say hi!
Disclosure
I am an advisor to the #dedoc° voices program. I do not receive any payment for this role. 
At the best of times, I’ll celebrate any kind of anniversary, but it seemed even more important to acknowledge my ‘loopiversary’ this year in what can really only be termed as the most fucked of times. Last week, I clicked over three years of looping, a decision that remains the smartest and most sensible I have ever made when it comes to my own diabetes management.
In reflecting just how Loop has affected my diabetes over the last three years, I’ve learnt a few things and here are some of them:
- The words I wrote in this post not long after I’d started looping are still true today: ‘…this technology has revolutionised every aspect of my diabetes, from the way I sleep, eat and live. I finish [the year] far less burdened by diabetes than I was at the beginning of the year.’
- The #WeAreNotWaiting community is but one part of the DOC, but it has provided the way forward for a lot of PWD to be able to manage their diabetes in ways we never thought possible.
- Even before I began to Loop, the kindness and generosity of people in that community was clear. I took this photo of Dana and Melissa, two women I am now lucky to count amongst my dearest friends, at an event at ADA, just after they had given me a morale boosting pep talk, promising that not only could I build loop for myself, but they would be there to answer any questions I may have. I bet they’re sorry they made that offer!

- Loop’s benefits are far, far beyond just diabetes. Sure, my diabetes is easier to manage, and any clinical measurement will show how much ‘better’ I am doing , but the fact that diabetes intrudes so much less in my life is, for me, the real advantage of using it.
- That, and sleep!
- I get ridiculously excited when other people make the leap to looping! I have watched friends’ loops turn green for the very first time and have wanted to cry with joy because only now will they understand what I’ve been ranting about. And experience the same benefits I keep bleating on about.

- It’s not for everyone. (But then, no one said it was.)
- You get out what you put in. The more effort and time and analysis you put into any aspect of diabetes will yield results. But with Loop, even minimal effort (I call the way I do loop ‘Loop lite’) means far better diabetes management than I could ever achieve without it.
- It took an out of the box solution to do, and excel at, what every piece of commercial diabetes tech promises to do on the box – and almost always falls short.
- It’s amazing how quickly I adapted to walking around all the time with another but of diabetes tech. My trusty pink RL has just been added to the phone/pump/keys/ wallet (and, of course, mask) checklist that runs through my head before I leave the house.
- Travelling with an external pancreas (even one with extra bits) is no big deal.

- I was by no means an early adopter of DIY tech, but I was way ahead pretty much any HCPs (except, of course, those living with diabetes). The first talk I gave about Loop still scars me. But it is pleasing to see that HCPs are becoming much more aware and accepting of the tech, and willing to support PWD who make the choice to use it.
- The lack of understanding about just what this tech does is astonishing. I surprised to still see people claiming that it is dangerous because users are ‘hacking’ devices. Language matters and you bet that this sort of terminology makes us sound like cowboys rather than having been thoughtful and considered before going down the DIY path.
- The lengths detractors (usually HCPs and industry) will go to when trying to discredit DIYAPS shouldn’t, but does, surprise me. The repeated claims that it is not safe and that people using the tech (for themselves or their kids) are being reckless still get my shackles up.
- Perhaps worst of all are those that claim to be on the side of those using tech, but under the guise of playing ‘devil’s advocate’ do more damage than those who outwardly refuse to support the use of the technology.
- The irony of being considered deliberately non-compliant when my diabetes is the most compliant it ever has been hurts my pea-sized brain. regularly.

- There is data out there showing the benefits and safety of looping. Hours and hours and hours of it.
- My privilege is on show each and every single time I look at the Loop app on my phone. I am aware every day that the benefits of this sort of technology are not available to most people and that is simply not good enough.
- Despite all the positives, diabetes is still there. And that means that diabetes burnout is still real. But now, I feel guilty when feeling burnt out because honestly, what do I have to complain about?
But perhaps the most startling thing I learnt on this: The most variable – and dangerous – aspect of my diabetes management has always been … me! Loop takes away a lot of what I need to do – and a lot of the mistakes I could, and frequently did, make. Loop for me is safer and so, so much smarter and better at diabetes than I could ever hope to be. I suspect that as better commercial hybrid closed loop systems come onto the market, those who have been wary to try a DIY solution will understand why some people chose to not wait.
And finally, perfect numbers are never going to happen with diabetes. But that’s not the goal, really is it? For me, it’s about diabetes demanding and being given as little physical and emotional time and space in my life. With Loop, sure numbers are better – but not perfect – and I do a lot less to make them that way. It took a system that did more for me, keeps me in range for most of my day, and has reduced the daily impact of diabetes in my life to truly understand that numbers don’t matter.
Last Friday night, I sat around with three other women with type 1 diabetes and we had a chat. When I say ‘sat around’ I mean Zoomed, but other than the fact that we were seeing each other through computer screens, it could have been any other time I was meeting up with women with diabetes for a casual chat.
The reason for this gathering was so that I could be interviewed for a new Australian podcast. Mamabetes was launched just last week, and is a project by three amazing Aussie advocates, Ashleigh, Rachel and Carleigh, all who are living with type 1 diabetes.
I was a little surprised when they reached out to me. My kid is fifteen and my experience of pregnancy and diabetes is a little old now. But they wanted to speak with me about stigma and language, and how that can impact on all sorts of diabetes experiences – including pregnancy.
I’d never met any of the women before and other than a short conversation with Ashleigh a couple of days before, the first time we chatted was when Zoom brought their gorgeous faces and happy smiles into my study at home. I’d been sent a brief outline of what they hoped to get from our discussion and a few broad questions for me to consider before we got started. We were going to chat for about fifteen minutes and see where our conversation took us.
I’m sure that we could have stuck to that timeframe if we really wanted, and to the questions I’d been offered as a guide. But an hour later, we were still chatting, and we’d taken off on some wonderful tangents, as happens when people with shared interests and experiences come together.
The podcast episode with our chat dropped this morning and I’ve been listening to it in bits and pieces in between the Zoom existence so many of us seem to be living at the moment. We cover lots, so do have a listen! Click on the image below to go to the podcase, and the Mamabetes other socials are listed for you to follow along.
Asheigh, Rachel and Carleigh are creating something really important here, and providing women with diabetes a place to learn and connect – around an issue that is relevant and important to many. Thanks to these three dynamic women for doing this, and for inviting me to be a part of their second podcast episode.

Go follow…
Until about three weeks ago, I’d never seen the words ‘social’ and ‘distancing’ in the same sentence. And then, suddenly, we were all being urged to practise this new form of keeping away from people.
What became apparent very quickly, however, was that social distancing could very easily lead to social isolation and that is not what the aim of keeping away from others was all about. Rather, it was about being physically distant from others. No more physical hugging, or cheek kissing. No more pats on the back or hand shaking.
But stopping physical contact doesn’t mean becoming disconnected to people. In fact, if there was ever a time that we need to feel connected to people, it’s now. And for me, I have never needed my diabetes tribe more. I think that a number of others might just be in the same boat.
I can’t begin to count the number of times I’ve spoken or written about how much I need my friends living with diabetes to help support my daily life with diabetes, or how they are an essential part of my diabetes management tool kit. In fact, I use this tweet so frequently when I am taking about diabetes peer support because it perfectly illustrates just how essential it is to me.

At the moment, as were locked in our homes, maintaining connections to others is far more difficult. My sister has just returned to Melbourne after over a year living on the west coast and apart from sitting in her garden while she stood at her front door, I’ve not seen been able to welcome her home. I’ve not hugged my parents for weeks, again seeing them only from out the front of their house as they stood on their veranda.
But when it comes to our diabetes peers, I’ve found it a little easier. Our DOC lives over the interwebs. We are physically distant pretty much all the time because most of the people that I spend my time talking to are literally in another country! I may not get to see my friends at conferences and meetings much in coming months, but that hasn’t stopped the messages and photos and videos and video calls.
Each night, before I turn my light out, I message friends to check in to see how they are. It takes nothing to send a quick message but the reassurance that there are others in the same boat, feeling the same fears and frustrations seems to calm and alleviate some of my stresses. And when I wake up there are always messages from friends who were awake while I slept checking back in on me. There are group chats with discussions that range from the incredibly serious to the (thankfully and much needed) absurd. Memes fly around and eyes are virtually rolled at some of what we are seeing online. And sometimes, but only sometimes, we talk diabetes…
I know that pretty much everyone around the world right now has some sort of concerns about COVID-19. Diabetes adds extra to that (because diabetes is a shit and just makes everything more difficult!). And that means that we want to unite with those who understand the extra bit of stress or pressure or anxiety. Find your tribe. And love them so, so hard. (Just do it from a distance at the moment….)

Tuesday last week, I woke up to find this message in my Twitter DMs. I read it and read it again. It accompanied a tweet or two to me about my blog post from the previous day.
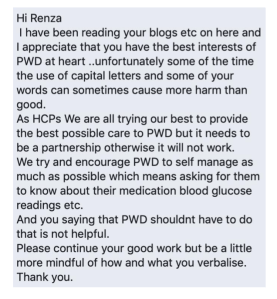
I debated about whether or not I should share this publicly. I wrote some words, walked away, came back to them, walked away, asked a few friends their thoughts, walked away, wrote a bit more and walked away again. I posted it to my closed Facebook page to get some feedback from others and wondered if that was enough.
But then remembered this blog post. #StandUP.
So, here I am, standing up. Because I am upset and angry.
I am not upset and angry that someone didn’t like or disagreed with what I wrote. It would be frightfully boring if we always all agreed with each other and loved the same things.
I am not upset and angry that this message was unsolicited. I believe that people don’t need an invitation to comment when I write and publish things on a public forum. I invite all feedback – good and not so good.
I’m not even upset or angry that I don’t understand what was being referred to in the message. I re-read and re-read and re-read my post, and I can’t see where I ever, ever said that people with diabetes shouldn’t self-manage, or know what meds they’re taking or what their glucose readings are. I couldn’t find it in there. But, people interpret things differently and perhaps my writing wasn’t as clear to them as I thought it was.
I’m not here today to defend the content in that blog post, because that’s not what this is about.
I am upset and angry that I was being told to ‘be mindful of what and how I verbalise’. This is called tone policing. It is telling me that I should moderate the way that I talk and think about my own diabetes. This was an opinion piece. My opinion. People don’t need to agree with it – and they can tell me they don’t. But telling me to moderate the way that I communicate is a very different thing.
I will forever call out and stand up to anyone who tells me, or others with diabetes, to restrain our feelings or opinions, and that is why I am writing this post. Because more than anything, I believe that we have a right to express how we feel about diabetes, in the way we want to, especially when we are sharing our own opinions or experiences. When we are told to be mindful of what and how we are writing/speaking it is a step on the way to censoring and silencing us. We already do that enough.
Often, in clinical settings, we moderate the way we speak. We might minimise how tough things are, or don’t speak out about the way we are treated or the judgement we face. When we are told that we’re not doing enough and are failing, we look down, afraid to stand up for ourselves.
And so, we created spaces where we could be free to share and rant and cry in a way that gave us some comfort. We turned to others who are likely to have had similar – if not identical – experiences. We share our opinions, some of them unpopular, thought-provoking and challenging of the status quo because we feel we have the liberty to do just that.
We have had to be quiet for too long. But that should never be the case in our own space.
The diabetes online community is that space. Twitter, when we use our #xxDOC (or #DSMA) hashtags is that space. Other online and offline support opportunities and groups we have created is that space.
And this blog (and others written by PWD) is that space.
So, back to the message I received last week. I did ask for clarification, and for examples of where I’d used capital letters or words that could be considered harmful, but I didn’t get a response.
Just this message:

No answers, just a threat to mute me. To silence my voice. Sure, it is only being silenced on this one person’s twitter stream, but that was the response to me refusing to be ‘compliant’ and agree with a healthcare professional’s demands that I tone down the way I write about my own opinion. I had not been aggressive, abusive or rude. I had just shared my own opinion and thoughts in my own voice. In my own space.
In a couple of weeks, the diabetes conference juggernaut will descend on Madrid for ATTD.
This one is all about new treatments and technologies in the world of diabetes and, in its thirteenth year, looks to once again be a busy and enlightening meeting.
There is so much on the program that focuses on user-led technologies and initiatives. I think it’s fair to say that PWD have long recognised that technology in diabetes is more than just the devices we wear on our bodies. We have long used technology for support and to connect to others who help us manage the day-to-day life of diabetes, and to learn and share. DIYAPS may be about the systems, but grasping the role of online platforms and support is essential in understanding the #WeAreNotWaiting movement as a whole.
 It’s great that a number of PWD already know that they will be part of ATTD this year, attending satellite events run by different device and drug companies. Some are on the program and some will be there through other opportunities and work.
The more the merrier, I say! Different voices with different experiences sharing and learning is always a great thing. And having the opportunity to meet people in real life after only seeing them online adds another dimension to our peer support networks.
For European diabetes friends yet to secure a place at ATTD, there is another possible avenue in, but you need to be quick. Launching at ATTD is the new #dedoc° voices program. Although #dedoc°has its foundations in Germany it is truly an international community, involving people from all over the world. #docday° events (always a highlight at these conferences) involve diabetes advocates from across Europe and the US, and even the odd Australian, too. It’s great to see this new initiative is helping more advocates get a seat at the diabetes conference table as active participants.
APPLY NOW
If you want to be considered for the #dedoc° voices program, you need apply, which is super simple – just go here, where you will find out all about the program and how to throw your name in the ring! Applications close on Friday, so chop chop!
Successful applicants will have their travel and accommodation costs reimbursed, and will receive full registration to the conference.
Good luck. And hope you see you there.
Disclosure
I am an advisor to the #dedoc° voices program. I do not receive any payment for this role.
I am an invited speaker at ATTD 2020. Lilly Diabetes is covering my travel and part of my accommodation so I can participate in the DOCLab advisory group meeting held during ATTD.
My packing-for-travel routine is pretty relaxed. We left for New York at 8am on Boxing Day and I started packing when we got home from our five millionth family gathering at about 10pm on Xmas night.
Admittedly, my laid back attitude to diabetes-supplies packing could be because I usually spend my time travelling surrounded by other PWD who are far better organised than I could ever hope to be. I know that if I run out of insulin, pack the wrong glucose strips for the meter I’m carrying or forget a charging cable, someone will be able to help me out. (I know this because these things have all happened. More than once. Way more than once.)
Anyway, I thought that I had done a pretty damn good job of throwing everything I needed together for New York, with back up supplies and contingencies. As we headed to the airport bright and early, still full of my mother’s Xmas zippoli, I felt comfortable that diabetes was going to be a relatively easy companion on this trip.
Turned out that I got it mostly right. Just not completely!
Issue one happened when I got a transmitter low battery warning the first week we were in NY. ‘Bugger,’ I thought, remembering back to the last time I recharged my Fenix G5 transmitter*. It was while I was sitting at breakfast one morning in Boston at ISPAD. I recalled that I definitely hadn’t had the transmitter plugged in long enough for a full charge. At the time, I thought I’d charge it fully the next time I did a sensor change…and then promptly forgot.
Of course, I had forgotten to pack the very specific charger required to recharge my Fenix. And I couldn’t for the life of me remember what it was called. ‘It has two little magnetic-y things on the side. And it’s kind of shaped like this,’ I said sketching a rough picture to the people behind the counter in about fifteen electrical stores around the city.
After getting nothing more than blank stares, I went directly to the source – Facebook – and sent a message to a couple of tech friends back home (including the bloke responsible for building the device). I had a response minutes later, placed an Amazon Prime order straight away and two days later my Fenix was charging on the kitchen counter in our apartment.
I had a re-batteried travel transmitter with me that I used in the interim (with layer upon layer upon layer of waterproof tape over the top of it because I had also forgotten to pack the resin needed to finish off that little device…), but as soon as the Fenix was fully charged, I reset it and shoved it back into the still in situ sensor. Crisis mostly averted.
And then there was the run in with Dex sensors. I’d sited a new sensor a day or two before we left and took two spares with me. I usually get three weeks out of a sensor, so thought that if lucky I wouldn’t even need to change one at all during our time away. But if I did, I would be right and have another there … and a spare just in case.
Well, best laid plans and all… the original sensor failed after less than a week. The second sensor did too, and the third sensor was actually faulty – the needle scarily poking out the end as I released it all from the packaging.
I believe the word I used at that point was ‘Fuck’. Loudly. And then turned straight back to Facebook with this:

A few NY friends reached out and shared the post, and within an hour, I had organised to meet up with someone who could help me out. Thanks a million to Stacey for connecting us, and thanks two million to Caroline who rode into Manhattan with her ridiculously beautiful baby to drop off sensors to me and have a coffee. (Off topic, but Caroline and I thought this was our first-time meeting, but we realised later that we had met for dinner one night in New York back in 2011!)
I am forever grateful for the support I receive from my peers online – and being my back up plan because I am so crap at diabetes. I do promise to try to do better when getting myself organised for travel, but I know that I am still likely to get things wrong. Diabetes is a hard task master and demands a lot. Slip ups happen.
But there is always help at hand. I was off Twitter at the time, feeling particularly vulnerable after the brutal time on there at the end of the year. Thankfully I had Facebook to turn to and a huge group of diabetes friends there to help me out. But what if that wasn’t the case? This is why our online spaces must be safe at all times, and why that power imbalance between HCPs and PWD, and how potentially harmful that can be, needs to be recognised. We need to feel safe reaching out wherever our peers are for whatever support we need. I did that and that’s why this blogpost is called ‘Peer support on the road’ rather than ‘Loopless in New York’!

Back to the important things.
* I use a rechargeable G5 transmitter with my Dexcom, built by a very clever bloke in Australia.
I wrote a post a while ago called ‘You Do You’, (and revisited and expanded on it here). It’s where I wrote about how everyone should have the freedom to do diabetes whichever way they see fit. I’m pro-choice in all aspects of life*, especially when it comes to PWD choosing their own management tools.
And I think that people with diabetes should have the choice to BE the people we need to be. And the people we are. I touched on this on my post on Monday when I spoke about how I felt intimidated online because my opinions and thoughts, and the way I addressed issues, were not everyone’s cup of tea. I felt that I was being called out for being myself. And that wasn’t okay.
No two people with diabetes are the same; no two people with diabetes will have precisely the same management ideas and preferences, and no two people with diabetes will react and respond to situations in exactly the same way.
THAT IS OKAY.
Diabetes is messy, frustrating, weird, annoying, amusing (rarely, but sometimes), scary, boring and a whole lot of other adjectives. And how we react and respond to it is our own business and no one else’s. You BE you, because you have the right to do that.
You have the right to be as loud or as quiet as you want.
You have the right to be as bitter and angry as you need to be in the moment.
You have the right to celebrate and be joyful about your diabetes.
You have the right to call out things that upset you just as much as you have the right to commend the things that make you satisfied.
You have the right to step away from groups, situations, people who upset you.
You have the right to disagree with others. Having an opposing view does not mean that you are attacking another person.
You have the right to have an opinion on what you see in the world of diabetes – even if it is happening on the other side of the world. I was incredulous when it was suggested that I shouldn’t question something happening in a healthcare system of which we are not a part. (I may not use the healthcare system in the US or the UK or Italy or anywhere other than Australia, but I am allowed to comment on what I see being done in those places.)
You have the right to be passionate and not be told that is a character flaw.
You have the right to be emotional because diabetes is real in a way that only makes sense to those of us who are living with it or have a loved one living with it. I don’t know how to take the emotion out of this, so you bet I will be emotional at times. I don’t get to clock off at the end of the work day and not think about it.
You have the right to use the words and language that works for you when talking about your own diabetes and if anyone tells you that #LanguageMatters is actually preventing PWD from doing that, tell them to fuck right off. It’s not. It never was. It never will be, and anyone who says it is has missed the point of the whole movement.
You have the right to use the word ‘fuck’ or whatever else you want to use. Profanity helps some people and we shouldn’t be told to wash out our mouths if others don’t like us using those words. (Sorry, dad.)
You have the right to be the sort of advocate you want to be. Or to not be an advocate.
You have the right to share your experiences – even the ones that don’t shine a particularly positive light on health systems or HCPs. No one – NO ONE – should silence us when we turn to our peers to seek support, or talk about what is going on in our diabetes lives.
You have the freedom to talk about your own diabetes, especially in the diabetes online community which we created for this very reason – to be able to share our experiences, learn from each other, support our peers and build each other up.
So, this? This is me being me. This is me standing up and not going quietly. This is me saying that I will be the person with diabetes I need to be, because it’s the only way I can be true to myself and true to my community.

*Except vaccinations. I don’t believe in choice there.





