
You are currently browsing the category archive for the ‘Awareness’ category.
This morning as I was buzzing around getting ready for work, I suddenly stopped. I realised something that had obviously been creeping up on me so incrementally that I had not noticed it before.
I looked around the bedroom and saw empty cannula packaging from the line change I had done when I got out of the shower and the empty sensor pack with the date written on it so I would remember when it was inserted. I went back through my CGM trace and pump history, noticing where I had bolused for a high BGL, set a temp rate for an impending low and calibrated at the appropriate times. I checked the history on my BGL meter and saw that I have been checking regularly and that the numbers were not as crazy as they have been.
I looked in my bag and saw a spare bottle of strips, my fully stocked ‘emergency’ kit, and a juice box and a small container full of glucose tabs ready in case I needed them.
When I got into work, my desk was prepared for all contingencies – more glucose tabs on the desk, a couple of spare cannulas in the top draw, as well as a few syringes. And a few single portion packs of Nutella.
I was – I am – managing my diabetes – well and without any stress at the moment. The burnout fog that had enveloped me for a long, long time seems to have lifted without me even noticing, and the diabetes tasks that form part of my day and had been so, so difficult to manage, have become routine. I do them without thinking. Checking my BGL and calibrating my CGM just happens. Bolusing for meals or my morning milky coffee is done before I take that first taste rather than half an hour later because my CGM is blaring at me that I am high.
Am I feeling motivated? I’m not sure that is the right word. I don’t have a desire to do these things. I am not so focused on diabetes that I think about it all the time.
But I am doing what I need to. Routinely. Just like brushing my teeth, combing my hair and putting on a necklace in the morning.
Perhaps that’s the thing about managing diabetes well. It’s the balance between getting the things done and not panicking about them. Or feeling so anxious and guilty because they are not getting done.
I don’t know the secret to this change. I do think that a big part of it is wearing my CGM all the time. Once I managed to hurdle feeling overwhelmed by the data and just accepted the numbers for what they are and acting accordingly, I feel much more driven to ‘do diabetes’. And perhaps as I see that things are not as dire as I often imagine them to be, I feel that I can just get on with things.
This is the roller coaster of diabetes. The ebbing and flowing of motivation and being in the headspace to get things done. I’m in a good place for now. I just have to work out how to stay here.

Emergency stash at the office (for lows or as required….)
It’s gloomy in Melbourne today. I have tights on for the first time in months and my hair is now frizzing thanks to the rain I was caught in as I ran next door for a coffee. (The silver lining in all of this is that there is fabulous coffee right next door to my new office. Also, extra silver lining is that I can see the weather out of my beautiful window. The not-so-silver-lining is that I am reminded that I am fool, because window = seeing rainy weather and yet I still forgot to take an umbrella…)
So here are some things that are keeping me either amused, happy, annoyed, interested, fascinated and heaps of other things too!
Roses spared and children saved
Today, the Spare A Rose Facebook page announced that 376 children would be benefitting from people’s generous donations this Valentine’s Day.
It’s not too late to make a donation, or even consider making a monthly donation throughout the year. AUD$6 each month equals a month of insulin for a kid who would otherwise not be able to afford it.
While this was the focus of our Valentine’s Day, there was still a lot of baking. Because I love a heart shaped cookie. Or giant brownie. And sprinkles.

Still the wrong name for this week
I think that the name misses the mark because it focuses on weight and not health. The overall aim of the week is to encourage people to cook more at home to achieve a healthy weight. Here’s just a little of the conversation with the DAA (after they read my post last year) on Twitter:
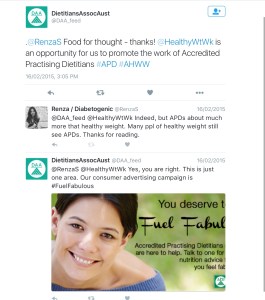
I think that this really does a disservice to the role of dietitians in healthcare. I am of a healthy weight, but have benefitted from the expertise of dietitians in the past.
The name of this week turns me off actually wanting to participate in any way, even though there are some terrific initiatives. What are your thoughts on this one?
In the genes
Why do some people develop diabetes-related complications and others don’t? We’re told that ‘control’ is the reason, but we also know that some people develop complications, despite years of what is considered ‘good control’ while others who struggle to reach targets don’t.
Things I wish I knew
I learn new things about diabetes each and every day. But how much easier it would have been while navigating this annoying bloody path to have known stuff earlier on. Diabetes UK has released a new book, 100 THINGS I WISH I’D KNOWN ABOUT LIVING WITH DIABETES, which includes information collected from over 1,000 people with diabetes with input from clinicians. The final 100 were selected by people with diabetes, (nice engagement there!), who chose the tips they thought most useful.
Oh – and while talking about Diabetes UK: Happy Birthday! They turn 82 years old this week.
New (to Australia) Tech
Looks like Australia is about to catch up to our friends in the EU who have had access to Freestyle Libre Flash Monitoring. The Flash website went live this week. More details – such as cost and release date – are yet to come, but you can register your interest. Have a look and register your interest.
And while we’re talking new tech in Australia, a couple of weeks ago, the Aussie launch details of the Dexcom G5 were announced. You can download the app (iOS only) which is already available from the App Store, although you won’t be able to use it until you are hooked up to a G5. The App has the ‘Share’ capability which means that you can (just as it says!) share your data with others.
Rock on
Last week, I was sitting at the front of our house, enjoying the sunshine and my day off, and listening to Live Fast, Diabetes, the new song from Adelaide punk/rock band, Grenadiers.
A very crotchety woman walked by, stopped as she heard the music, and scolded me with this nugget of wisdom: ‘You’re too old to be listening to that noise.’
Yeah, we know
Science: ‘Apparently BGLs are lower in warm weather.’
PWD: ‘Ah, yeah. We know. We’ve known for ages….’
Love it when evidence catches up!
And finally….
It’s Tuesday. Do the #OzDOC tweet chat! Tonight at 8.30pm AEDT.

I don’t get to take part in the OzDoc tweet chats as frequently as I would like to anymore, but when I do, I know that I am guaranteed an hour of thoughtful and engaging discussion about real life with diabetes.
This week, I popped in a little late, but in plenty of time to catch a terrific chat a out diabetes stigma – from both within and outside the diabetes community.
Diabetes stigma is real. Have I experienced it? You bet.
Stigma is unsettling, and it comes from a place of ignorance. Is there any real animosity or vitriol? I like to think no, but it pains me that when there have been times of nastiness, it has come from within the community.
I can honestly say that I have never been stigmatised about my diabetes from anyone inside the diabetes community. But then, I have the type of diabetes that I didn’t cause myself. You know, the one that has nothing to do with the sorts of foods that I ate. The one that has nothing to do with me being overweight or inactive or lazy. I have the one that cute kids get – kids who are innocent and have done nothing to ask for this. And I have the tough one – the one that is the worst, the one that can cause death in an instant, the one that no one understands.
These are words that people from within the diabetes community have used when talking about type 2 diabetes. That’s right – by others living with (or living with a child with) diabetes. Perhaps it was in a discussion about the hopeless and insensitive comments made by some silly comedian; or perhaps in response to a diabetes report that doesn’t separate type 1 and type 2 diabetes.
And I am not the only one to have noticed this. The Walk With D campaign was set up because there was a need to acknowledge that … ‘Even within the diabetes community, there are levels of misunderstanding, misrepresentation, and mistaken messaging, often creating a divide where there should be a bridge.’
There have been some studies that also reinforce the idea that there certainly is stigma from within the community.
The ACBRD has been researching diabetes stigma for a couple of years now, starting with a project looking at the stigma experienced by people with type 2 diabetes and following up with a similar study about people with type 1 diabetes.
The second study discussed the perpetuation of type 2 diabetes stigma by people with type 1 diabetes and it’s interesting reading. You can read the full article here, but here are just some of the findings:
- In general, participants expressed somewhat negative attitudes towards, and beliefs about, people with T2DM. This included stereotypes such as ‘lazy’, ‘fat’, ‘over-consume’, ‘sedentary’, ‘unfit’ and judgment about the intelligence and character of people with T2DM, and blame for ‘bringing it on themselves’.
- These attitudes and beliefs served to perpetuate, and give voice to, the stigma surrounding T2DM and drove an in-group/out-group (or ‘us vs them’) mentality.
- It was also evident that there was resentment among people with T1DM toward those with T2DM, which stemmed from two main factors: (1) the perception that people with T2DM are responsible for many of the negative connotations that surround diabetes, and (2) the perception that T2DM, as a largely preventable condition, attracts more attention and therefore gets more resources and support than T1DM.
- Some participants believed that T1DM was the ‘real’ or ‘serious’ type of diabetes, and was more worthy of research attention and investment of societal resources than T2DM.
That sounds pretty stigmatising to me.
Let me be clear about my position here – there are different types of diabetes and people living with each of those types of diabetes has the right to find support and healthcare that is relevant and specific to their diabetes. A young person living with type 1 diabetes is, of course, going to have different needs to an older adult living with type 2 diabetes.
There are many times that we need to clearly define the different types of diabetes as this is important when it comes to getting the right treatment, seeing the right HCPs and ensuring the person living with diabetes has the right information.
I am not saying that there shouldn’t be specialised and tailored services and activities available to people depending on what they need, or relevant to the type of diabetes they have. I built a program from the ground up that was very specific and targeted in its approach to being only about and for people with type 1 diabetes. I get it!
And you absolute bet that people with type 1 diabetes should have access to support and peer opportunities that are specific. I know that for me the sense of ‘me too’ comes most strongly when I am speaking with other people with T1, usually women around the same age, who are working and have the same sort of technology, caffeine and boot addiction as I do – sometimes there does need to be a ‘sacred space’ for us to discuss the issues that are particular to the challenges presented by our brand of diabetes. And finding the perfect pair of knee-highs.
What I am saying is that I know that the stigma comes from a variety of places. And I believe that we should be advocating for diabetes messaging to be positive and beneficial to people living with diabetes. The challenge of getting that message across to people in the general community who have no idea about diabetes is difficult to manage and sometimes it has not been executed particularly elegantly.
But I am a firm believer in the strength of community and the support that it can offer. And to me, the diabetes community means everyone affected by diabetes – everyone. Stigmatising anyone inside that community does a great disservice to us all.
DISCLAIMERS ALL OVER THE PLACE!!
The ACBRD is a partnership between Diabetes Victoria and Deakin University and until very recently, Diabetes Victoria employed me. Since the ACBRD was established (6 years ago) I have worked with foundation director, Professor Jane Speight and her team on a number of different projects.
I have not received any funding from the ACBRD for my work with them. I just like to write about them because the work they do is very important and is changing the way that diabetes is perceived. And their work in diabetes and stigma is ground breaking. (Really! The Washington Post published this article in 2014, quoting Dr Jessica Browne from the ACBRD.)
Now, I just happen to share an office with the ACBRD. And this is on my office wall. I have found myself reading it quite a lot this week!

Click for larger image

I wrote about Spare a Rose, Save a Child last year. And the year before that.
I wrote about the easy and logical tie-in with Valentine’s Day.
I wrote about how I would be making a donation and encouraging my Valentine to do the same.
I wrote about how easy it is to support the campaign.
I wrote about how fabulously tangible the campaign is: 1 rose = AUD$6 = 1 month of insulin for a child.
I wrote about how easy it is to get involved.
I wrote about how no child should die because they cannot access life-saving medication.
I wrote all about it.
So I won’t do that again.
Instead – have a read! (And make a donation!)
_________________________________
Yesterday, as I sped around the supermarket, the onslaught of the next commercial opportunity hit me fair and square in the face. No, I’m not talking about Easter (I could act all outraged that there are Hot Cross Buns in Woolies, but we bought some and have been eating them, so that would be kind of hypocritical). I am talking about the festival of love – Valentine’s Day.
Valentine’s Day can go one of three ways for people. It can be a day of overt love declarations involving flowers, cards, poems, sky writing, gorilla-grams, stripper-grams (don’t judge), candle light, champagne, walks on the beach; it can be a day of sadness and misery and feeling left out; or it can be a day of complete oblivion where one is confused why there are so many people carrying bunches of balloons with ‘I wuv you, Shnookums’ written on them in glitter.
This year, I say screw that. This year, I say how about you do something that is meaningful that will not only help others, but also make you feel great. This year, it doesn’t matter if you have a Valentine or not. Everyone can play.
I am, of course, speaking of the Spare a Rose Save a Child campaign.
Now, if you have diabetes and/or any links to the diabetes word, you have probably seen and heard about this campaign before. I’ve even written about it here. The general gist is that instead of sending a dozen roses to your Valentine, send eleven instead and with the money that would have bought the extra one (about $6 in Aussie money) make a donation to Life for a Child. Those six bucks will provide insulin to a kid in a developing country for a whole month. Or, give your Valentine ten roses and donate $12.
All good, right?
But I have a little challenge for you.
This is a brilliant campaign because it is so simple. It’s easy to explain and it’s really easy to get involved. So my challenge is this. Let’s get this moving way out of the diabetes world. Let’s get this into the hands and hearts of our friends and family who may not really consider this as an idea for Valentine’s Day. Let’s tell our workplace HR teams and see if they can encourage it as a work-place wide giving program (there’s even a tool kit to get you started!). Pop in to visit your neighbours and ask them to get involved. Next time you are going for a walk in your local shopping centre, drop in to some of the small businesses and ask them to get involved. Ask your kids if they would like to donate some of their pocket money.
Roses and diamonds and jewellery and books and CDs and vouchers for massages and guitars and DVDs of favourite movies are all lovely and fun for Valentine’s Day and I am not suggesting you complete give up on the idea of sharing gifts. But how about sharing the love a little this year? I know that I certainly will be making a donation and have already strongly suggested to my Valentine that he do the same. (And check out this and this cute card to attach to your gift, telling your Valentine how you’ve shared the love this year.)
So, how about making sure a child has life-saving insulin available to them by donating just a few dollars in your loved one’s – or your – name. Because THAT is a gift of love and I honestly can’t think of anything I would like more this Valentine’s Day.
A couple of weeks ago, I sat in a packed Melbourne Town Hall. And there, on the stage, was Nigella Lawson. It is possible that I have never been so excited in all my life – the original and greatest domestic goddess in all the lands was sitting about five metres from me, sharing the same air! She is every bit as poised and elegant in person as she is on screen and her beauty is startling. I certainly squealed when she walked onto the stage!
So, was the hour or so that Nigella was sitting on the stage worth the time and money? Well yes. And no.
I have been to a number of these ‘in conversation’ events before and they can be hit and miss. Largely their success is dependent on the person asking the questions, or rather, guiding the conversation. And that was the frustration with Nigella’s session. Food writer and restaurant critic, Jill Dupleix, was a little clumsy in her attempts to steer the conversation. It probably didn’t help that she started with a dud question that I am sure was meant to break the ice, but had the complete opposite reaction. Nigella looked positively uncomfortable. Perhaps asking someone who has recently gone through a very public and awful relationship breakup about her sex life wasn’t very well considered.
But even after that, I felt that Dupleix was not a great choice of interviewer. She interrupted and gave her opinion about the audience questions. She was clearly afraid of silences!
Everyone in the room had come to hear from Nigella. We wanted to hear the secrets to her success and about her every day life. For me, I wanted to hear about how she had turned something she was so passionate about into a successful career. I had the kidlet with me, and she was enthralled as Nigella shared stories of how she got her start as a journalist and how she built an empire as a food writer.
When given the chance, the Domestic Goddess, using language in a way that was both beautiful and mesmerising, shared snippets into her life that were amusing and telling. (She keeps condiments such as mustard and soy sauce in little jars on her bedside table for when she is eating in bed so she doesn’t need to climb down the stairs, back to the kitchen, for them. Brilliant!)
Where the discussion worked was when Jill shut up and Nigella could speak, uninterrupted. Unfortunately, too often she was cut off, or the silences – probably where Nigella was trying to formulate her next thought – were cut short and we never got to hear the titbit of information that she was finding the right words to disclose.
I left feeling elated that I had been in the same room as Nigella, but disappointed that I had not heard more. Several people I spoke with afterwards said the same thing.
This is the power of effective communication. Whether it is in a room like that, or as a one on one consultation, the most important person in the room is the one who needs to be heard most, be given the most time to speak, and have the opportunity to set the agenda and direct the conversation. And this is the case in a formal interview, health appointment or even a conversation with a loved one at the kitchen table.
I have really kept this in mind recently. Yesterday was the first day of school and over the last week or so I have frequently checked in with the kidlet about how she is feeling as the holidays come to an end. As with any eleven year old, she moved between being excited and nervous. Some of the things taking up her attention were hilarious (how will I wear my hair on the first day, mum?) but as they were her concerns, they are legitimate. It wasn’t my place to tell her that no one would care if she was wearing a high or low ponytail, and she should be concentrating on important things like revising her times table.
No, my job is to shush and listen and ask gentle questions to get more out of her and then try to make her feel as calm and happy as I can.
It’s the same with the way that diabetes consultations are very frequently criticised for not allowing the PWD the opportunity to use the forum for what they need, instead, going through a tick-box exercise of what the HCP needs and wants. Surely the HCP should shush and listen.
I think that often we like to think that we are the most important person in the room; the our opinions count for more; that our voice should be the loudest; that anything we don’t like should be defended. But most of the time, unless we really are the most important person in the room (i.e. in the case of a HCP consultation, or if we are Nigella in a Town Hall full of people), we need to just shush and listen.
Because if we did that, just imagine how much more we would hear and learn.

Nigella Lawson in Melbourne last week.
I am always interested in seeing the sorts of campaigns other health organisations come up with – especially when trying to adequately express to people what it is like to actually live with whatever condition they represent.
In the diabetes world, we often focus on the debilitating complications when trying to communicate with the broader community, but that is really only one aspect of diabetes. There is so much more that we could talk about – the relentlessness of the condition, the fear we may feel, how our mental health and diabetes are intrinsically linked, the relationship we have with food and the increased rate of eating disorders, how diabetes impacts those around us. So, so much.
But what doesn’t get done all that well, is trying to actually explain the physiological side of living with diabetes. Our invisible illness makes it difficult to point to a bruised arm or a bandaged head to ‘show where we hurt’.
Diabetes is not alone here. Multiple sclerosis is another condition that is complex and has little community understanding. I know I for one have no idea about what living with this particular autoimmune condition would be like. So I was really interested to see how the campaign from MS Australia, which uses an interesting analogy to explain what life with MS, is all about. Have a look at This Bike Has MS:
Now I don’t live with MS, so I can’t say if this is in any way an accurate representation of the physical issues which impact on day-to-day life. Does it provide a true portrayal of some of the problems faced by people living with MS?
I know that I was quite scathing a few years ago when describing what I considered to be a well-meaning, but pretty useless simulation of a hypo. Perhaps people living with MS are echoing my criticism of the hypo simulator, claiming that this ad really doesn’t explain much. There may be ways to try to demonstrate – or even allow someone to experience – some of the physical aspects of a health condition. But they only go a little way to explaining the real life, day-to-day, emotional and psychological pieces that make up chronic health conditions.
But however flawed these attempts may be, I still think that they are important, because they go some way to explaining – or at least illustrating – the condition in a physical way. Getting on that bike will give someone a sense of the physical side of MS, just like the hypo simulator demonstrated some of the physical symptoms that accompany a low.
And any efforts that results in less stigma, more compassion and better understanding of why we need to continually lobby and advocate for more – for better – is a good thing.
Almost fourteen and a half years ago, I took up a very part time job at Diabetes Victoria.
The diabetes world was a little different back then and today, as I packed up my office and was farewelled by a group of amazing women I have been honoured to call my team, I reflected back over the years.
- I had been using a pump for about five months when I started working there. It was the first time that many people in the organisation had ever seen one and there were a lot of questions.
- The pump situation in Australia was a little different to today. If you wanted a pump, you had a choice of a Medtronic 507C or a Disetronic DTron.
- Smart pumps were not a thing yet!
- There was no DAFNE yet either.
- The few of us who were pumping had to self-fund the consumables to the tune of about $300 per month.
- It was in May 2004, after a lot of lobbying, that the Government announced that pump consumables would be listed on the NDSS, reducing their costs to about $30 per month. This was the first taste I ever had of political lobbying and advocacy and I loved it!
- Within my first three weeks of being in the job, about half a dozen different women called saying they wanted information about diabetes and pregnancy. We didn’t have anything, so together with some like-minded groups, we set about developing a resource that provided all the information women wanted in a format they liked. That was my first taste of realising how important it was to listen to the ‘consumer’ and it became the overarching philosophy of my work.
- No one was talking prevention of type 2 diabetes. And when that started, it started a discussion about a huge issue.
- No one was talking about diabetes and mental health – except those of us living with the condition. We knew that it was real; we knew that burnout was debilitating; we knew that our mental health directly correlated with our ability to manage our diabetes. Seeing the Australian Centre for Behavioural Research in Diabetes become a real thing has been a game changer for people with diabetes as it has opened the discussion in ways we could only have imagined!
- People with diabetes at diabetes conferences? Not really, but we have made some strides there! (Psssst….but not enough!)
- Social media? Not a thing back in 2001. Now, online support, which was fledgling to say the least back in 2001, is everywhere and accessible by many, many people.
What a change a (almost) decade and a half makes! The diabetes landscape is very different. I’m glad I get to still be a player in this space in my new national job.
But today, it’s about saying goodbye.
And with that, I want to acknowledge a group of women. These women:

To (in alphabetical order), Alice, Angela, Anika, Carolyn, Elise, Elizabeth, Jane, Kelly, Kim and Kristina: thank you for making my last day so lovely. But more so, thank you for being the people who ‘do’. Each and every day, you come into work and do things alongside – in partnership – with people affected by diabetes to improve their lives in some way. Your commitment to people living with diabetes is second to none, there is no other team like this one in Australia and the work that you do each and every day is, in fact, life changing. We hear that frequently.
I am so fortunate that I got to lead you in my clumsy and sometimes ranty way, and I thank you all for indulging me as you have. I wish you all the best and will be watching – very closely – all your future successes.
Last night, Aaron and I joined a group of friends at the beautiful Sun Theatre in Yarraville for a ‘cinematic experience’. Harking back to the ‘good ol’ days’, we saw a film shot in 70mm Ultra Panavision with an overture at the beginning, an intermission of exactly 13 minutes in the middle and a souvenir program to take home at the end. (We’ll ignore the fact that rather than watching Ben Hur, introduced by Bill ‘Golden Age of Hollywood’ Collins, we were watching Quentin Tarantino’s eighth movie, ‘Hateful Eight’ (H8ful Eight??? Hateful 8???) with all the gore and violence – yet surprisingly still so much grace and beauty – one has come to expect in a Tarantino film.)
Often, there is much chatter about the ‘good ol’ days’. I get it. It was a time where things seemed simpler: kids were kids, adults were adults and everyone knew where they belonged. Milk came in bottles with cream on top….And I walked ten miles to school and twenty miles home, all uphill.
We can look back nostalgically at different periods in history. And it’s funny how history repeats itself. I remember hearing my father telling me how lousy the 1980s music I loved was compared to the music he loved. And yet his favourite music – the Beatles, Frank Sinatra, Simon and Garfunkel – would have had the same said about them. I try to catch myself before I criticise the trash music daughter is listening to now, because I remember how annoying it was (and how distressed I was) when my dad criticised Morten Harket.
Last week, Aaron got into a Facebook discussion that started off being about music and somehow ended up not being about music. The person he was ‘speaking’ with was saying that everything was better in the ‘olden days’.
‘Everything?’ asked Aaron
‘Yes,’ she replied. ‘Everything!’ She then went on to explain what she included in her ‘everything’ – music, food, medicine…
He quickly jumped in and pointed out that thanks to advances in medicine, his wife is still around. The olden days were really not all that great for those living with a health condition such as type 1 diabetes.
Perhaps because I am a beneficiary of all that the ‘modern era’ has to offer, I have no nostalgia or desire to go back in time. Because for me, along with sentimental thoughts of kids playing in the streets until dusk – and playing meant being outside, not sitting in front of a console – and cooking meant making foods from scratch and a telephone call was something made from a phone with a chord, there would be the practicalities of boiling syringes and sharpening needles and an inability to accurately measure BGLs and a life without diabetes technology. Bygone era? No. Be gone!
I would take the modern era and all its so-called short comings in a heartbeat over the ancient era of medicine! Through our rose-coloured glasses we forget that there were days before vaccines and days when life expectancy was shorter. We forget that there were not tests or screening to identify different conditions, that mental health was rarely, if ever, discussed. We forget that only 94 years ago – not that long ago – there was no medication to treat someone with type 1 diabetes.
So with all this in mind, read what is coming next. Here is an update on a couple of the many artificial pancreas projects happening today.
I want a cure as much as the next person. But in the meantime, keep the DTech coming. Please.
When I look back at the numerous (i.e. far too many) encounters I have had with healthcare professionals, some stand out. Fortunately, a lot of the time it is because the care I have received has been outstanding and delivered by wonderfully caring and respectful professionals. But there have been times where the experience was no so good.
One of the stories I tell when speaking to medical students about what makes for good communication comes from a very difficult time. I was in hospital with terrible stomach issues. A new doctor had been referred to me and for the ease of this tale, we will call him Professor Poor Communication Skills – Prof PCS for short.
Prof PCS was an expert in his field and by the end of my time in hospital, I actually quite liked him. He was loud and direct and I appreciated his no-messing-around attitude. Plus, he worked out what was wrong with my stomach, stopped the pain and got me out of hospital.
However, it took a while – and a little bit of coaching – for me to come to like him.
When Prof PCS came to see me for the first time I had already been in hospital for about a week. I went through what had been going on and he ordered a few blood tests and x-rays. With that, he promised to return the following day with the results. I didn’t really mind the way that he blustered in and out in a flash and didn’t explain anything because really, there was nothing to explain! I didn’t mind that he didn’t give me details of the tests he was running because I could kind or work them out and figured I could ask questions the next day.
I didn’t really care for the way he had stormed in and not introduced himself. Or the way he didn’t make eye contact when he spoke.
The next day came and I waited for him to do his rounds. Late in the afternoon, I heard his booming voice in the corridor. I remember thinking that he was speaking terribly loudly to his patient about their test results and that everyone could hear.
As he rounded the corner into my room, I realised that he had been talking about my test results. By the time he was standing at the end of my bed, he was halfway through a sentence and announcing all sorts of things that didn’t make sense because I had kind of missed the beginning of what he had been trying to say.
I looked at the nurse who was standing slightly behind him. I was confused. And I was actually a little angry.
‘Excuse me,’ I said to him. And then repeated myself. ‘Excuse. Me.’
‘Yes?’ I don’t think he was used to being interrupted because he looked a little surprised.
‘Hi,’ I said. ‘Can we just stop for a second?’ I took a deep breath, collected my thoughts and started.
‘For this to work,’ I waved my hands between the two of us. ‘I need you to be in the same room that I am in. I need to be able to see you when you speak. I need to be able to ask you questions and be clear that you are speaking to me. I need to see your body language and your eyes and be clear about what you are saying. I do not want you to start your consultation with me whilst you are still in the corridor. Is that okay?’
He looked stunned and completely lost for words. The nurse smiled.
I can’t believe that I was the first person to have ever pulled him up on this behaviour, but when he left the room (after explaining things very clearly, answering my questions and telling me what I could expect next) the nurse said that she had never seen him look stunned before. She also said that other patients had commented on how uncomfortable they were with his ‘bedside manner’, but no one had ever commented on it directly to him.
I was reminded of this encounter the other day when I was reading about Kate Granger and her #HelloMyNameIs campaign.
Kate is a doctor – a geriatrician and a writer. She is also has terminal cancer.
When she was an inpatient, she noticed that many of the healthcare professionals looking after her did not introduce themselves. She had no idea who was speaking to her about her care. She (and her husband) decided to do something about it. This from the #HelloMyNameIs website:
‘…we decided to start a campaign to encourage and remind healthcare staff about the importance of introductions in the delivery of care. I firmly believe it is not just about knowing someone’s name, but it runs much deeper. It is about making a human connection, beginning a therapeutic relationship and building trust. In my mind it is the first rung on the ladder to providing compassionate care.’
It’s incredible how such a simple idea has taken flight. Events have been held throughout the UK and there have been over 800 million impressions on social media. The more I have read, the more amazed I am at just how far-reaching this initiative is and how entrenched it has become in some places.
It is indeed wonderful.
However it is also kind of shocking that we need a campaign to remind people to introduce themselves and remember the importance of taking the time to connect with people at a time where they are possibly feeling very vulnerable and scared.
The next time I speak with medical and nursing students about effective communication, I will be holding up #HelloMyNameIs as an example of doing things right. And it will be the perfect anecdote to balance out the Prof PCS story.

Yesterday, we took the kidlet to her new orthodontist. We had been referred from her dentist and this was going to be the first discussion about the kid needing braces. She had a bit of nervousness about the whole process and wasn’t feeling all that great. She was also concerned that there would be pain involved. But, as I explained, this was just a chance for us to hear what was ahead and hopefully be able to ask any questions we might have. Plus she could meet the people at the clinic who she would be seeing regularly. And I also reminded her several times that if she didn’t feel comfortable with what she saw and who we met, we could go elsewhere.
The second we walked in, I knew that we would be staying with this clinic. The first thing we noticed on the wall was a white board which said ‘Welcome to today’s new patients’ and we spotted our kid’s first name up there with a few other names. The kidlet felt pretty good about that!
We walked to the front desk, and a lovely woman smiled at us all and turned her attention straight to the kidlet, saying hello and welcoming her to the clinic and introducing herself. She made eye contact the whole time with the kid before turning to hand me a clipboard. ‘Would you mind filling this in please? And, if it’s okay with you,’ she said turning back to the eleven year old, ’I’d like to show you around.’
The two of them went on a little tour of the practise and I heard them chatting away, the kidlet asking questions as each different space was introduced. When the kid returned to us in the waiting room, she was holding a clipboard of her own. ‘I need to fill this in,’ she said, and took great care answering questions about her likes and dislikes and interesting things about herself.
A short while later, the dental nurse came into the waiting room and, again, went straight to the kid. ‘Hi, I’m K,’ she said holding out her hand. ‘Is this mum and dad?’ She asked turning to us.
‘Now, I need to take some photos – just in that room over there. The room is tiny – are you okay to come by yourself? Or you can bring mum or dad if you’d like.’ The kidlet jumped up and smiled, clearly very pleased at being asked directly what she wanted. ‘I’ll be fine,’ she said.
The rest of the appointment continued the same way. When we were shown into the treatment room, K explained exactly what would happen once the orthodontist entered the room. The orthodontist welcomed the kidlet first and then introduced herself to us. The kidlet was asked regularly if she had any questions and anything she did ask was answered efficiently and clearly. She was congratulated on asking smart questions (mostly different versions of ‘is it going to hurt’) and no one tried to rush through things or to dismiss any of our questions.
The practical side of things – i.e how we would need a second mortgage to afford the treatment – was explained clearly to the grown-ups in the room and the ‘rewards’ system (a points program which earned gift vouchers) was explained to the kid. She looked delighted!
We left the clinic feeling very well informed. All our questions had been answered and we knew exactly what was going to happen next. The kidlet felt really positive about the whole experience too.
This is ‘patient-centred’ care at its best. It’s not just lip-service – it was far more than the staff all being overwhelmingly lovely. They were genuinely focused on ensuring that everyone knew what was going on and that the kid understood that this was all about her. She was given options – each of them explained to her – and then we were asked to think about them and make decisions, with the option of being able to ask further questions if needed.
So what does this level of care and attention take? It certainly took no more time that would be expected of a first consultation. There were no more staff members involved than at any other clinic offering the same service.
But what it did take is care and attention and an understanding of the ‘customer’. And respect. A lot of respect.





 Diabetogenic
